Cause:Human papilloma (venereal wart) virus (HPV) (Venereal (Genital) Warts), esp types 16 and 18 plus, less frequently, 31, 33, 35, and many others (Nejm 2003;348:518)
Pathophys:HPV genome becomes integrated into cellular DNA and causes malignant transformation. Squamous dysplasia may resolve, or untreated, may evolve to invasive carcinoma
Sexual intercourse transmits the virus, hence also associated with genital herpes of cervix and vulva (Nejm 1981;305:517, 483). HPV incidence in college women high (>40%), resolution and recurrence common (Nejm 1998;338:423)
Most common cancer in women after breast and lung. 65% of all female genital cancers; 95% are over age 30 yr. Incidence = 20/100000, 16000/yr in US women; CIS = 120/100000; 5000 deaths/yr in US
Increased incidence with early onset of sexual activity, number of sexual partners, h/o other STDs esp HIV (Jama 2000;283:1031; Nejm 1997;337:1343) and chlamydia (Jama 2001;285:47), smoking, bcp use (slight), and with asymptomatic macular and raised warty lesions on male partners
Sx: Usually none; may have vaginal bleeding, esp postcoital; vaginal discharge; pelvic pain, when invasive
Si:
Cervical erosion and mass
- Stage 0: carcinoma in situ
- Stage I: confined to cervix only
- Stage II: not to pelvic wall and not in lower 3rd of vagina
- Stage III: to pelvic wall
- Stage IV: rectum or bladder involvement
5-yr survival 50% overall (old data); 100% with CIS; 25% in stage IV with surgery
Ureteral obstruction; lymphatic mets, usually local; pregnancy worsens; postop sexual dysfunction in 25% (Nejm 1999;340:1383)
Lab:
Path:(Jama 2002;287:2114, 2120; 2001;285:1506)
- Conventional cervical Pap smear
- q 1 yr if <35 yr and/or multiple partners;
- q 6-12 mo if HIV pos and CD4 <500 and HPV positive (Jama 2005;293:1471);
- q 5 yr if >35 yr and <8 lifetime partners (Canadian Walton Rept—Can Med Assoc J 1982;127:581) and no h/o abnormal Paps or STDs in pt or partner; or
- q 3 yr at age 30-65 yr (Nejm 2003;349:1501);
- in elderly >65 yr, get 2-3 Paps 3 yr apart if not previously done then stop (Ann IM 1992;117:520).
- Unnecessary if s/p hysterectomy for benign disease (Nejm 1996;335;1559, 1599, Jama 1996;275:940). 5-10% false neg rate in best labs.
- Atypical squamous cells uncertain significance (ASCUS), should be <5% of Paps; about 25% will turn out to be serious higher grade lesions; check for HPV DNA (Jama 1999;281:1605, 1645) or follow PAP q 6 mo × 2-3 yr after rx of any infection and colpo if + HPV DNA or repeat ASCUS PAP.
- Atypical glandular cells (AGCUS) over age 35 yr, or under age 35 yr w irregular bleeding has a higher correlation w occult Ca than LSIL or ASCUS; typically needs colpo and endometrial bx
- Monolayer liquid technologies (Papnet, Autonet, and Thin Prep) improved sensitivity, not clearly better (Jama 2009;302:1757); their use for rescreening of 10% unnecessary (Jama 1998;279:235, 240) and much more expensive than manual rescreening (Jama 1998;279:235, 240)
Colposcopy with bx if Pap shows ASCUS 3 or more times in a row, papillomavirus, or if see a lesion. Acetic acid staining helps locate. Looking for: cervical intraepithelial neoplasia (CIN) I (mild dysplasia, or low-grade squamous intraepithelial lesion) (LSIL), CIN II (moderate dysplasia), CIN III (severe dysplasia) and carcinoma in situ (CIS); high-grade squamous intraepithelial lesion (HSIL) includes CIN II and III, and CIS. Should also do for AGCUS over age 35 yr or adenocarcinoma in situ
HPV DNA screening (Jama 2000;283:81, 87, 108; Nejm 1999;341:1633, 1687), 1 pgm level cut off has 94% sens and specif unlike 55% sens of Pap (Nejm 2007;357:1579, 1589, 1650); may be best used as f/u of equivocal Paps (ACP J Club 2003;139:79); SIL usually develops within 2 yr of infection if at all
Fig.11.1 Management of Atypical Squamous Cells of Undetermined Significance (ASC-US)

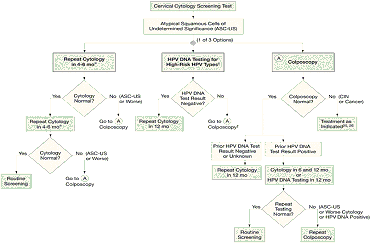
Reproduced with permission from Sawaya GF. A 21-Year-Old Woman With Atypical Squamous Cells of Undetermined Significance. J Am Med Assoc 2005; 294:2210.
Rx:Prevention: immunization (pXX); male circumcision halves rates (Nejm 2002:346, 1105); barrier methods of birth control
Vaccination of women (Venereal (Genital) Warts)
of low-grade SILs: f/u Paps since most regress and resolve, esp in young women (Nejm 1998;338:423)
of high-grade lesions: cryoRx, laser Rx, loop excision (LEEP), or occasionally cone bx; latter two incr subsequent PROM and preterm delivery (Jama 2004;291:2100); can do at same visit as Pap to incr compliance (Jama 2005;294:2173, 2182, 2210, 2225)
of carcinoma stage I and early II: radiation and surgery equieffective with 80% stage I and 50% stage II cures of advanced stage II, as well as stages III and IV: radiation; w advanced local disease even I B, cisplatin chemoRx w radiation improves survival (Nejm 1999;340:1137, 1144, 1154, 1198)
Perhaps a role for HPV-16 immunization, at least for vulvular Ca (Nejm 2009; 361:1838, 1899)