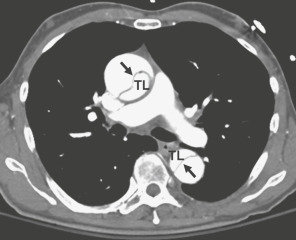
AUTHORS: Cristina Font, MD and Philip Stockwell, MD


Acute aortic syndromes are a spectrum of aortic pathologies that include aortic dissection, intramural hematomas (IMHs), and penetrating atherosclerotic ulcers.1 Aortic dissections are the most common and occur when blood passes through an intimal tear, separating the intima from the medial layers and creating a false lumen.1 IMH and penetrating aortic ulcer are variants of the classically described aortic dissection. Fig. 1 illustrates acute aortic syndromes.
Figure 1 Acute aortic syndromes.
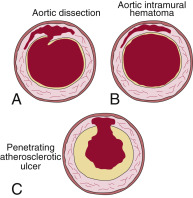
A, Classic aortic dissection. There is a tear in the intima with blood entering the media and a dissecting cleavage plane propagating for variable distances anterograde (and occasionally retrograde) throughout the aortic wall. B, Aortic intramural hematoma (IMH). A spontaneous hemorrhage of the vasa vasorum leads to bleeding within the media in the absence of an intimal tear or intimal flap. C, Penetrating atherosclerotic aortic ulcer (PAU). An ulcerated aortic plaque ruptures into the media, leading to an outpouching or ulceration in the aortic wall. This may be associated with IMH formation; pseudoaneurysm; or a focal, thick-walled aortic dissection. (From Zipes DP: Braunwald’s heart disease: a textbook of cardiovascular medicine, ed 11, Philadelphia, 2019, Elsevier.)
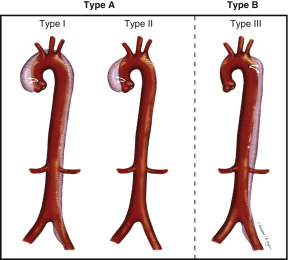
Aortic dissection is generally classified according to anatomic location (Fig. 2). Table 1 summarizes classification schemes of acute aortic dissection.
- Stanford (more commonly used classification system): Type A ascending aorta (proximal), type B descending aorta (distal)
- DeBakey: Type I ascending and descending aorta, type II ascending aorta, type III descending aorta
- The Society of Thoracic Surgery and Society of Vascular Surgery have recently proposed a classification system of dissection subtypes to more precisely define the location of disease as extending between two anatomic zones2
- Aortic dissection can also be classified by acuity of presentation: Hyperacute (<24 h), acute (2 to 7 days), subacute (8 to 30 days), and chronic (>30 days). The overall survival rate is inversely related to time of presentation, with the highest survival rate in the hyperacute group and the lowest survival rate in the chronic group
TABLE 1 Classification Schemes of Acute Aortic Dissection
| DeBakey Classification | |||
| Type I | Originates in the ascending aorta and extends at least to the aortic arch and often to the descending aorta (and beyond) | ||
| Type II | Originates in the ascending aorta and confined to this segment | ||
| Type III | Originates in the descending aorta, usually just distal to the left subclavian artery, and extends distally | ||
| Stanford Classification | |||
| Type A | Dissections involving the ascending aorta (with or without extension into the descending aorta) | ||
| Type B | Dissections not involving the ascending aorta | ||
From Mann DL et al: Braunwald’s heart disease, ed 10, Philadelphia, 2015, Elsevier.
| ||||||||||||||||||||
2.6 to 3.5 per 100,000 person-yr; more frequent in winter as compared to other seasons, although no clear reason has been identified.3,4
- Hypertension (found in up to 77% of patients with aortic dissection)3,5
- Atherosclerosis (found in up to 27% of patients with aortic dissection)3,5
- Preexisting aortic aneurysm (found in up to 16% of patients with aortic dissection)3,5
- Age (60 to 80 yr)
- Family history of aortic aneurysms/dissection
- History of cardiac surgery, aortic valve replacement, intraaortic catheterization1,3,5
- Disorders of collagen (Marfan syndrome, Ehlers-Danlos syndrome)3,5
- Vascular inflammation (giant cell arteritis, Takayasu arteritis, rheumatoid arthritis, syphilitic aortitis)
- Aortic coarctation, bicuspid aortic valve
- Turner syndrome
- Cocaine abuse (usually within 12 h of last use of cocaine)1,3,5
- Trauma (∼20% road accident fatalities found to have ruptured aorta on autopsy)1
- Pregnancy and delivery
- Fluoroquinolone use1
- Table 3 summarizes genetically triggered conditions associated with aortic dissection
TABLE 3 Genetically Triggered Conditions Associated with Aortic Dissection
| Marfan syndrome (MFS) | Autosomal dominant disorder of connective tissue caused by FBN1 mutation; incidence of 1 in ≈5000 individuals; multisystem manifestations, including ectopia lentis; mitral valve prolapse, aortic root aneurysm, aortic dissection; skeletal features (pectus deformities, scoliosis, arachnodactyly, hyperflexibility, tall stature, elongated fingers and toes); dural ectasia; spontaneous pneumothorax | ||
| Loeys-Dietz syndrome (LDS) | Autosomal dominant disorder caused by mutations in TGFBR1 and TGFBR2, associated with aneurysms and dissections involving the aorta and branch vessels, often at relatively small diameters and young age; manifestations include craniofacial features (hypertelorism, craniosynostosis, cleft palate, bifid or broad uvula), bluish sclera, arterial tortuosity, velvety and hyperlucent skin, easily visible veins, clubfeet, skeletal abnormalities; phenotypes may vary, including those with more pronounced craniofacial features and those with more cutaneous features; ectopia lentis has not been described in LDS; mutations in TGFB2 lead to a syndrome with an overlap in clinical features of LDS and MFS | ||
| Familial thoracic aortic aneurysm (FTAA) syndromes | Autosomal dominant disorders with variable expression and penetrance leading to thoracic aortic aneurysms (TAAs) and dissections at variable ages in families; ACTA2 mutations occur in 10%-15% of cases of FTAA and are associated with bicuspid aortic valve (BAV) disease, cerebral aneurysms, livedo reticularis, iris flocculi, PDA, moyamoya, and premature coronary artery disease; gene mutations causing familial thoracic aortic aneurysm and dissection (TAAD) include ACTA2, TGFBR1, TGFBR2, FBN1, MYH11, MYLK, TGFB2, SMAD3 | ||
| Vascular Ehlers-Danlos syndrome (vEDS) | Autosomal dominant disorder of collagen synthesis caused by a gene mutation in COL3A1 leading to rupture and dissection of the aorta (usually the descending and abdominal aorta) and branch vessels; manifestations include flexible digits, hyperlucent skin with visible veins, varicose veins, typical facial appearance, and spontaneous rupture of the uterus or bowel | ||
| Bicuspid aortic valve (BAV) | Congenital condition affecting ≈1% of the population, familial in ≈9% of cases; often associated with dilation of the ascending aorta and carries increased risk for aortic dissection; gene mutations include NOTCH1 and loci at 15q, 18q, 5q, and 13q; may be associated with FTAA | ||
| Turner syndrome (TS) | Genetic disorder affecting 1 in 2000 live-born girls and caused by complete or partial loss of the second sex chromosome (XO, Xp); women with TS often have BAV and aortic coarctation; associated with ascending aortic dilation for body size and increased risk for aortic dissection, especially when associated with BAV, hypertension, and coarctation | ||
| Aneurysms-osteoarthritis syndrome | Autosomal dominant genetic disorder resulting from mutations in the SMAD3 gene and associated with premature osteoarthritis, osteochondritis dissecans, skeletal features, aortic aneurysms, branch vessel aneurysms, and arterial tortuosity; overlap with LDS phenotype |
From Mann DL et al: Braunwald’s heart disease, ed 10, Philadelphia, 2015, Elsevier.
TABLE 2 Risk Factors for Aortic Dissection
TAVR, Transcatheter aortic valve replacement.
From Zipes DP: Braunwald’s heart disease: a textbook of cardiovascular medicine, ed 11, Philadelphia, 2019, Elsevier.
- Sudden onset of severe sharp, tearing, or ripping chest, back, or abdominal pain.1,3,5 However, painless dissection occurs in ∼6.3% of cases2
- Anterior chest pain (79% type A, 63% type B)3
- Back pain, abdominal pain (43% type A, 64% type B)3
- Syncope (19% type A, 3% type B), generally secondary to cardiac tamponade or stroke3
- Congestive heart failure (CHF)1
- May present with hypertension (28% for type A, 66% in type B dissection),5 although 25% present with hypotension (systolic blood pressure <100 mm Hg), which can indicate bleeding, cardiac tamponade, or severe aortic regurgitation.3 Patients presenting with very high systolic blood pressure (>180 mm Hg for type A, >200 mm Hg for type B dissection), as well as in those with systolic blood pressure ≤100 mm Hg, have significantly higher in-hospital mortality rates
- Pulse and blood pressure differentials (>20 mm Hg between arms) in 19% to 31% of cases caused by partial compression of subclavian arteries6
- Aortic regurgitation in 40% to 75% of cases of proximal dissection,1 often with diastolic decrescendo murmur
- Myocardial ischemia caused by coronary artery occlusion, most commonly involving the right coronary artery
- Stroke in 5% to 10% of patients (secondary to dissection into or decreased blood flow to the carotids)1
- Mesenteric ischemia occurs in 3% to 5% of cases, with external compression, flap prolapse, or involvement of arterial ostia1
- Horner syndrome (ptosis, miosis, anhidrosis)
- Vocal cord paralysis or hoarse voice (caused by compression of the left recurrent laryngeal nerve)1
Genetics, in addition to other risk factors (Tables 4, 5, 6, and 7), contribute to the development of aortic aneurysms and dissection.
TABLE 7 Crawford Classification of Thoracoabdominal Aneurysms
| I | Descending thoracic aorta to suprarenal aorta | ||
| II | Proximal descending thoracic aorta to infrarenal aorta (below the diaphragm) | ||
| III | Mid descending thoracic aorta to infrarenal aorta | ||
| IV | Supravisceral aorta to infrarenal aorta |
From Soto JA, Lucey BC: Emergency radiology: the requisites, ed 2, Philadelphia, 2017, Elsevier.
TABLE 6 Descending Thoracic Aortic Aneurysm
| Degenerative | Resulting from atherosclerosis | ||
|---|---|---|---|
| Focal pseudoaneurysm resulting from a penetrating aortic ulcer | |||
| Arteritis | Giant cell | ||
| Takayasu | |||
| Behçet disease | |||
| Inherited/connective tissue | Marfan syndrome | ||
| Ductus aneurysm | |||
| Loeys-Dietz syndrome | |||
| Infectious | Mycotic aneurysms | ||
| Traumatic | Posttraumatic pseudoaneurysms | ||
| Chronic aortic transection |
From Soto JA, Lucey BC: Emergency radiology: the requisites, ed 2, Philadelphia, 2017, Elsevier.
| Degenerative | Resulting from Atherosclerosis | ||
|---|---|---|---|
| Arteritis | Giant cell | ||
| Takayasu | |||
| Behçet disease | |||
| Infectious | Syphilis |
From Soto JA, Lucey BC: Emergency radiology: the requisites, ed 2, Philadelphia, 2017, Elsevier.
TABLE 4 Ascending Thoracic Aortic Aneurysms
| Degenerative | Associated with Atherosclerosis | ||
|---|---|---|---|
| Inheritable/connective tissue | Marfan syndrome | ||
| Ehlers-Danlos syndrome | |||
| Loeys-Dietz syndrome | |||
| Turner syndrome | |||
| Osteogenesis imperfecta | |||
| Rheumatoid arthritis | |||
| Bicuspid aortic valve | |||
| Aneurysm of sinus of Valsalva | |||
| Arteritis | Giant cell | ||
| Takayasu | |||
| Behçet disease | |||
| Relapsing polychondritis | |||
| Infectious | Syphilis | ||
| Mycotic aneurysms |
From Soto JA, Lucey BC: Emergency radiology: the requisites, ed 2, Philadelphia, 2017, Elsevier.