AUTHOR: Joseph S. Kass, MD, JD, FAAN
Dementia is a syndrome characterized by progressive loss of previously acquired cognitive skills, including memory, language, insight, and judgment. Alzheimer disease (AD) is thought to account for the majority of all cases of dementia.
| ||||||||||||||||||||
Risk doubles every 5 yr after the age of 65. The Chicago Health and Aging Population
study found that the average annual incidence in people ages 65 and above was 2.3%, with Blacks having a significantly increased risk compared to Whites.1
Approximately 1/9 people (10.7%) ages ≥65 has Alzheimer dementia. Currently an estimated 6.5 million Americans have AD; 5% of the population between the ages of 65 and 74, 13.1% between 75 and 84, and 33.2% at ≥85 yr. Between 12% and 18% of Americans over age 60 are thought to have mild cognitive impairment (MCI).2
Females greater than males. In the U.S. 4 million women versus 2.5 million men are affected (12% of women, 9% of men ≥65).2
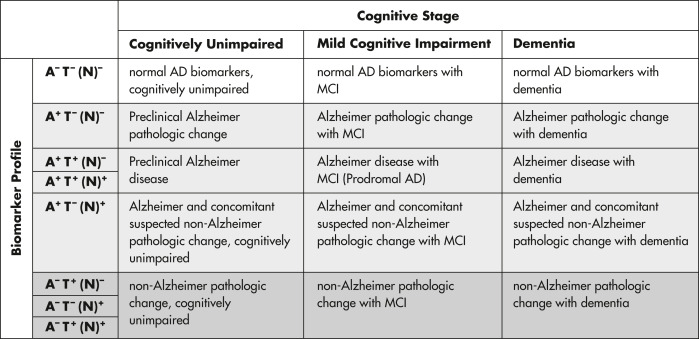
Diagnosis of AD has evolved with the development of biomarkers that indicate AD pathology in vivo such as brain amyloidosis and pathologic tau accumulation. The National Institute on Aging (NIA) and the Alzheimer Association (AA) recommended new diagnostic criteria and guidelines for AD in 2011, and these criteria were further revised in 2018 (Table 1). The NIA-AA criteria differed from prior DSM or NINDCS-ADRDA criteria in the following ways: (1) They recommend AD be considered a disease well before the onset of symptoms by incorporating biomarkers in diagnosis, and (2) they define three distinct stages of AD: (1) Preclinical AD, in which there is measurable biologic evidence of AD pathology but no symptoms; (2) MCI due to AD, in which the patient experiences mild memory loss but experiences no functional impairment at home or work but demonstrates biomarker evidence of AD; and (3) dementia due to AD, in which the patient experiences cognitive decline causing functional impairment and demonstrates biomarker evidence of AD. The 2018 NIA-AA criteria define AD not as three clinical syndromes but as a biologic process defined by biomarkers indicating the presence of beta amyloid (A+), pathologic tau (T+), and neurodegeneration or neuronal injury (N+). Using the ATN system and clinical status together allows an entire study population to be characterized (Fig. 1).
TABLE 1 New Diagnostic Criteria
| Research Criteria | |||
|---|---|---|---|
| Criteria for Probable Alzheimer Disease | DSM-5 2013 | NINCDS-ADRDA 2007 | NIA-AA 2018 |
| Insidious onset | X | X | X |
| Onset over months to years | X | X | |
| Progressive decline | X | X | X |
| Deficits are not explained by delirium or other medical or psychiatric conditions | X | X | X |
| Social/occupational impairment | X | X | |
| Presence of episodic memory deficit | X | X | |
| Cognitive deficits in at least two domains | X | X | |
| Neuropsychologic testing required for diagnosis? | Preferably | X | Only if routine history and mental status testing are inconclusive |
| Abnormal PET or MRI scan | Supportive feature∗ | Required if needed to show biomarker evidence of amyloidosis, tauopathy, neurodegeneration as part of the biomarker-based AT(N) diagnostic schema | |
| Genetic markers? | X | Supportive feature∗ | For research purposes |
| Required only if there is evidence of multiple causes and no clear evidence of progression and decline in memory and another cognitive domain | |||
| Abnormal cerebrospinal fluid marker required? | Supportive feature∗ | Required if needed to show biomarker evidence of amyloidosis, tauopathy, neurodegeneration as part of the biomarker-based AT(N) diagnostic schema | |
DSM-5, Diagnostic and Statistical Manual of Mental Disorders, fifth edition; MRI, magnetic resonance imaging; NIA-AA, National Institute on Aging-Alzheimers Association; NINCDS-ADRDA, National Institute of Neurological and Communicative Disorders and Stroke-Alzheimers Disease and Related Disorders Association; PET, positron emission tomography.
∗At least one supportive feature is required for diagnosis of probable AD.
Modified from Fillit HM: Brocklehursts textbook of geriatric medicine and gerontology, ed 8, Philadelphia, 2017, Elsevier.
Figure 1 Descriptive nomenclature: Syndromal cognitive staging combined with biomarkers.
AD, Alzheimer disease; MCI, mild cognitive impairment. NOTE: Formatting denotes three general biomarker categories based on biomarker profiles: Those with normal AD biomarkers (no color), those with non-AD pathologic change (dark gray), and those who are in the Alzheimer continuum (light gray).
From Clifford RJ Jr et al: NIA-AA research framework: toward a biological definition of Alzheimers disease, Alzheimer Dement 14:535-562, 2018.
Although not yet commonly used in the clinic but invariably used in AD clinical trials, biomarkers transform the diagnosis of AD into one that can be established definitively while the patient is still alive. In clinical practice, the diagnosis is commonly made based on clinical history, a thorough physical and neurologic examination, and use of reliable and valid diagnostic criteria (i.e., DSM or NINDCS-ADRDA) such as the following:
Red flags for an AD diagnosis are summarized in Box 1.
BOX 1 Red Flags for an Alzheimer Disease Diagnosis
|
Modified from Kaufman DM, et al: Kaufmans clinical neurology for psychiatrists, ed 8, Philadelphia, 2017, Elsevier.
TABLE 4 Clinical Features of Delirium, Depression, and Alzheimers Disease
| DELIRIUM | DEPRESSION | ALZHEIMERS DISEASE | |
|---|---|---|---|
| Onset of initial symptoms | Abrupt | Relatively discrete | Insidious |
| Difficulty with attention and disturbed consciousness | Dysphoric mood or lack of pleasure | Memory deficits-verbal and/or spatial | |
| Course | Fluctuating-over days to weeks | Persistent-usually lasting months if untreated | Gradually progressive, over years |
| Family history | Not contributory | May be positive for depression | May be positive for AD |
| Memory | Poor registration | Patchy/inconsistent | Recent >remote |
| Memory complaints | Absent | Present | Variable-usually absent |
| Language deficits | Dysgraphia | Increased speech latency | Confrontation naming difficulties |
| Affect | Labile | Depressed/irritable | Variable-may be neutral |
From Stern TA: Massachusetts General Hospital handbook of general hospital psychiatry, ed 7. Philadelphia, 2018, Elsevier.
TABLE 2 Cognitive Disorders in Older Adults
| Diagnosis (% of Dementias Attributable) | History | Physical Examination Findings | Imaging Findings | Comment |
|---|---|---|---|---|
| Normal aging changes (n/a) | Delayed retrieval (forgetting names, dates), slower processing (takes longer to learn new things). No functional limitations | None | Mild generalized cortical atrophy, mild ventricular enlargement. No focal findings | Patients may have white matter disease and/or prior lacunar infarcts related to HTN, DM, and cardiovascular disease, etc., but unrelated to memory complaints |
| Mild cognitive impairment (n/a) | Cognitive deficits beyond what is expected for age across one or more domains | None | Variable depending on etiology. Atrophy of medial temporal lobe and/or hippocampus (pre-Alzheimer disease) | |
| Alzheimer disease (67%) | Progressive memory loss and other cognitive deficits | Medial temporal, parietal lobe, and/or hippocampal atrophy on MRI. Positivity on amyloid PET scan | ||
| Vascular dementia (20%, includes mixed dementia) | Prominent vascular risk factors, possible history of stroke/TIA, possible stepwise disease progression. Executive dysfunction may be prominent early symptom | Variable depending on distribution of disease | Cortical and subcortical infarcts and white matter disease | Commonly present in conjunction with Alzheimer disease-known as mixed dementia |
| Lewy body dementia and Parkinson dementia (15%) | Fluctuating cognition, well-formed visual hallucinations, REM sleep disorder, falls, sensitivity to neuroleptics | Orthostatic hypotension, postural instability, hyposmia, bradykinesia, resting tremor, rigidity | No specific findings on MRI. Positivity on dopamine transporter PET scan | Parkinson dementia occurs in patients with preexisting Parkinson disease of at least 1-yr duration, followed by onset of cognitive deficits |
| Frontotemporal dementia (<5%) | Two variants: | Frontal release signs | Frontal and temporal lobe atrophy | Executive function and episodic memory generally preserved in early stages of disease |
| Chronic traumatic encephalopathy (CTE, unknown) | History of multiple concussions and/or traumatic brain injury, most commonly in former athletes or military personnel. Concurrent behavioral changes and psychiatric disease common | None | Nonspecific white matter changes | Tauopathy in cortical and perivascular regions of the brain. CTE can only definitely be diagnosed by autopsy; there is currently no definitive clinical criteria for diagnosis |
| Rapidly progressive dementia (<1%) | Memory symptoms progressive over weeks to months | Variable depending on etiology | ||
| Delirium (n/a) | Identifiable toxic, metabolic, or infectious etiology and/or precipitants (e.g., acute hospital admission). Rapid onset | Inattention, disorganized thinking, and/or altered level of consciousness. Fluctuating course | No specific findings |
DM, Diabetes mellitus; EEG, electroencephalogram; HTN, hypertension; MCI, mild cognitive impairment; MRI, magnetic resonance imaging; PET, positron emission tomography; REM, rapid eye movement; TIA, transient ischemic attack.
From Warshaw G et al: Hams primary care geriatrics, ed 7, Philadelphia, 2022, Elsevier.
TABLE 3 Features Distinguishing Alzheimer Disease and Frontotemporal Dementia
| Feature | Alzheimer Disease | Frontotemporal Dementia |
|---|---|---|
| Age at onset (yr) | >65 | 53 (mean) |
| Memory impairments | Early, pronounced | Subtle, at least initially, with preserved visuospatial ability |
| Behavior abnormalities | None until middle or late stage | Early and prominent perseverative and compulsive behavior; hyperorality; impaired executive ability |
| Language impairment | Except for anomia, none until late stage | Paraphasias, anomia, decreased fluency |
| CT/MRI appearance | General atrophy, but especially parietal and temporal lobes | Frontal and temporal lobe atrophy |
| Histologic marker | Aβ accumulation | Tau accumulation |
CT, Computed tomography; MRI, magnetic resonance imaging.
From Kaufman DM et al: Kaufmans clinical neurology for psychiatrists, ed 8, Philadelphia, 2017, Elsevier.
TABLE 5 Symptoms and Preserved Abilities of Alzheimer Dementia by Disease Stage Symptoms and Preserved Abilities by Cognitive Domain Across Various Stages of Alzheimer Dementia
| Mild | Moderate | Severe | |
|---|---|---|---|
| Memory | |||
| Symptoms | |||
| Preserved abilities | |||
| Executive Function | |||
| Symptoms | |||
| Preserved abilities | |||
| Language and Communication | |||
| Symptoms | |||
| Preserved abilities | |||
| Sensory/Perceptual | |||
| Symptoms | |||
| Preserved abilities | |||
ADLs, Activities of daily living.
From Warshaw G et al: Hams primary care geriatrics, ed 7, Philadelphia, 2022, Elsevier.
Brief mental status testing can be done easily and quickly in the office. Formal neuropsychologic testing offers more nuanced data about a patients current cognitive and emotional function but is not required for straightforward cases. Formal neuropsychologic testing is indicated when patients present with atypical symptoms, have significant psychiatric comorbidities, and when patients or families report of cognitive dysfunction differs from findings on a bedside cognitive assessment. Also, neuropsychologic testing may be beneficial if there are concerns that in the future, the patients testamentary capacity will be challenged.
Commonly used cognitive tests to detect dementia include the Folstein Mini-Mental State Examination (MMSE), the Mini-Cog test, and the Montreal Cognitive Assessment. A newer self-administered gerocognitive examination (SAGE) which patients complete by themselves, usually in 15 minutes is now available and consists of a validated 11-item instrument that compares favorably with MMSE and has the advantage of self-administration at home.3 A meta-analysis examining the performance of commonly used screening tests for dementia identified 11 commonly used tests, with the MMSE having the most data. The combined sensitivity and specificity for detecting dementia were 0.81 and 0.89, respectively, for the MMSE and 0.91 and 0.86, respectively, for the Mini-Cog. Subgroup analysis revealed that only the Montreal Cognitive Assessment had comparable performance to the MMSE for detecting MCI with 0.89 sensitivity and 0.75 specificity.
The Mini-Cog (https://mini-cog.com/) is a 3-min instrument consisting of a 3-item recall test for memory and a simply scored clock drawing test. The Montreal Cognitive Assessment (MoCA, www.mocatest.org/) is a 30-point test that takes approximately 10 min to administer and includes tests of visuospatial function, attention, verbal recall, language, abstraction, and orientation. A score of 25 points or less (26 points if the patient has <12 yr of education) indicates cognitive impairment. The test is available in >35 languages, and multiple forms in English allow for repeated assessments over time. A summary of commonly used tests may be found in Table E6.
Mental status testing should include tests that assess the following cognitive functions:
Patients with AD typically have trouble with verbal recall in addition to experiencing visuospatial or language deficits. Attention is usually preserved until the later stages of AD, so consider alternative diagnoses in patients who perform poorly on tests of attention early in their disease. A summary of the pattern of cognitive deficits associated with different dementias and depression may be found in Table 7.
TABLE 7 Patterns of Cognitive Impairment by Domain and Dementia
| Episodic Memory | Attention | Language | Executive | Visuospatial | Behavioral Symptoms | |
|---|---|---|---|---|---|---|
| Alzheimer disease | (I) | Simple (P) Divided (I) | Phonemic (P) Semantic (I) Naming (I) | (I) | Simple (P) Complex (I) | Early apathy, late psychotic symptoms |
| Mild cognitive impairment-amnestic | Immediate and Delayed recall (I) Recognition (I) | Simple (P) Divided (P) | (P) | (P) | (P) | (P) |
| Vascular dementia | Immediate and Delayed recall (V) Recognition (P) | Simple (P) Divided (I) | (I) | (I) | (P) | Depression |
| Behavioral variant FTLD | (V) | Simple (P) Divided (I) | (I) | (I) | (P) | Disinhibition, apathy, hyperorality, inappropriate social interaction |
| Semantic variant PPA | (P) | (P) | (I) Comprehension (I) Fluency | (P) | (P)(I) Visual agnosia | (P) |
| Nonfluent variant PPA | (P) | (P) | (I) Fluency (P) Comprehension,(I) Expressive speech | (P) | (P) | (P) |
| Parkinson disease dementia | (V) Immediate and Delayed recall (P) Recognition | (I) | (P) | (I) | (I) | Depression, possible hallucinations, psychomotor slowing |
| Dementia with Lewy bodies | (V) Immediate and Delayed recall (P) Recognition | (V) | (V) | (I) | (I) | Hallucinations, delusions |
| Depression | (V) Immediate and Delayed recall (P) Recognition | (V) | (V) Fluency (P) Naming | I/V | (P) | Psychomotor slowing, apathy |
FTLD, Frontotemporal lobar degeneration; I, impaired; P, preserved; PPA, primary progressive aphasia; V, variable.
From Fillit HM: Brocklehursts textbook of geriatric medicine and gerontology, ed 8, Philadelphia, 2017, Elsevier.
In addition to the common amnestic presentation, AD rarely presents as one of three rare nonamnestic syndromes that affect memory later in the course of the disease. These three rare presentations should also raise suspicion of another dementia type. A primary language variant presents as either logopenic expressive aphasia or progressive nonfluent aphasia and may be either a form of AD or of frontotemporal lobar degeneration. A primary visuospatial variant called posterior cortical atrophy presents with disturbances in complex visual processing and may be a form of either AD or dementia with Lewy bodies. An executive/behavioral variant presents with impaired executive function and/or behavior derangement and may represent either a frontal variant of AD or behavioral variant frontotemporal dementia.
TABLE E6 Commonly Used Neuropsychologic Tests
| Domains To Be Assessed | Tests Used with Age-Corrected and/or Education Norms for Adults Older than 65 Yr | ||
|---|---|---|---|
| Premorbid ability | |||
| Verbal memory | |||
| Visual memory | |||
| Simple attention | |||
| Language | |||
| Executive function | |||
| Visuospatial | |||
| Motor | |||
| Mood |
WAIS-IV, Wechsler Adult Intelligence Scale, fourth edition; WMS-IV, Wechsler Memory Scale, fourth edition.
From Fillit HM: Brocklehursts textbook of geriatric medicine and gerontology, ed 8, Philadelphia, 2017, Elsevier.
TABLE 8 Laboratory Evaluation of Patients with Dementia
| Type of Study | Examples | ||
|---|---|---|---|
| Basic studies, excluding reversible with specific indication from history for causes of dementia or examination |
| ||
| Adjuvant studies to Aid Diagnosis | |||
| Other tests as indicated by history or physical or neurologic examination | |||
From Fillit HM: Brocklehursts textbook of geriatric medicine and gerontology, ed 8, Philadelphia, 2017, Elsevier.
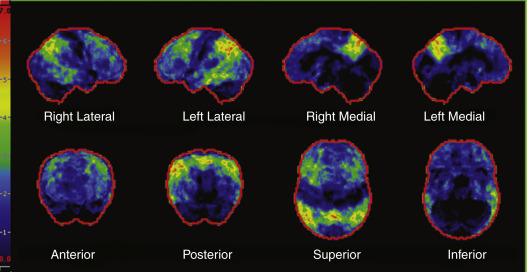
Relative Preservation of the Frontal and Occipital Lobes Consistent with Alzheimer Disease Dementia.
From Jankovic J et al: Bradley and Daroffs neurology in clinical practice, ed 8, Philadelphia, 2022, Elsevier.
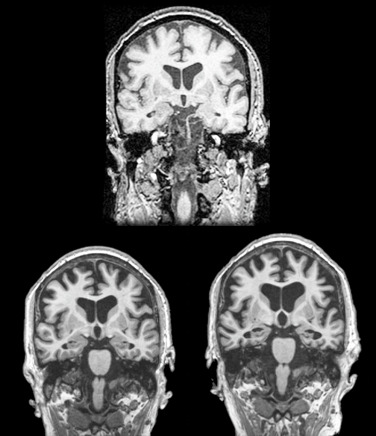
Note Progressive Hippocampal and Cortical Atrophy. Top Image: Normal Cognition Age 75. Bottom Left Image: Amci Age 81. Bottom Right Image: Dementia Due to AD Age 86.
From Jankovic J et al: Bradley and Daroffs neurology in clinical practice, ed 8, Philadelphia, 2022, Elsevier.
TABLE 9 Person-Centered Care Approach Applied to Care of People Living with Dementia
| Key Component | Early Stage | Middle Stage | Late Stage |
|---|---|---|---|
| Develop a personalized, goal-oriented care plan, based on a thorough medical, functional, and social assessment | |||
| Periodically review the persons goals and care plan to assess ongoing effectiveness and to address evolving goals | |||
| Engage an interprofessional team that adapts its composition in response to the needs of the person living with dementia | |||
| A specified team leader to facilitate information transfer, care coordination, and continuity | |||
BPSD, Behavioral and psychologic symptoms of dementia; CHe-I, acetylcholinesterase inhibitors; OT, occupational therapy; PT, physical therapy; SLP, speech language pathology.
From Warshaw G et al: Hams primary care geriatrics, ed 7, Philadelphia, 2022, Elsevier.
TABLE 13 Treatment of Behavioral and Neuropsychiatric Symptoms
| Initial Dose | Maximum Dose | |
|---|---|---|
| Atypical Antipsychotics | ||
| Olanzapine | 2.5 mg qd to bid, may increase by 2.5 mg as needed | 7.5 mg bid |
| Quetiapine | 25 mg bid, may increase by 25 mg every 2 days | 250 mg tid |
| Antidepressants | ||
| Sertraline | 25-50 mg qd, may increase by 25 mg every week | 200 mg qd |
| Escitalopram | 10 mg qd, may increase after 1 wk to 20 mg qd | 10 mg qd |
TABLE 10 Symptomatic Treatment of Memory Disturbance
| Initial Dose | Target Dose | |
|---|---|---|
| Donepezil | 5 mg qd for 4-6 wk | 10 mg qd |
| Rivastigmine | 1.5 mg bid with food, increase by 1.5 mg bid weekly | 3-6 mg bid |
| Galantamine | 4 mg bid with food, increase by 4 mg bid every 4 wk | 8-12 mg bid |
| Memantine | 5 mg qd, increase by 5 mg weekly | 10 mg bid |
TABLE 11 Acetylcholinesterase Inhibitor Dosing
| Drug | Initial Dose | Recommended Dose | Minimum Therapeutic Dose | Formulations |
|---|---|---|---|---|
| Donepezil | 5 mg daily | 10 mg daily | 5 mg daily | 5, 10, 23 mg |
| Galantamine IR | 4 mg bid | 12 mg bid | 8 mg bid | 4, 8, 12 mg |
| Galantamine ER | 8 mg daily | 24 mg daily | 16 mg daily | 8, 12, 24 mg |
| Rivastigmine | 1.5 mg bid | 6 mg bid | 3 mg bid | 1.5, 3, 4.5, 6 mg |
| Rivastigmine patch | 4.6 mg daily | 9.5 mg daily | 9.5 mg daily | 4.6, 9.5, 13.3 mg |
bid, Twice daily.
Acetylcholinesterase inhibitor dosing and suggested titration intervals. From US Department of Veterans Affairs. Pharmacy Benefits Management Services. 2018 [cited October 15, 2019]. Available at: http://www.pbm.va.gov/. Note that medication doses can be increased every 4 wk as patient tolerates.
From Warshaw G et al: Hams primary care geriatrics, ed 7, Philadelphia, 2022, Elsevier.
TABLE 12 Instruments Used to Monitor Clinical Response of Alzheimer Disease (AD) to Pharmacologic Therapy
From Fillit HM: Brocklehursts textbook of geriatric medicine and gerontology, ed 8, Philadelphia, 2017, Elsevier.
The physician should make a thorough search for the treatable causes of dementia. Current American Academy of Neurology practice parameters recommend:
TABLE 15 Genes Implicated in the Development of Alzheimer Disease
| Gene | Comment | ||
|---|---|---|---|
| APP | >30 known mutations associated with EOAD; located on chromosome 21; associated with elevated risk of AD in Down syndrome | ||
| PSEN1 | >150 known mutations associated with EOAD | ||
| PSEN2 | <20 known mutations associated with EOAD | ||
| APOE | Three known alleles: |
AD, Alzheimer disease; EOAD, early-onset Alzheimer disease; LOAD, late-onset Alzheimer disease.
From Warshaw G et al: Hams primary care geriatrics, ed 7, Philadelphia, 2022, Elsevier.
TABLE 14 Strategies for Prevention of Dementia
| Recommendation | Quality of Evidence | ||
|---|---|---|---|
| Engage in physical activity | Moderate | ||
| In adults with mild cognitive impairment, engage in physical activity to slow cognitive decline | Low | ||
| Tobacco cessation | Low | ||
| Do not exceed maximum daily recommended amount of alcohol intake | Moderatea | ||
| Follow a healthy diet based on WHO recommendationsb | Moderatec | ||
| Follow a Mediterranean diet | Moderate | ||
| Maintain a healthy weight | Low | ||
| Participate in cognitively stimulating activities or cognitive training | Low | ||
| Treatment of hypertension | High | ||
| Treatment of diabetes mellitus | Moderate | ||
| Treatment of dyslipidemia | Low |
Strategies for Prevention of Dementia, as based on World Health Organization (WHO) 2019 Guidelines for Risk Reduction of Cognitive Impairment and Dementia.
a 4 units of alcohol per week for men, 7 units of alcohol per week for women.
b Components include: 5 daily servings of nonstarchy vegetables, <10% dietary intake of free sugars, <30% dietary intake of fats (preferentially unsaturated fats), <5 g daily of salt.
c Strength of evidence is variable based on individual dietary components.
From Warshaw G et al: Hams primary care geriatrics, ed 7, Philadelphia, 2022, Elsevier.
For additional information for patients, families, and clinicians, contact the following organizations: