section name header

Basic Information ⬇

Author: Fred F. Ferri, MD

Definition

Herpes simplex is a viral infection caused by the herpes simplex virus (HSV). HSV-1 is associated primarily with oral infections, and HSV-2 causes mainly genital infections. However, either type can infect any site. After the primary infection, the virus enters the nerve endings in the skin directly below the lesions and ascends to the dorsal root ganglia, where it remains in a latent stage until it is reactivated.

Synonyms

  • Genital herpes
  • Herpes labialis
  • Herpes gladiatorum
  • Herpes digitalis
  • Oral herpes
ICD-10CM CODES
A60Anogenital herpesviral (herpes simplex) infections
A60.04Herpesviral vulvovaginitis
B00Herpesviral (herpes simplex) infections
B00.1Herpesviral vesicular dermatitis
B00.82Herpes simplex myelitis
B00.9Herpesviral infection, unspecified
P35.2Congenital herpesviral (herpes simplex) infection
Epidemiology & Demographics

  • •More than 85% of adults have serologic evidence of HSV-1 infection. The seroprevalence of adults with HSV-2 in the U.S. is 25%; however, only approximately 20% of these persons recall having symptoms of HSV infection.
  • •Most cases of eye or digital herpetic infections are caused by HSV-1.
  • •Worldwide, more than 400 million persons have genital herpes caused by HSV-2. In the U.S., one in five adults is infected with HSV-2, and 1 million new infections occur yearly.
  • •Frequency of recurrence of HSV-2 genital herpes is higher than HSV-1 oral labial infection.
  • •The frequency of recurrence is lowest for oral labial HSV-2 infections.
  • •The incidence of complications from herpes simplex (e.g., herpes encephalitis) is highest in immunocompromised hosts.
  • •Male circumcision significantly reduces the incidence of HSV-2.
Physical Findings & Clinical Presentation
Primary Infection

  • •Symptoms occur from 3 to 7 days after contact (respiratory droplets, direct contact).
  • •Constitutional symptoms include low-grade fever, headache and myalgias, regional lymphadenopathy, and localized pain.
  • •Pain, burning, itching, and tingling last several hours.
  • •Grouped vesicles, usually with surrounding erythema, appear and generally ulcerate or crust within 48 h (Fig. E1).
  • •The vesicles are uniform in size (differentiating it from herpes zoster vesicles, which vary in size). Scattered erosions covered with exudate may be noted on genitals (Fig. E2).
  • •During the acute eruption the patient is uncomfortable; involvement of lips and inside of mouth (Fig. E3) may make it unpleasant for the patient to eat; urinary retention may complicate involvement of the genital area.
  • •Lesions generally last from 2 to 6 wk and heal without scarring.
  • •Herpes whitlow is a term generally applied to HSV infection of fingers or toes, although strictly speaking, it refers to HSV infection of the paronychia. Among children, this condition is most commonly seen in infants and toddlers who suck the thumb or fingers and who are experiencing either a symptomatic or a subclinical oral HSV-1 infection (Fig. E4). An HSV-2 herpes whitlow occasionally develops in an adolescent as a result of exposure to infectious genital secretions. The onset of the infection is heralded by itching, pain, and erythema 2 to 7 days after exposure. The cuticle becomes erythematous and tender and may appear to contain pus, although if it is incised, little fluid is present. Incising the lesion is discouraged, as this maneuver typically prolongs recovery and increases the risk for secondary bacterial infection. Lesions and associated pain typically persist for about 10 days, followed by rapid improvement and complete recovery in 18 to 20 days. Regional lymphadenopathy is common, and lymphangitis and neuralgia may occur. Unlike other recurrent herpes infections, recurrent herpetic whitlows are often as painful as the primary infection but are generally shorter in duration.

Figure E1 Herpetic gingivostomatitis.
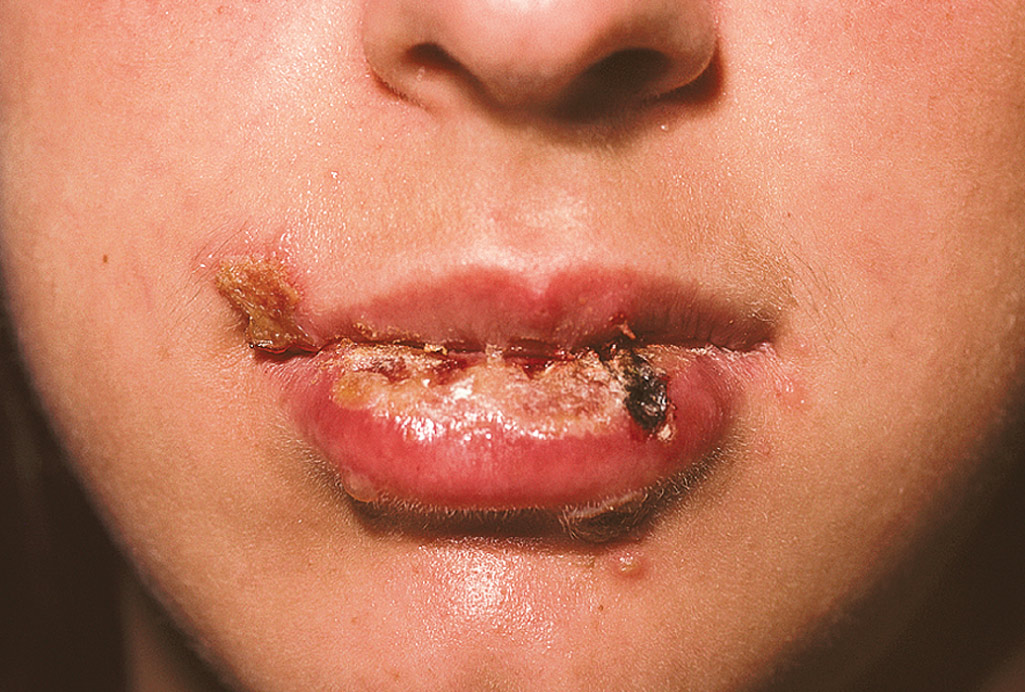
Multiple erosions with crusting. Note the associated lesions involving the chin.

(From Paller AS, Mancini AJ: Hurwitz clinical pediatric dermatology: a textbook of skin disorders of childhood and adolescence, ed 5, Philadelphia, 2016, Elsevier.)

Figure E2 Primary herpes simplex.
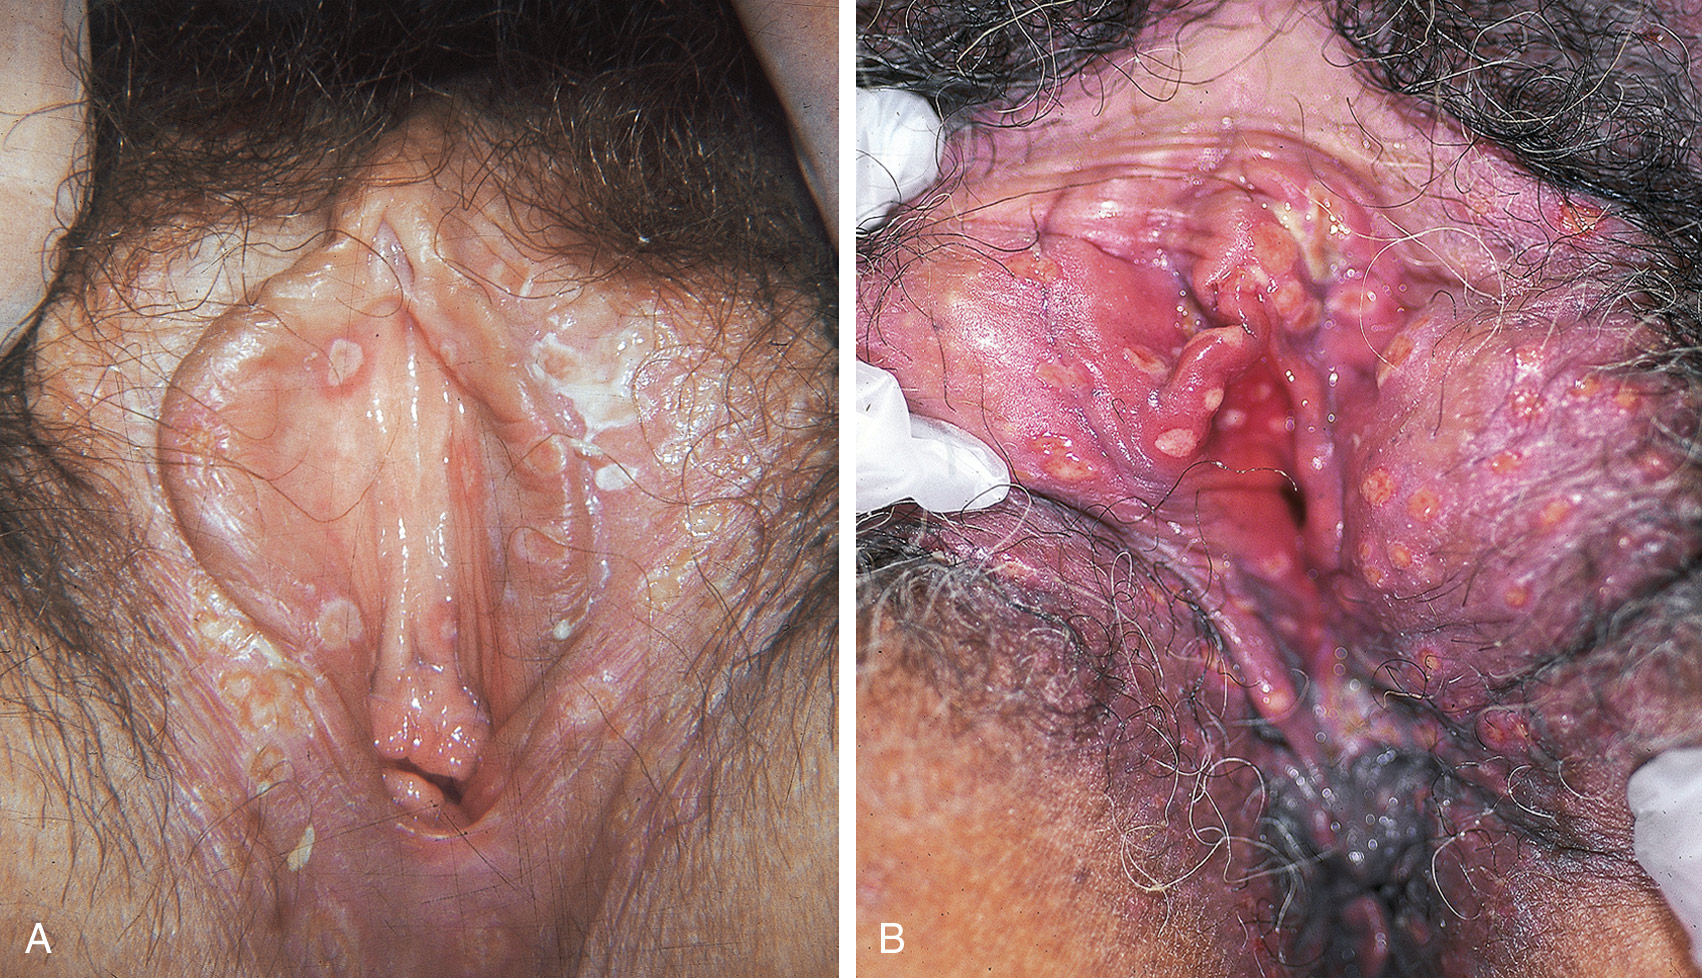
A, Scattered erosions covered with exudate. B, Numerous erosions appeared 4 days after contact with an asymptomatic carrier.

(From Habif TP: Clinical dermatology, ed 4, Philadelphia, 2004, Mosby.)
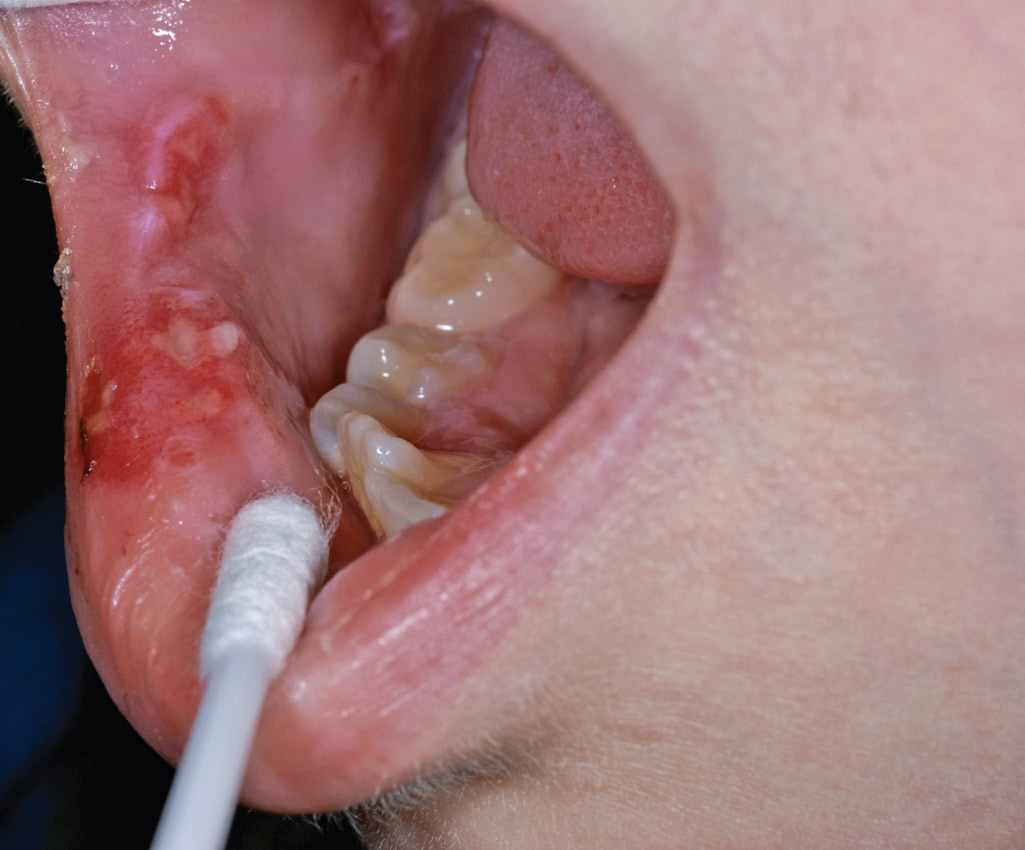
Figure E3 Herpes labialis.

Erythematous erosions clustered on the right lower lip in a patient with labial herpes. This young girl also had herpes-associated erythema multiforme.

(From Paller AS, Mancini AJ: Hurwitz clinical pediatric dermatology: a textbook of skin disorders of childhood and adolescence, ed 5, Philadelphia, 2016, Elsevier.)
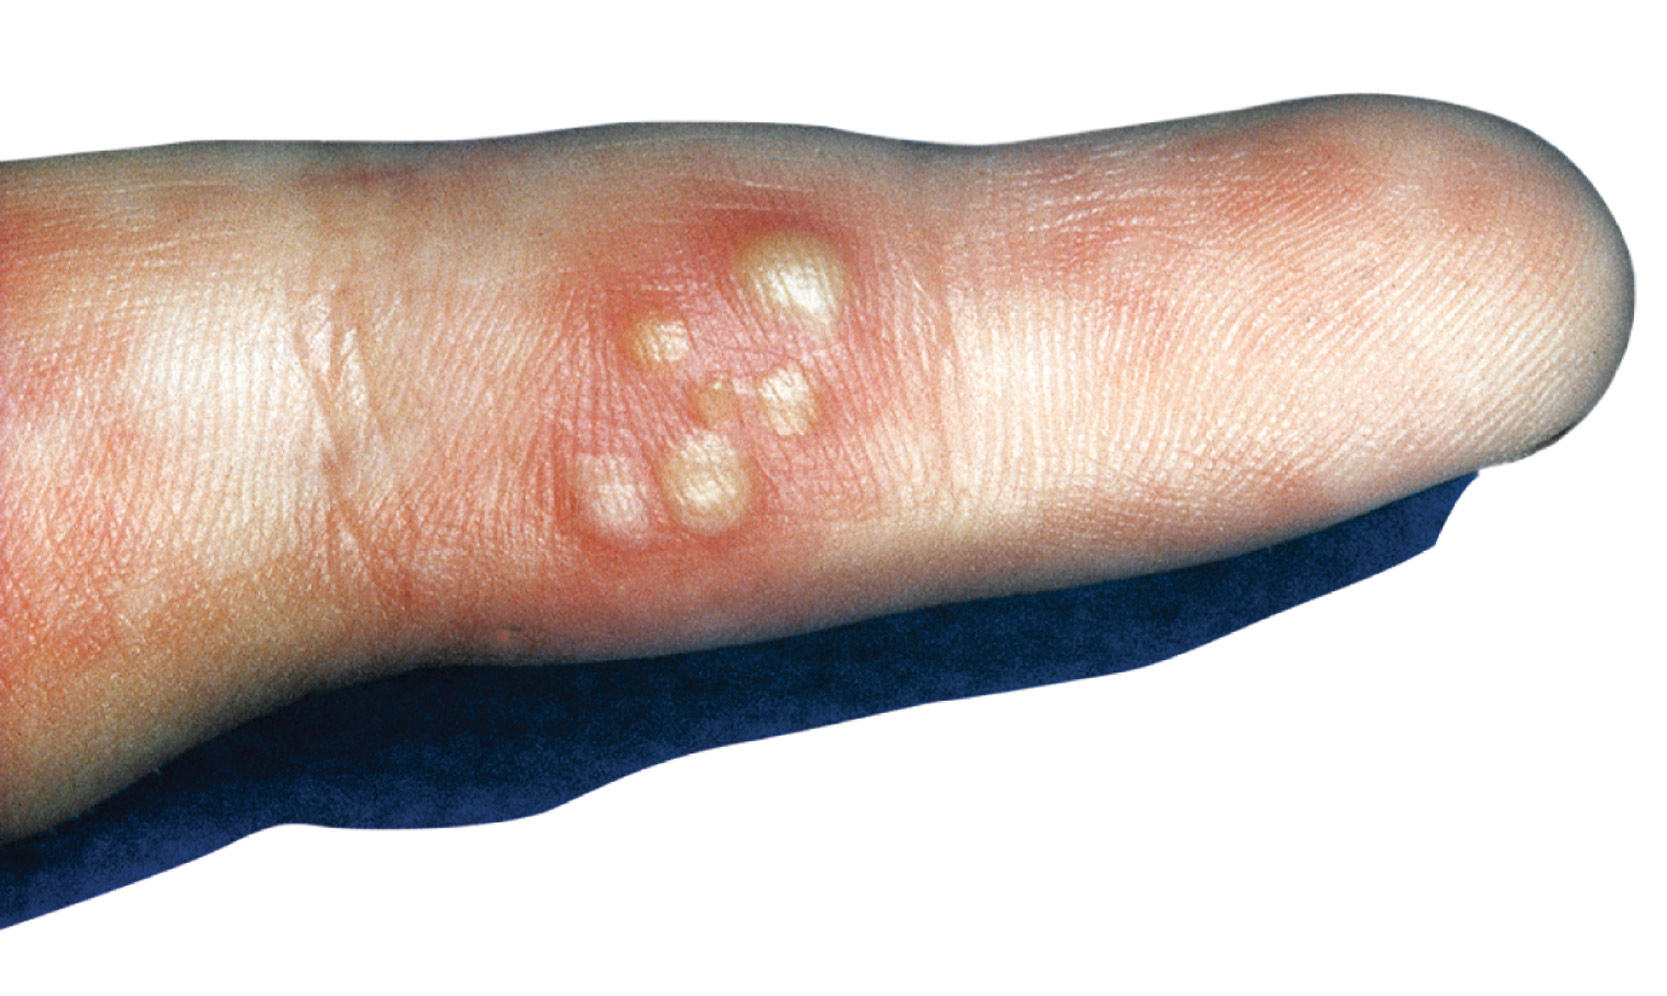
Figure E4 Herpes simplex infection of finger (whitlow).

(From Schachner LA, Hansen RC [eds]: Pediatric dermatology, ed 3, Philadelphia, 1988, Mosby, p. 1079.)

Recurrent Infection:

  • •Generally caused by alteration in the immune system; fatigue, stress, menses, local skin trauma, and exposure to sunlight are contributing factors.
  • •The prodromal symptoms (fatigue, burning and tingling of the affected area) last 12 to 24 h.
  • •A cluster of lesions generally evolves within 24 h from a macule to a papule and then vesicles surrounded by erythema; the vesicles coalesce and subsequently rupture within 4 days, revealing erosions covered by crusts.
  • •The crusts are generally shed within 7 to 10 days, revealing a pink surface.
  • •The most frequent location of the lesions is on the vermilion border of the lips (HSV-1), the penile shaft or glans penis and the labia (HSV-2), buttocks (seen more frequently in women), fingertips (herpetic whitlow), and trunk (may be confused with herpes zoster).
  • •Rapid onset of diffuse cutaneous herpes simplex (eczema herpeticum) may occur in certain atopic infants and adults. It is a medical emergency, especially in young infants, and should be promptly treated with acyclovir.
  • •Herpes encephalitis, meningitis, and ocular herpes can occur in patients with immunocompromised status and occasionally in normal hosts.
Etiology

HSV-1 and HSV-2 are both DNA viruses.

Diagnosis ⬆ ⬇

Differential Diagnosis

  • •Impetigo
  • •Behçet syndrome
  • •Coxsackie virus infection
  • •Syphilis, chancroid, granuloma inguinale (Table 1)
  • •Stevens-Johnson syndrome
  • •Herpangina
  • •Aphthous stomatitis
  • •Varicella
  • •Herpes zoster

TABLE 1 Features of Sexually Transmitted Infections Characterized by Genital Ulcers

SyphilisGenital HerpesChancroidGranuloma Inguinale (Donovanosis)
AgentTreponema pallidumHSV-1, HSV-2Haemophilus ducreyiKlebsiella granulomatis
Incubation10-90 days2-14 days1-10 days8-80 days
Systemic findings
  • Primary syphilis: Uncommon
  • Secondary syphilis: Fever, rash, malaise, anorexia, arthralgia, lymphadenopathy
Headache, fever, malaise, myalgia (40%-70%)NoneLocal spread only
Inguinal lymphadenopathyLate, bilateral, nontender, no suppurationEarly, bilateral, tender, no suppurationEarly, rapid, tender, and unilateral; suppuration likely (bubo)Lymphatic obstruction
Primary lesionPapuleVesiclePapule to pustuleSubcutaneous nodule
Ulcer Characteristics
NumberUsually 1Multiple<3>1, may coalesce
EdgesDistinctReddened, raggedSharply demarcated, serpiginous bordersRolled, distinct
DepthShallowShallowShallowRaised
BaseRed, smoothRed, smoothNecroticBeefy red, clean
SecretionSerousSerousPurulentNone
IndurationFirmNoneNoneFirm
PainNoneUsualOftenNone
Diagnosis
SerologyMHA-TP or FTA-ABS; VDRL or RPRSeroconversion (primary infection only)NoneNone
IsolationNo in vitro test; rabbit testes inoculationCultureSwab of ulcer on selective medium, node aspirates usually sterileNone
MicroscopicDark-field examinationPCR or fluorescent antibody stainingGram-negative coccobacilliStaining of ulcer biopsy material for Donovan bodies
TreatmentEarly (primary, secondary and early latent):Benzathine penicillin G (2.4 million U IM) onceAcyclovir or famciclovir or valacyclovirAspirate or excise fluctuant nodesDoxycyclineorazithromycin
Late latent (>1 yr duration): Benzathine penicillin G (2.4 million U IM) weekly × 3 dosesIncision and drainage of buboes >5 cm
Azithromycin or ceftriaxone or ciprofloxacin or erythromycin

FTA-ABS, Fluorescent treponemal antibody-absorption; HSV, herpes simplex virus; IM, intramuscular; MHA-TP, microhemagglutination assay-Treponema pallidum; PCR, polymerase chain reaction; RPR, rapid plasma reagin; VDRL, Venereal Disease Research Laboratory.

From Marcdante KJ et al: Nelson essentials of pediatrics, ed 9, Philadelphia, 2023, Elsevier.

Workup

Diagnosis is based on clinical presentation. Laboratory evaluation confirms diagnosis.

Laboratory Tests

  • •Direct immunofluorescent antibody slide tests provide a rapid diagnosis.
  • •Viral culture is the most definitive method for diagnosis; results are generally available in 1 or 2 days. The lesions should be sampled during the vesicular or early ulcerative stage; cervical samples should be taken from the endocervix with a swab.
  • •Pap smear will detect HSV-infected cells in cervical tissue from women without symptoms.
  • •Serologic tests for HSV: Immunoglobulin (Ig) G and IgM serum antibodies. Antibodies to HSV occur in 50% to 90% of adults. The presence of IgM or a fourfold or greater rise in IgG titers indicates a recent infection (convalescent sample should be drawn 2 to 3 wk after the acute specimen is drawn).
  • •Tzanck smear is a readily available test that will demonstrate multinucleated giant cells. However, it is not a highly sensitive test.

Treatment ⬆ ⬇

TABLE 2 Topical and Oral Antiviral Medications Used for Herpes Simplex Virus Infections*

DrugFormulationRegimenIndication/Comment
Topical
Acyclovir5% cream (2 g, 5 g)Apply 5 times/dayRecurrent HL; A: ≥12 yr; 4 days; Rx
5% ointment (15 g, 30 g)Apply 6 times/dayInitial GH, localized HSV; A: Adults; 7 days; Rx
Penciclovir1% cream (1.5 g, 5 g)Apply q2h (awake)Recurrent HL; A: ≥12 yr; 4 days; Rx
Docosanol10% cream (2 g)Apply 5 times/dayHL; A: ≥12 yr; treat until healed; OTC
Oral (all Rx)
Acyclovir200-mg capsuleA: ≥2 yr
400-mg, 800-mg tablet
200-mg/5-ml susp
200 mg 5 times/dayInitial GH; 10 days
200 mg 5 times/dayRecurrent GH; 5 days
400 mg 2 times/daySuppression, recurrent GH; up to 12 mo, then reevaluate
Famciclovir125-, 250-, 500-mg tabletA: ≥18 yr
1500-mg single doseRecurrent HL
1000 mg 2 times/dayRecurrent GH; 1 day
250 mg 2 times/daySuppression, recurrent GH; up to 12 mo
Valacyclovir500-mg, 1-g capletA: Adults and ≥12 yr for HL
1 g 2 times/dayInitial GH; 10 days
500 mg 2 times/dayRecurrent GH; 3 days
500 mg-1 g once dailySuppressive GH
2 g 2 times/dayHL; 1 day; both adults and children ≥12 yr

A, Approved; GH, genital herpes; HL, herpes labialis; HSV, herpes simplex virus; OTC, over-the-counter; Rx, by prescription.

* Approved indications and regimens listed; often used off-label.

From Paller AS, Mancini AJ: Hurwitz clinical pediatric dermatology: a textbook of skin disorders of childhood and adolescence, ed 5, Philadelphia, 2016, Elsevier.

TABLE 3 Antiviral Treatment for Herpes Simplex Virus in the Nonpregnant Patient

Antiviral Agent
IndicationValacyclovirAcyclovirFamciclovir
First clinical episode1000 mg bid, 7-10 days400 mg tid; or 200 mg five times/day, 7-10 days250 mg tid, 7-10 days
Recurrent episodes1000 mg daily, 5 days; or 500 mg bid, 3 days800 mg bid, 5 days; or 800 mg tid, 2 days
  • 125 mg bid, 5 days
  • 500 mg once then 250 mg bid, 2 days; 1000 mg bid, 1 day
Daily suppressive1000 mg daily (≥10 recurrences/yr) or 500 mg daily (≤9 recurrences/yr)400 mg bid250 mg bid

bid, Twice per day; tid, three times per day.

Data from Workowski KA, Bolan GA: Centers for Disease Control and Prevention: sexually transmitted diseases treatment guidelines, 2015, MMWR Recomm Rep 64(RR-03):1-137, 2015; Gershenson DM et al: Comprehensive gynecology, ed 8, Philadelphia, 2022, Elsevier.

Disposition

Most patients recover from the initial episode or recurrences without complications; immunocompromised hosts are at risk for complications (e.g., disseminated herpes simplex infection, herpes encephalitis).

Referral

  • •Hospital admission in patients with herpes encephalitis or herpes meningitis and in immunocompromised hosts with diffuse herpes simplex infection
  • •Ophthalmology referral in patients with suspected ocular herpes

Pearls & Considerations ⬆

Comments

  • •Provide patient education regarding transmission of HSV.
  • •Condom use offers significant protection against HSV-1 infection in susceptible women.
  • •Patients should be instructed on the use of condoms for sexual intercourse and on avoiding kissing or sexual intercourse until lesions are crusted. Pericoital application of tenofovir gel, an antiretroviral vaginal gel, has also been shown to reduce the risk of HSV-2 in women. This may be useful in regions of the world where use of condoms is shunned.
  • •Patients should also avoid contact with immunocompromised hosts or neonates while lesions are present.
  • •Proper handwashing techniques should be explained.
  • •Patients with herpes gladiatorum (cutaneous herpes in athletes involved in contact sports) should be excluded from participation in active sports until lesions have resolved.
  • •Many new HSV-2 infections are asymptomatic. Since HSV-2 antibody tests have become commercially available, an increasing number of persons have learned that they have genital herpes through serologic testing. Persons with asymptomatic HSV-2 infection shed virus in the genital tract less frequently than persons with symptomatic infection, but much of the difference is attributable to less frequent genital lesions because genital lesions are accompanied by frequent viral shedding. The U.S. Preventive Services Task Force (USPSTF) recommends against routine serologic screening for genital HSV infection in asymptomatic adolescents and adults, including those that are pregnant.
  • •Suppressive treatment of HSV-2 infection lowers the incidence of genital lesions by 70% to 80% but cuts the rate of HSV-2 transmission to uninfected partners by only 50%.
  • •Pregnancy: Antiviral prophylaxis with acyclovir is recommended from 36 wk of gestation until delivery in women with a history of genital herpes. Elective cesarean delivery should be performed in laboring patients with active lesions to decrease the risk of neonatal herpes.
  • •Trials involving investigational herpes simplex vaccine have found it to be effective in preventing HSV-1 genital disease and infection, but not in preventing HSV-2 disease or infection.
Related Content

  • Genital Herpes (Patient Information)
  • Oral Herpes (Patient Information)