section name header

Basic Information ⬇

Author: Glenn G. Fort, MD, MPH

Definition

Histoplasmosis is caused by the fungus Histoplasma capsulatum and characterized by a primary pulmonary focus with occasional progression to chronic pulmonary histoplasmosis (CPH) or various forms of dissemination. Progressive disseminated histoplasmosis (PDH) may present with a diverse clinical spectrum, including adrenal necrosis, pulmonary and mediastinal fibrosis, and ulcerations of the oropharynx and GI tract. In those patients coinfected with HIV, it is a defining disease for AIDS.

Synonyms

  • North American histoplasmosis
  • Ohio Valley fever
  • Vanderbilt disease
Epidemiology & Demographics
Incidence (In U.S.):

  • •Unknown for acute pulmonary disease
  • •For CPH, estimated at 1/100,000 cases in endemic areas
  • •For PDH in immunocompetent adults, estimated at 1/2000 cases of histoplasmosis
Prevalence:

Unknown

Predominant Sex:

Clinically evident disease is most common in males; male:female ratio of 4:1

Predominant Age:

  • •CPH is most often seen in males >50 yr old with an associated history of COPD.
  • •Presumed ocular histoplasmosis syndrome (POHS) is seen between ages of 20 and 40 yr.
Peak Incidence:

Unknown

Physical Findings & Clinical Presentation

  • •Conidia are deposited in alveoli, then converted to yeast forms where they spread to regional lymph nodes and other organs, especially liver and spleen.
  • •1 to 2 wk later, a granulomatous inflammatory response begins to contain the yeast in the form of discrete granulomas.
  • •Delayed-type hypersensitivity to Histoplasma antigens occurs 3 to 6 wk after exposure.
  • •Clinical disease manifests in various forms (Box E1), depending on host cellular immunity and inoculum size:
    1. 1.Acute primary pulmonary histoplasmosis:
      1. a.An overwhelming number of patients are asymptomatic.
      2. b.Most clinically apparent infections manifest by complaints of fever, headache, malaise, pleuritic chest pain, nonproductive cough, and weight loss.
      3. c.Less than 10%, mainly women, complain of arthralgias, myalgias, and skin manifestations such as erythema multiforme or erythema nodosum (Fig. E1).
      4. d.Acute pericarditis presents in a smaller percentage of patients.
      5. e.Hepatosplenomegaly is most commonly observed in children.
      6. f.With particularly heavy exposure, there is severe dyspnea, marked hypoxemia, impending respiratory failure.
      7. Most patients are asymptomatic within 6 wk.
    2. 2.CPH: Chronic pulmonary histoplasmosis
      1. a.Presents insidiously with low-grade fever, malaise, weight loss, cough, sometimes with blood-streaked sputum or frank hemoptysis.
      2. b.Most patients with cavitary lesions present with associated COPD or chronic bronchitis, masking underlying fungal disease.
      3. c.Tends to worsen preexisting pulmonary disease and further contribute to eventual respiratory insufficiency.
    3. 3.PDH: Progressive disseminated histoplasmosis
      1. a.In both acute and subacute forms, constitutional symptoms of fever, fatigue, malaise, and weight loss are common.
      2. b.Acute form (seen in infants and children) presents with respiratory symptoms, fever ≥101° F (38.3° C), generalized lymphadenopathy, marked hepatosplenomegaly, and fulminant course resembling septic shock associated with a high fatality rate.
      3. c.Subacute form is more common in adults and associated with lower temperatures, hepatosplenomegaly, oropharyngeal ulceration, focal organ involvement (including adrenal destruction, endocarditis, chronic meningitis, and intracerebral mass lesions).
      4. d.Course of subacute form is relentless, with untreated patients dying within 2 yr.
      5. e.Chronic PDH is found in adults and marked by gradual symptoms of weight loss, weakness, easy fatigability; low-grade fever when present; oropharyngeal ulcerations and hepatomegaly and/or splenomegaly in one third of patients.
      6. f.Less clinical evidence of focal organ involvement in chronic form than in subacute form.
      7. g.Natural history of chronic form is protracted and intermittent, spanning months to years.
  • •Histoplasmoma:
    1. 1.A healed area of caseation necrosis surrounded by a fibrous capsule
    2. 2.Usually asymptomatic
  • •Mediastinal fibrosis:
    1. 1.A rare consequence of a fibroblastic process that encases caseating mediastinal lymph nodes producing severe retraction, compression, and distortion of mediastinal structures
    2. 2.Constriction of the bronchi resulting in bronchiectasis, also esophageal stenosis associated with dysphagia, and superior vena cava syndrome
  • •POHS: Presumed ocular histoplasmosis syndrome
    1. 1.Diagnosis characterized by distinct clinical features, including atrophic choroidal scars and maculopathy in patients with histories suggestive of exposure to the fungus (e.g., residence in an endemic area)
    2. 2.Patient complains of distortion or loss of central vision without pain, redness, or photophobia
    3. 3.Usually no evidence of infection except for a positive skin reaction to histoplasmin
  • •In patients with AIDS:
    1. 1.Possible presentation as overwhelming infection similar to acute PDH seen in children
    2. 2.Constitutional symptoms: Fever, weight loss, malaise, cough, dyspnea
    3. 3.About 10% with cutaneous maculopapular, erythematous eruptions or purpuric lesions on face, trunk, and extremities
    4. 4.Up to 20% with CNS involvement, manifesting as intracerebral mass lesions, chronic meningitis, or encephalopathy

Figure E1 Erythema nodosum in an adolescent boy with pulmonary histoplasmosis.
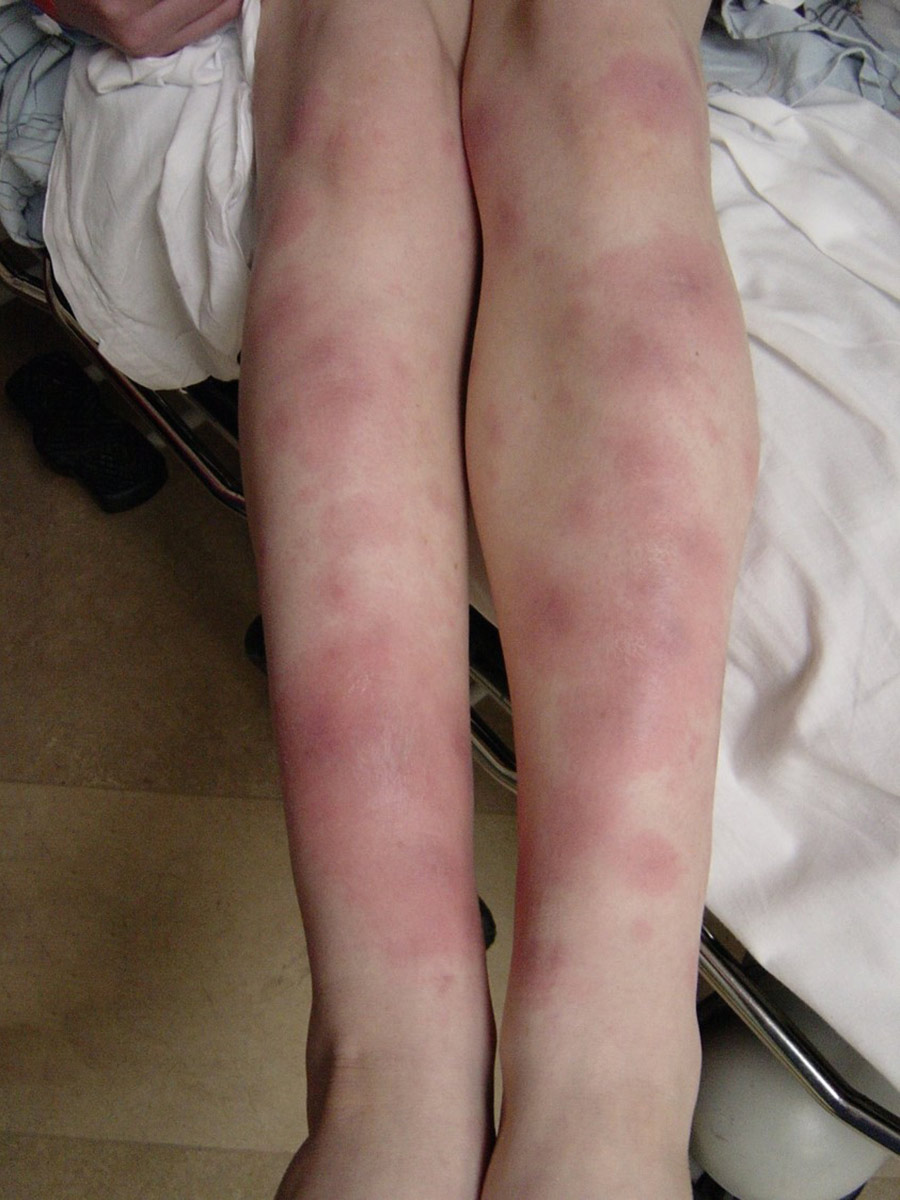
(From Cherry JD et al: Feigin and Cherry’s pediatric infectious diseases, ed 8, Philadelphia, 2019, Elsevier.)

BOX E1 Clinical Manifestations of Histoplasmosis

  • •Asymptomatic infection
  • •Pneumonia
  • •Progressive disseminated infection (HIV, immunocompromise, infancy)
  • •Mediastinal lymphadenopathy
  • •Cavitary pneumonia*
  • •Asthma-like illness
  • •Pleural effusion or granulomatous pleuritis*
  • •Obstruction or dysfunction of contiguous mediastinal structures (bronchi, esophagus) by granulomatous inflammation of lymph nodes (mediastinal granuloma)
  • •Isolated cervical or supraclavicular lymphadenopathy*
  • •Superior vena cava syndrome*
  • •Mediastinal fibrosis*
  • •Vocal cord granuloma
  • •Vocal cord paralysis
  • •Hemoptysis
  • •Broncholithiasis with lithoptysis*
  • •Chylothorax*
  • •Diaphragmatic weakness or paralysis
  • •Esophageal diverticulum or fistula
  • •Pericarditis
  • •Erythema nodosum
  • •Meningitis or focal cerebritis*
  • •Arthritis or arthralgias
  • •Parotitis
  • •Nephrocalcinosis
  • •Interstitial nephritis*
  • •Hypercalcemia
  • •Gastrointestinal tract ulceration or hemorrhage
  • •Gastrointestinal tract pseudomalignancy
  • •Crohn disease-like illness
  • •Biliary obstruction*
  • •Ocular histoplasmosis, choroiditis*
  • •Endocarditis*
  • •Adrenal mass*

From Cherry JD et al: Feigin and Cherry’s pediatric infectious diseases, ed 8, Philadelphia, 2019, Elsevier.

Etiology

  • •H. capsulatum is a dimorphic fungus present in temperate zones and river valleys worldwide.
  • •In the U.S., it is highly endemic in southeastern, mid-Atlantic, and central states (Ohio and Mississippi River valleys). Outside the U.S. it is distributed in Central and South America, the Caribbean, and in regions of Australia, India, and Africa.
  • •Exists as mold at ambient temperature and favors soils enriched with bird or bat droppings.

* Rare in children.

Diagnosis ⬆ ⬇

Differential Diagnosis

  • •Acute pulmonary histoplasmosis:
    1. 1.Mycobacterium tuberculosis
    2. 2.Community-acquired pneumonias caused by Mycoplasma and Chlamydia
    3. 3.Other fungal diseases, such as those caused by Blastomyces dermatitidis and Coccidioides immitis
  • •Chronic cavitary pulmonary histoplasmosis: M. tuberculosis
  • •Histoplasmomas: True neoplasms
  • •Sarcoidosis
Workup

  • •Suspect diagnosis in patients who present with a history of residence or travel in an endemic area, especially if engaged in occupations (e.g., outside construction or street cleaning) or hobbies (e.g., cave exploring) that increase the likelihood of exposure to fungal spores.
  • •Suspect diagnosis in immunosuppressed patients with remote history of exposure, especially if associated with characteristic calcifications on chest x-ray.
  • •Diagnostics for histoplasmosis are summarized in Table E1.

TABLE E1 Diagnostics for Histoplasmosis

Infection SiteDisease SeverityDiagnostic
Lung
AcuteMild-moderateH and M bands and complement fixation.
Moderate to severeAs above. Serum or urine antigen, or both, also may be positive in up to 70%. Bronchoalveolar fluid antigen may be useful. Culture of bronchoalveolar lavage fluid and silver stain of concentrated lavage fluid. Sputum culture.
Chronic cavitaryH and M bands and complement fixation. Culture of bronchoalveolar lavage fluid and silver stain of concentrated lavage fluid. Sputum cultures.
Disseminated
AcuteSerum or urine antigen, or both. H and M bands and complement fixation. These are not useful in AIDS patients. Examination of the buffy coat for yeast cells in phagocytes. Biopsy of bone marrow or liver with silver stain and culture. Blood culture.
ChronicSerum or urine antigen, or both. H and M bands and complement fixation. Biopsy of tissue with silver stain and culture.
Central nervous systemSerum or urine antigen, or both. CSF antigen. Culture of CSF. H and M bands and complement fixation are not as useful.
Mediastinal
LymphadenitisH and M bands and complement fixation.
GranulomaH and M bands and complement fixation.
FibrosisH and M bands and complement fixation.
RheumatologicArthralgiasH and M bands and complement fixation.
PericarditisH and M bands and complement fixation.
Endocarditis or endovascularH and M bands and complement fixation. Serum or urine antigen, or both. Culture and silver stain of valve.

AIDS, Acquired immunodeficiency syndrome; CSF, cerebrospinal fluid.

From Bennett JE et al: Mandell, Douglas, and Bennett’s principles and practice of infectious diseases, ed 9, Philadelphia, 2020, Elsevier.

Laboratory Tests

  • •Detection of Histoplasma antigen in serum and urine. Urine antigen is 75% accurate in normal hosts and 95% in immunocompromised patients with disseminated disease. The sensitivity and specificity of the urinary antigen is also dependent on the stage of infection exceeding 80% in acute and disseminated infection but decreasing to less than 50% in chronic infection. The serum test is close to 100% accurate, but with Blastomyces and Coccidioides, tests may cross-react with infections. Tests can also be performed on bronchoalveolar lavage.
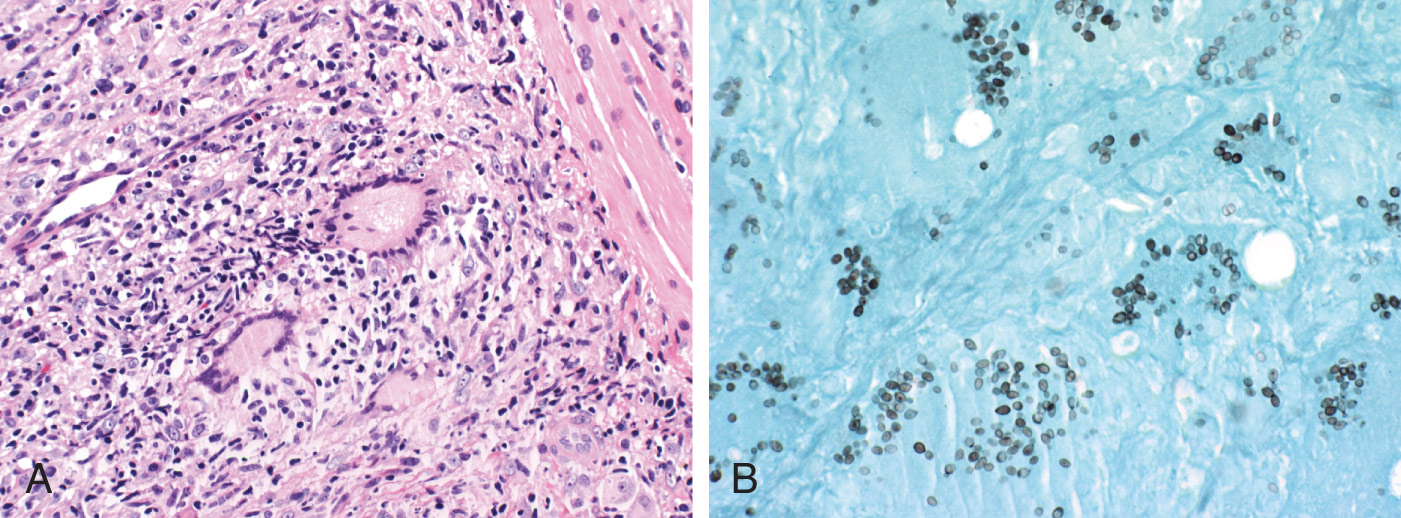
  • •Demonstration of organism on culture from body fluid or tissues biopsy (Fig. E2) will confirm the diagnosis in clinically suspected cases and negative urinary antigen.
    1. 1.Especially high yield in patients with AIDS
    2. 2.Characteristic oval yeast cells in neutrophils with Giemsa stain from peripheral smear
    3. 3.Preparations of infected tissue with Gomori silver methenamine for revealing yeast forms, especially in areas of caseation necrosis
  • •Serologic tests, including complement-fixing (CF) antibodies and immunodiffusion assays.
  • •In PDH:
    1. 1.Pancytopenia
    2. 2.Marked elevations in alkaline phosphatase and alanine aminotransferase (ALT) common
  • •In chronic meningitis (majority of cases):
    1. 1.CSF pleocytosis with either lymphocytes or neutrophils predominating
    2. 2.Elevated CSF protein levels
    3. 3.Hypoglycorrhachia

Figure E2 A, Photomicrograph Shows a Tissue Biopsy Specimen from a Patient with Slowly Progressing Disseminated Histoplasmosis

Granulomas are Well Formed, and No Organisms are Seen. Hematoxylin and Eosin Stain, ×450. B, Special Stains Better Demonstrate Yeast in Tissue Sections. Silver Methenamine Stain, ×450.

(From Mason RJ: Murray & Nadel’s textbook of respiratory medicine, ed 5, Philadelphia, 2010, Saunders.)

Imaging Studies

  • •Chest x-ray in acute pulmonary histoplasmosis:
    1. 1.Singular or multiple patchy infiltrates, especially in the lower lung fields
    2. 2.Hilar or mediastinal lymphadenopathy with or without pneumonitis
    3. 3.Diffuse nodular or confluent bilateral miliary infiltrates characteristic of heavier exposure
    4. 4.Infrequent pleural effusions, except when associated with pericarditis
  • •Chest x-ray in histoplasmoma: Coin lesion displaying central calcification, ranging from 1 to 4 cm in diameter, predominantly located in the subpleural regions
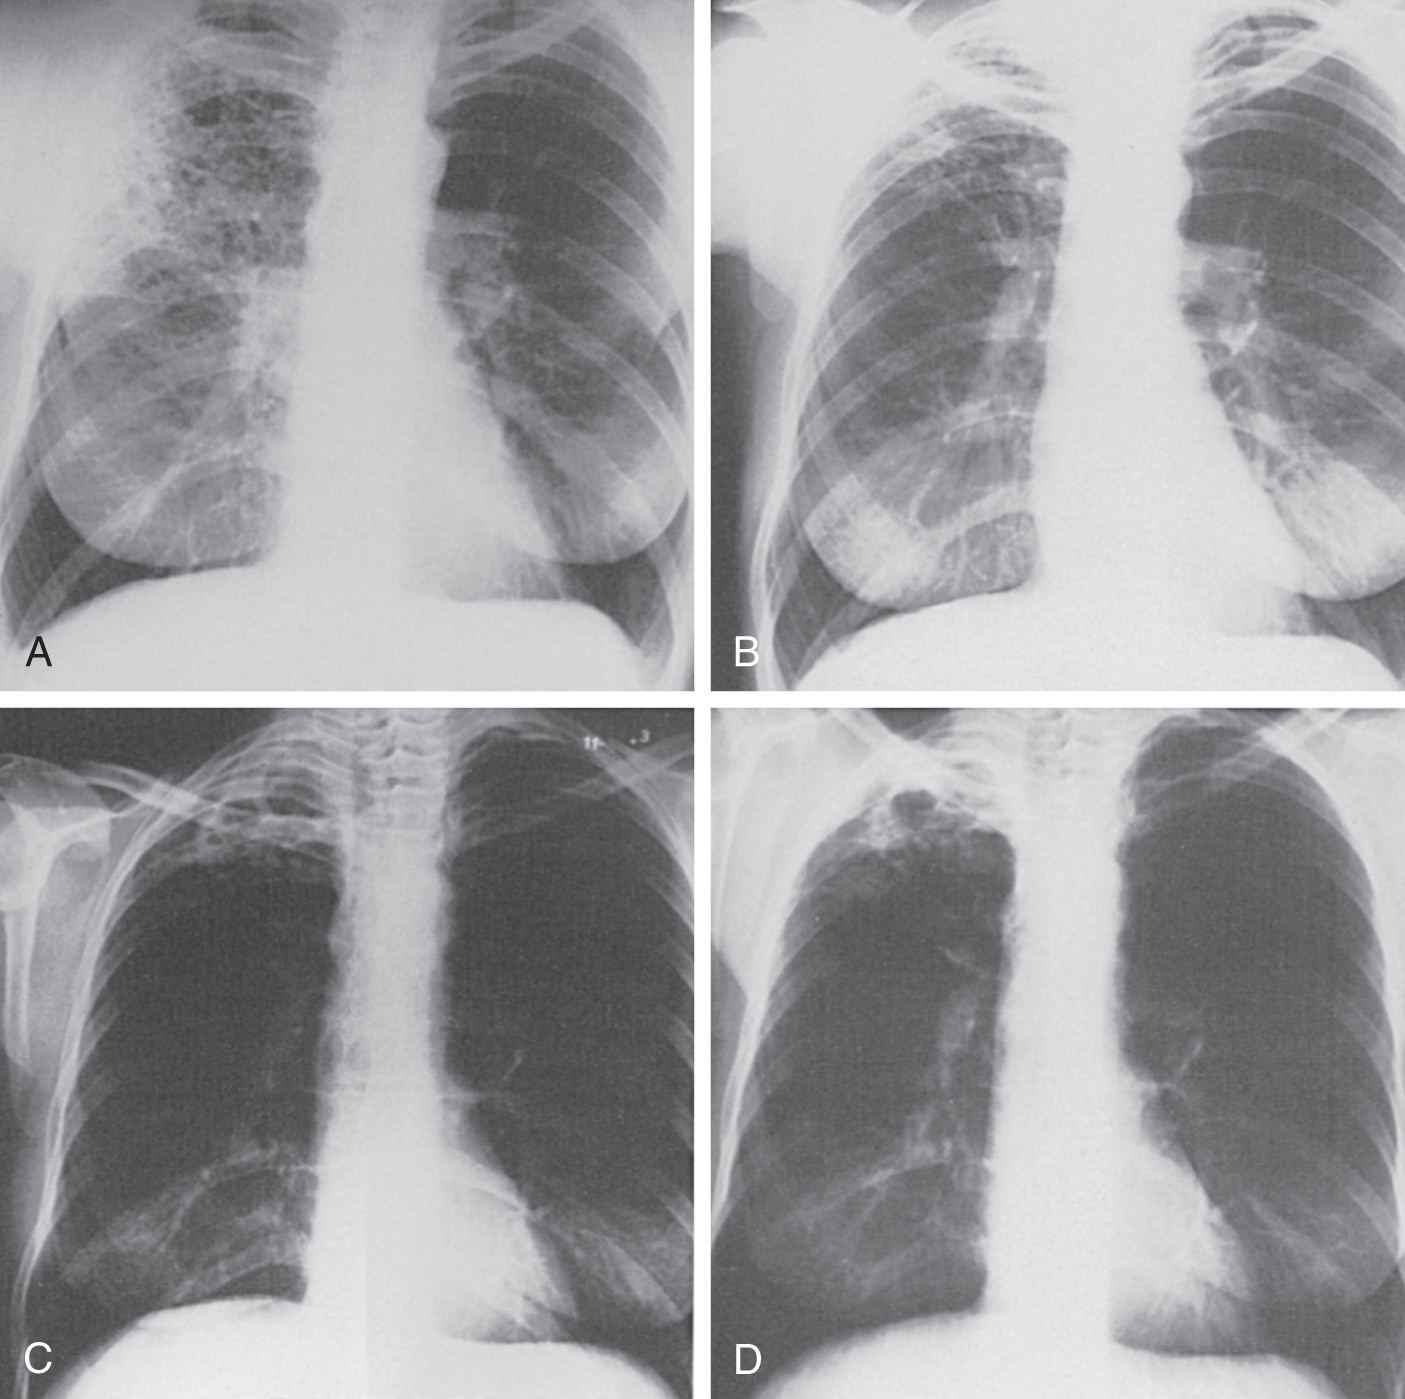
  • •Chest x-ray in CPH (Fig. E3):
    1. 1.Upper lobe disease frequently associated with cavities
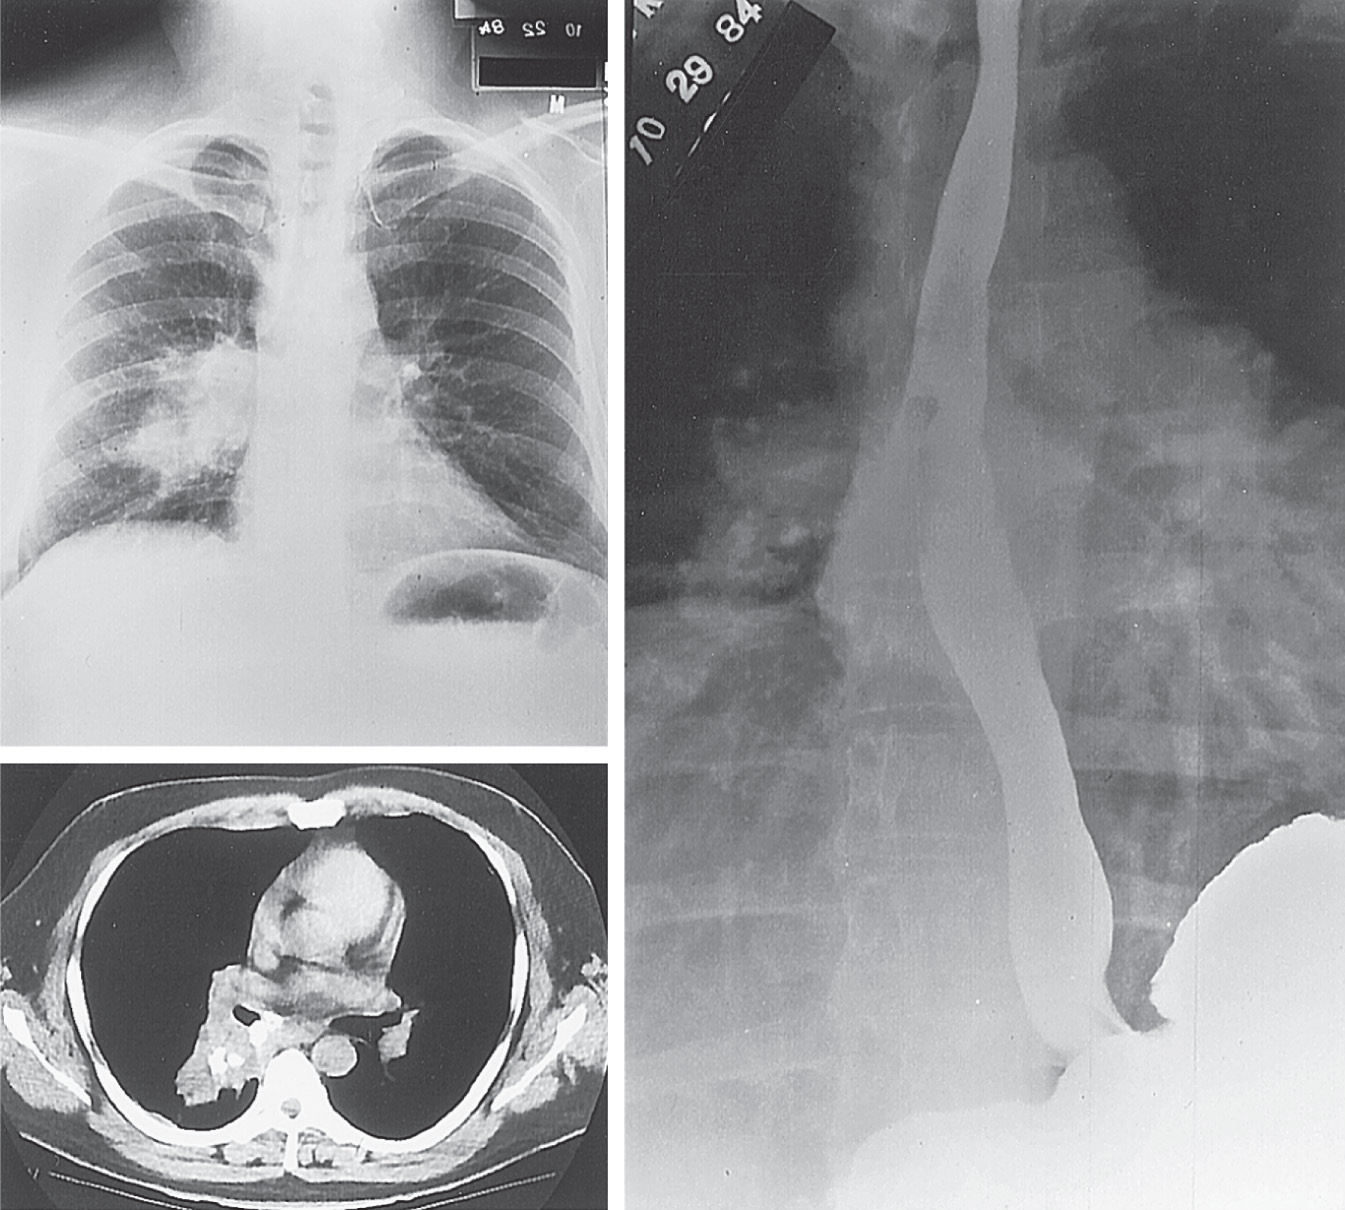
    2. 2.Preexisting calcifications in the hilum associated with peribronchial streaking extending to the parenchyma (Fig. E4)
  • •Chest x-ray in acute PDH: Hilar adenopathy and/or diffuse nodular infiltrates
  • •CT scan of adrenals to reveal bilateral enlargement and low-attenuation center

Figure E4 Computed Tomography, Contrast Esophagography, and Chest Radiography Demonstrating Calcified Mediastinal Granulomatous Disease Secondary to Histoplasmosis, with Erosion into the Adjacent Esophagus

(From Sellke FW et al: Sabiston and Spencer: surgery of the chest, ed 10, Philadelphia, 2024. Elsevier.)

Figure E3 The evolution of chronic pulmonary histoplasmosis in a smoker.

A, At the onset of the illness, the chest radiograph shows multiple cavity-like air spaces. B, 2.5 yr later, fibrosis has occurred with volume loss of the lobe and retraction of the hilum. C, A further 17 mo later, the entire right upper lobe appears to be destroyed. D, There are signs of continued activity and a residual cavity at the time of diagnosis. The sputum culture was positive for Histoplasma capsulatum.

(From Mason RJ: Murray & Nadel’s textbook of respiratory medicine, ed 5, Philadelphia, 2010, Saunders.)

Treatment ⬆ ⬇

Treatment (Table E2)
Nonpharmacologic Therapy

For life-threatening disease seen in acute disseminated disease or infection in patients with AIDS: Supportive therapy with intravenous (IV) fluids

TABLE E2 Treatment of Histoplasmosis

Infection SiteDisease SeverityTreatment
Lung
AcuteMild-moderateNone or itraconazole 200 mg 3 times daily for 3 days followed by 200 mg twice a day for 6-12 wk.
Moderate-severeLipid-formulated amphotericin B, 3-5 mg/kg, or deoxycholate amphotericin B, 0.7-1 mg/kg, daily for 1-2 wk followed by itraconazole 200 mg 3 times a day for 3 days followed by 200 mg twice a day for a total duration of 12 wk. For children, itraconazole 5-10 mg/kg or deoxycholate amphotericin B, 1 mg/kg daily.
Chronic cavitaryItraconazole 200 mg 3 times a day for 3 days followed by twice daily for at least 1 yr and as long as 2 yr.
Disseminated
AcuteLipid-formulated amphotericin B, 3-5 mg/kg, or deoxycholate amphotericin B, 0.7-1 mg/kg, daily for 1-2 wk followed by itraconazole 200 mg 3 times a day for 3 days followed by 200 mg twice a day for at least 12 mo. For children, deoxycholate amphotericin B (1 mg/kg) daily for 4-6 wk or 2-4 wk followed by itraconazole 5-10 mg/kg daily. Total duration = 3 mo.
ChronicItraconazole 200 mg 3 times a day for 3 days followed by 200 mg twice a day for at least 1 yr. Serum levels should be monitored to ensure adequate concentrations.
Central nervous systemLiposomal amphotericin B, 5 mg/kg daily for 4-6 wk followed by itraconazole administered as above for at least 1 yr and resolution of symptoms and negative cerebrospinal fluid antigen.
Mediastinal
LymphadenitisNo treatment. If symptomatic (e.g., dysphagia), itraconazole 200 mg twice daily for 12 wk. Corticosteroids (60 mg with a rapid taper) may be used to diminish lymph node size.
GranulomaSame as lymphadenitis. Corticosteroids are not necessary.
FibrosisSurgical intervention with stents. Antifungals are not useful.
RheumatologicArthralgias, etc.Nonsteroidals.
PericarditisNonsteroidals or corticosteroids. If the latter, treat with itraconazole (200 mg × 3 for 3 days and then once a day) until corticosteroids have been discontinued.
Endocarditis/endovascularSurgical removal of the valve combined with lipid-formulated amphotericin B, 5 mg/kg daily for 6 wk. Lifelong suppression may be considered in some who are not surgical candidates with itraconazole 200 mg once or twice a day.

Data from Wheat LJ et al: Clinical practice guidelines for the management of patients with histoplasmosis: 2007 update by the Infectious Diseases Society of America, Clin Infect Dis 45:807-825, 2007.

Acute General Rx

  • •No drug therapy is required for asymptomatic pulmonary disease
  • •A course of therapy with itraconazole 200 mg PO tid for 3 days, then 200 mg/day PO for 6 to 12 wk may be beneficial in some patients with acute pulmonary distress. Avoid fluconazole because it is not as active
  • •Same therapy appropriate for immunocompetent, mild to moderately symptomatic patients with CPH and subacute and chronic forms of PDH, but duration for 6 to 12 mo
  • •Use amphotericin B 0.7 to 1 mg/kg IV daily for initial therapy in moderate to severe disease and then transition to oral itraconazole within 1 to 2 wk. Lipid formulations of amphotericin can be used to avoid nephrotoxicity of amphotericin B, and they produce better outcomes in terms of mortality, rates of culture conversion, and side effects
  • •Liposomal amphotericin: 3 mg/kg/day IV or amphotericin B lipid complex: 5 mg/kg/day
  • •Posaconazole is highly effective as well: Delayed-release tablets 300 mg PO bid × 2 doses then 300 mg PO daily or suspension: 200 mg qid then 400 mg PO bid after stabilization of disease
  • •Voriconazole is less active in vitro than itraconazole: 6 mg/kg PO bid × 2 doses then 4 mg/kg PO bid
  • •Isavuconazole: 372 mg PO/IV q8h × 6 doses and then 372 mg PO/IV daily
  • •Note that echinocandins such as micafungin are not effective
  • •Chronic cavitary pulmonary histoplasmosis: Itraconazole 200 mg PO tid for 3 days, then once or twice daily for at least 12 mo
  • •CNS histoplasmosis: Liposomal amphotericin B, 5 mg/kg/day for a total of 175 mg/kg over 4 to 6 wk, then itraconazole 200 mg 2 to 3×/day for at least 12 mo
  • •Endocarditis: Surgical treatment with excision of infected valve or graft combined with amphotericin for a total dose of 35 mg/kg or 2.5 g
  • •For pericardial disease:
    1. 1.Antifungal therapy: No apparent benefit
    2. 2.Best managed with NSAIDs
  • •For POHS:
    1. 1.Antifungal therapy: No apparent benefit
    2. 2.May respond to laser therapy
Chronic Rx

  • •In patients with AIDS: Lifelong suppressive therapy with either itraconazole, given 200 mg PO daily, or IV amphotericin B at a dose of 50 mg once weekly; a triazole compound posaconazole (400 mg PO bid) may be useful in refractory cases, but clinical experience is limited at this point.
  • •Prophylaxis with itraconazole 200 mg PO daily is indicated in solid organ transplants, patients receiving TNF inhibitors, and HIV-infected patients with <150 CD4 cells/mm3 living in a community with a hyperendemic rate of histoplasmosis (MMWR 58[RR-4]:1, 2009).
Disposition

For those with chronic or progressive disease, especially if immunocompromised, prognosis is dependent on prompt recognition and timely administration of appropriate antifungal drugs.

Referral

  • •To an infectious disease specialist in suspected cases of disseminated disease, especially if immunocompromised
  • •To a pulmonologist for patients with CPH form because of progressive respiratory compromise
  • •To a thoracic surgeon for decompression procedures for progressive mediastinal fibrosis

Pearls & Considerations ⬆

Comments

  • •Patients living in endemic areas, especially if immunocompromised, should take appropriate respiratory precautions when disposing of bird waste from rooftop or home aviaries.
  • •Appropriate respiratory precautions should also be taken when leisure traveling to areas that act as a natural haven for the fungus, such as bat caves.
Related Content

  • Histoplasmosis (Patient Information)