Author: Shiva Kumar R. Mukkamalla, MD, MPH


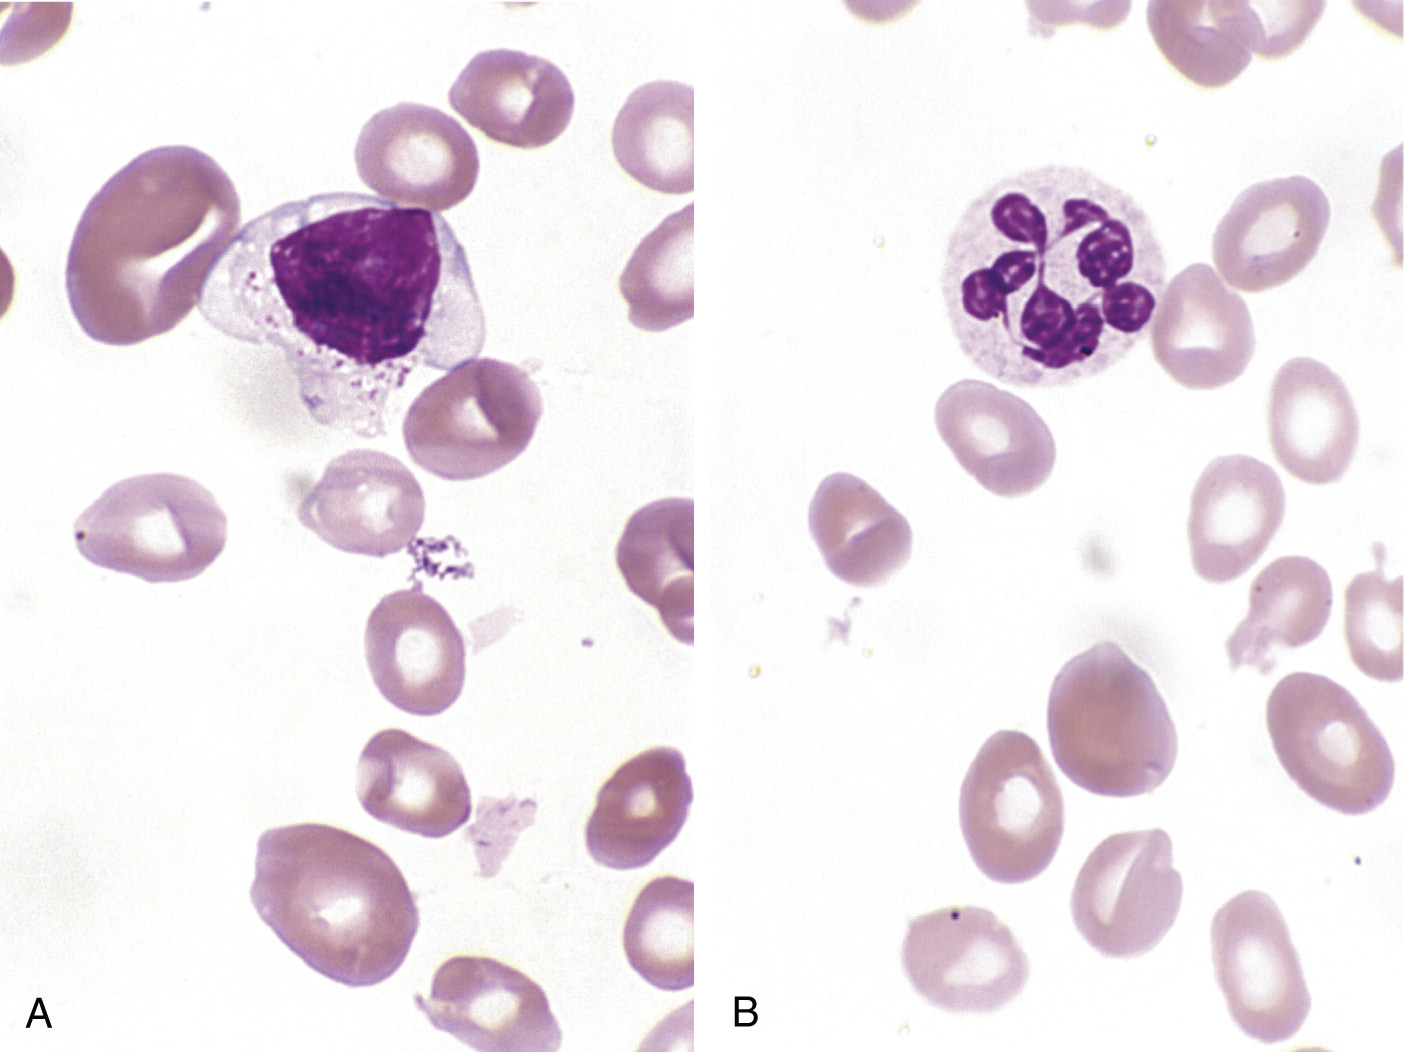
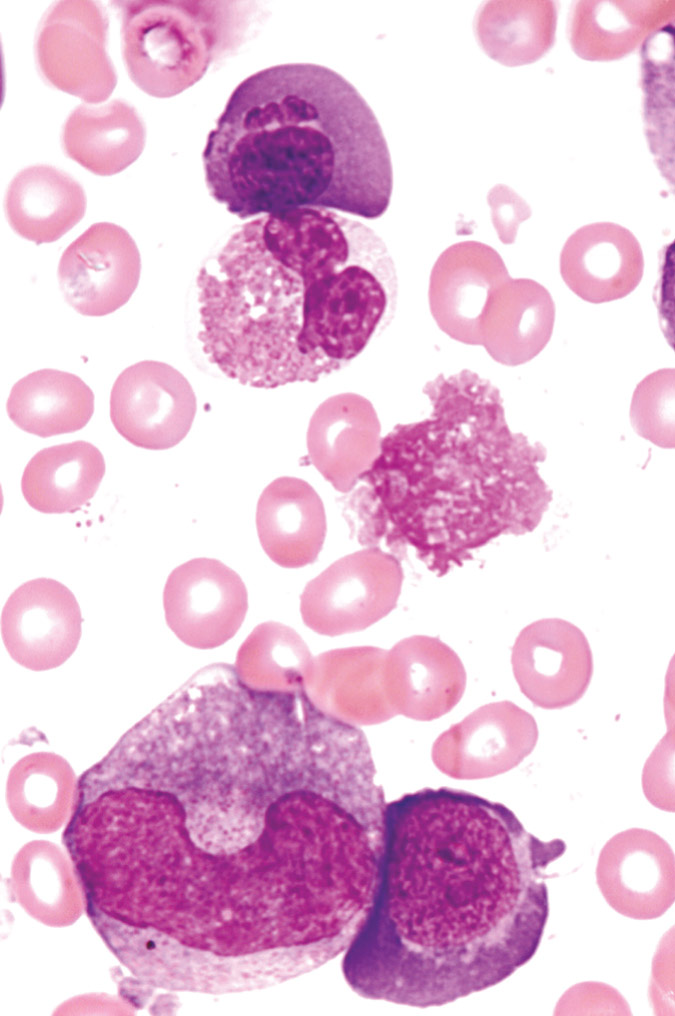
Pernicious anemia (PA) is an autoimmune disease resulting from antibodies against gastric intrinsic factor and gastric parietal cells that results in vitamin B12 deficiency due to decreased absorption and leading to megaloblastic anemia. Pernicious anemia also manifests with neurologic symptoms.
| ICD-10CM CODES | |||
| D51.0 | Vitamin B12 deficiency anemia due to intrinsic factor deficiency | ||
| D51.8 | Other vitamin B12 deficiency anemias | ||
| D51.9 | Vitamin B12 deficiency anemia, unspecified | ||
| D51.1 | Vitamin B12 deficiency anemia due to selective vitamin B12 malabsorption with proteinuria | ||
- •Increased incidence in females and older adults (40 to 70 yr)
- •More frequent in patients of northern European ancestry
- •Overall prevalence of undiagnosed PA after age 60 yr is 1.9%
- •Prevalence is higher in women (2.7%), particularly in Black women (4.3%)
- •Associated with other autoimmune diseases (e.g., type 1 diabetes mellitus, Graves disease, Addison disease), along with possible Helicobacter pylori association
- •Mucosal pallor and/or glossitis ("beefy red tongue")
- •Angular cheilosis
- •Mild jaundice (representative of intramedullary hemolysis of megaloblastic cells); "lemon yellow" skin due to pallor and jaundice
- •Peripheral sensory neuropathy with paresthesia initially and absent reflexes in advanced disease
- •Delirium or dementia
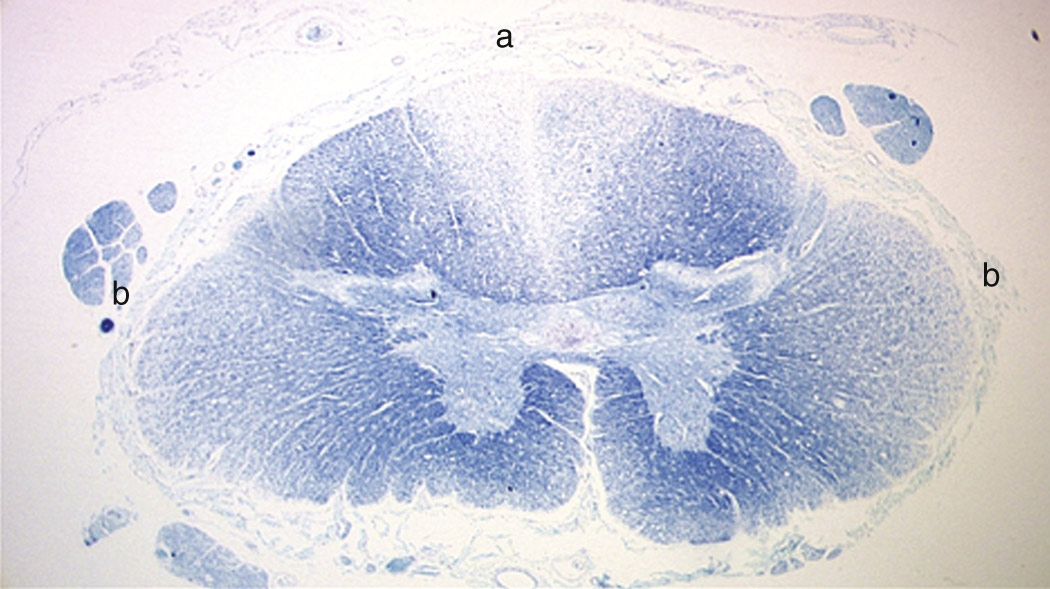
- •Worsening weakness and possible subacute combined degeneration of spinal cord (Fig. E1)
- •Loss of proprioception and an unsteady gait
- •GI symptoms including anorexia, pyrosis, nausea, and vomiting
- •Possible splenomegaly and mild hepatomegaly
- •Parietal cell antibodies are present in >70% of patients, while intrinsic factor antibodies are noted in >50% of patients.
- •Atrophic gastric mucosa (Fig. E2) with achlorhydria.
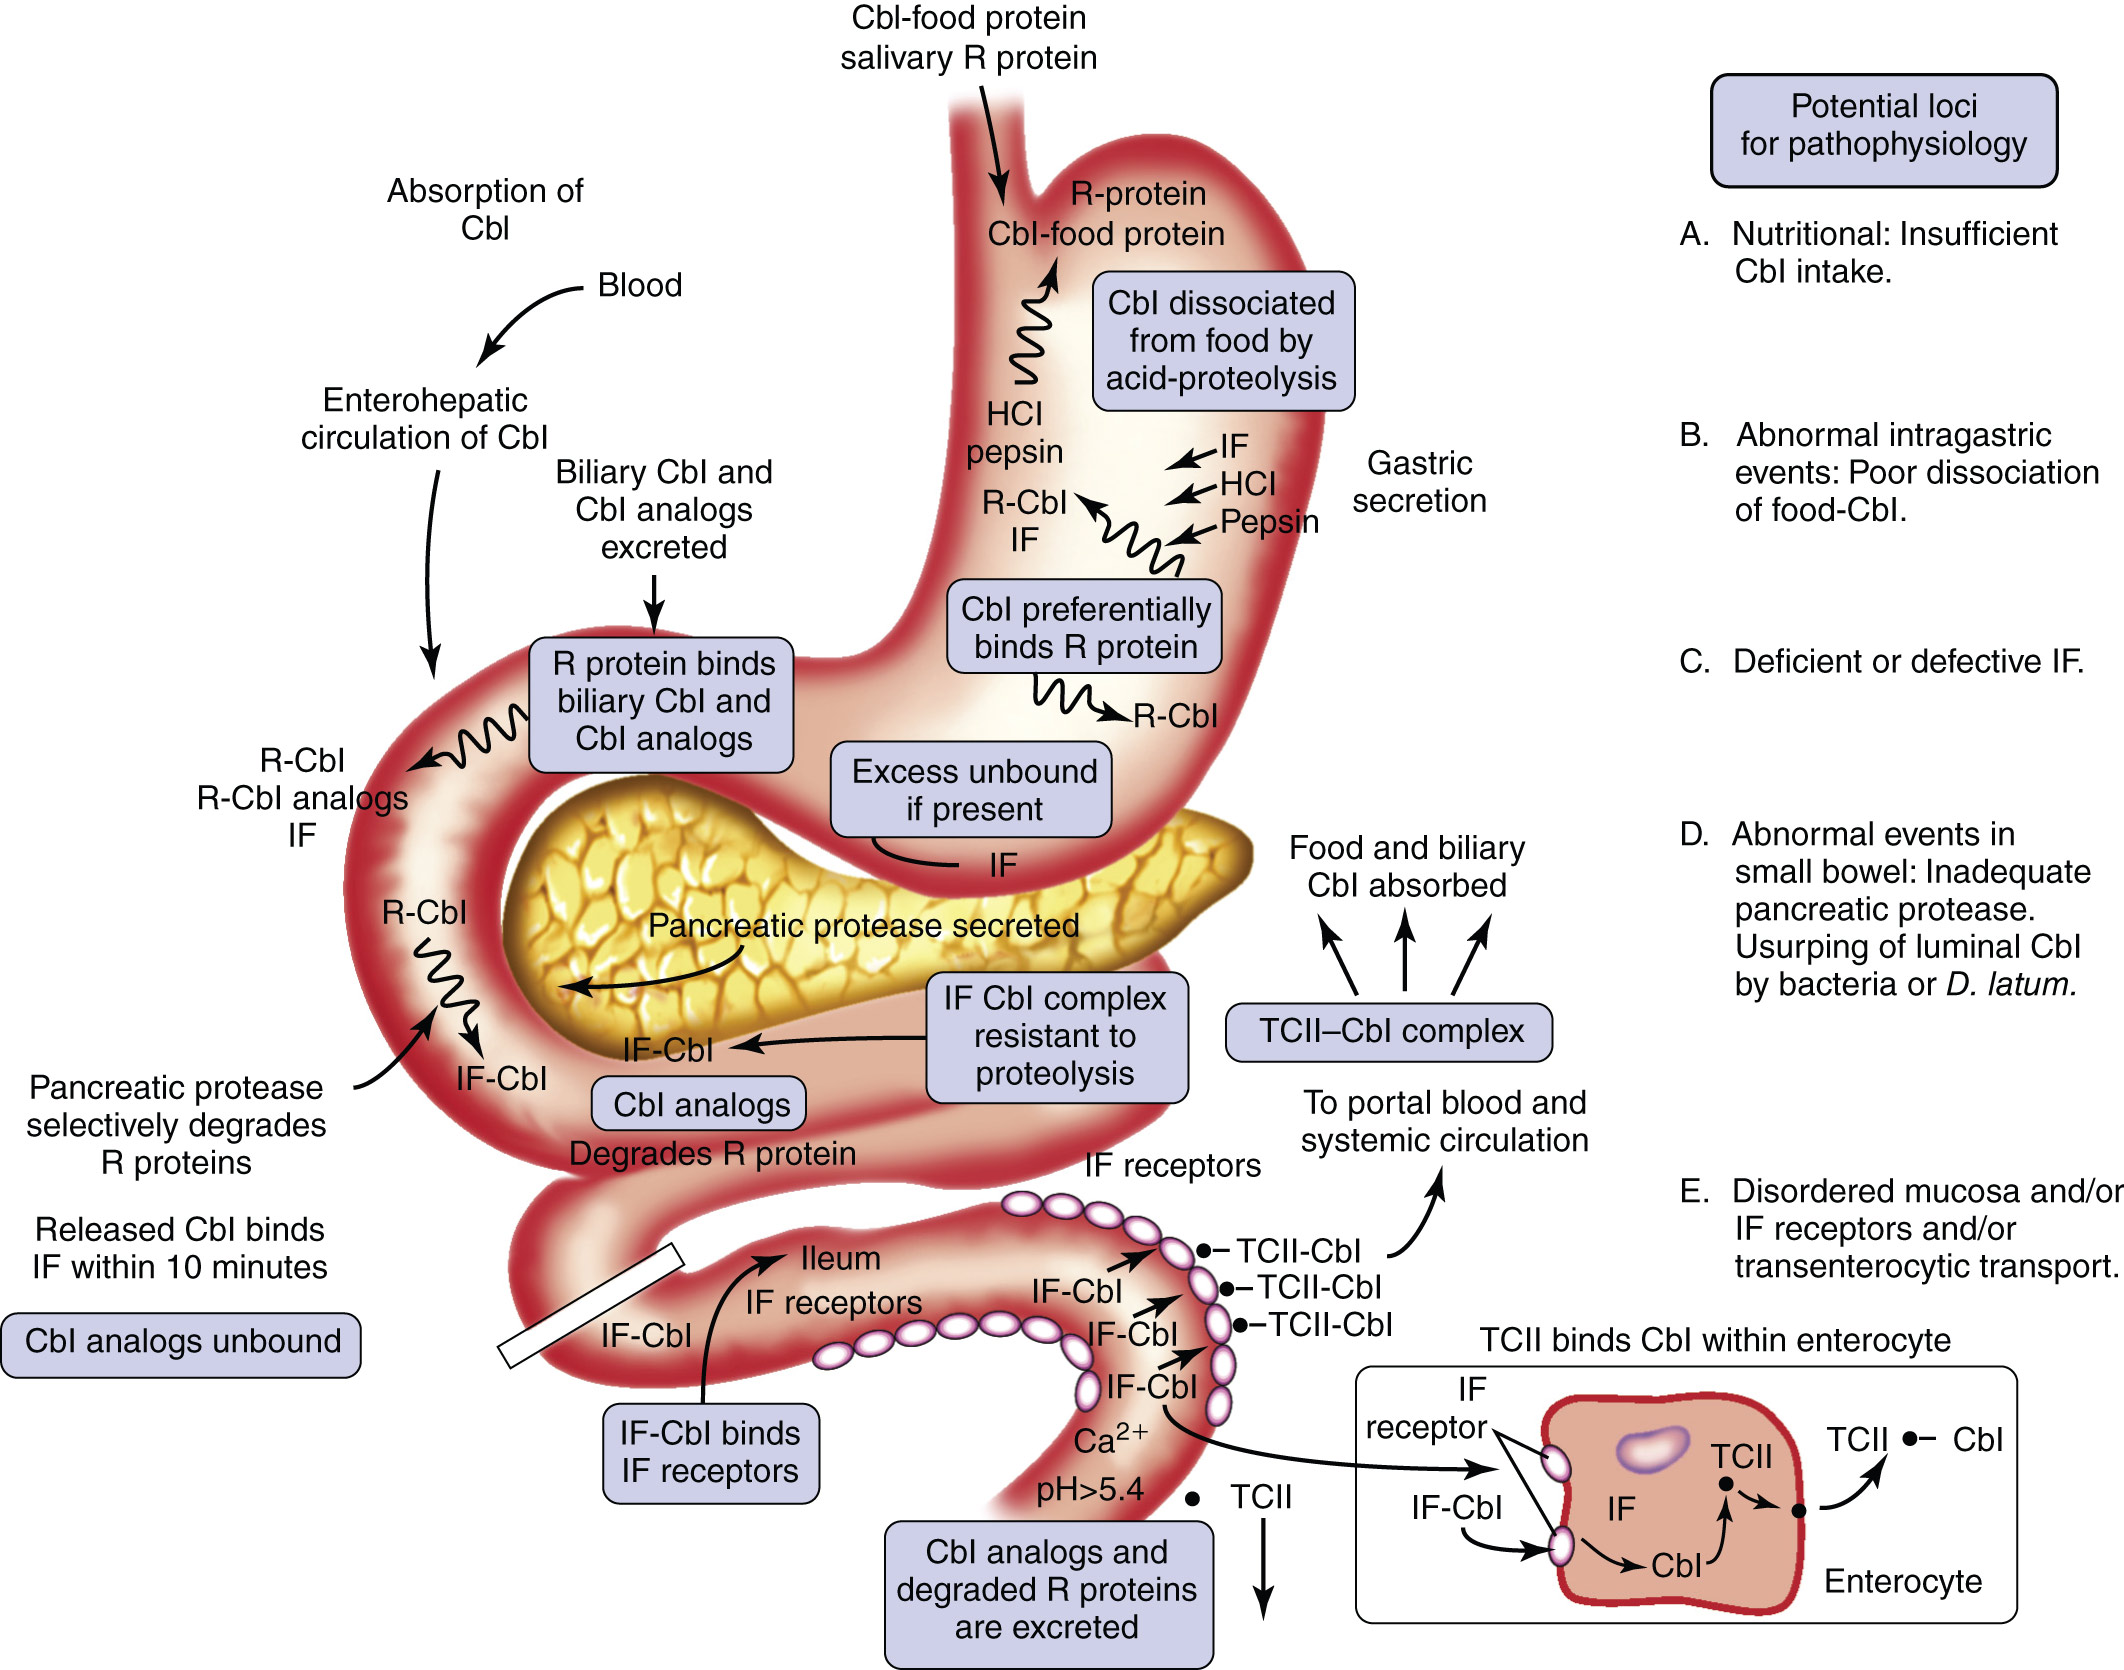
- •Inborn errors of cobalamin-cofactor synthesis are rare. Fig. E3 illustrates the components and mechanism of cobalamin absorption. An etiopathophysiologic classification of cobalamin deficiency is described in Section II.
Figure E2 Histologic Features of Stomach in Pernicious Anemia Compared with Normal
The Normal Gastric Mucosa (A) is Contrasted with that Seen in Pernicious Anemia (B), in Which There is Atrophy of Gastric Glands, Intestinal Metaplasia with Goblet Cells, and Loss of Parietal Cells (Not Visible at This Magnification).
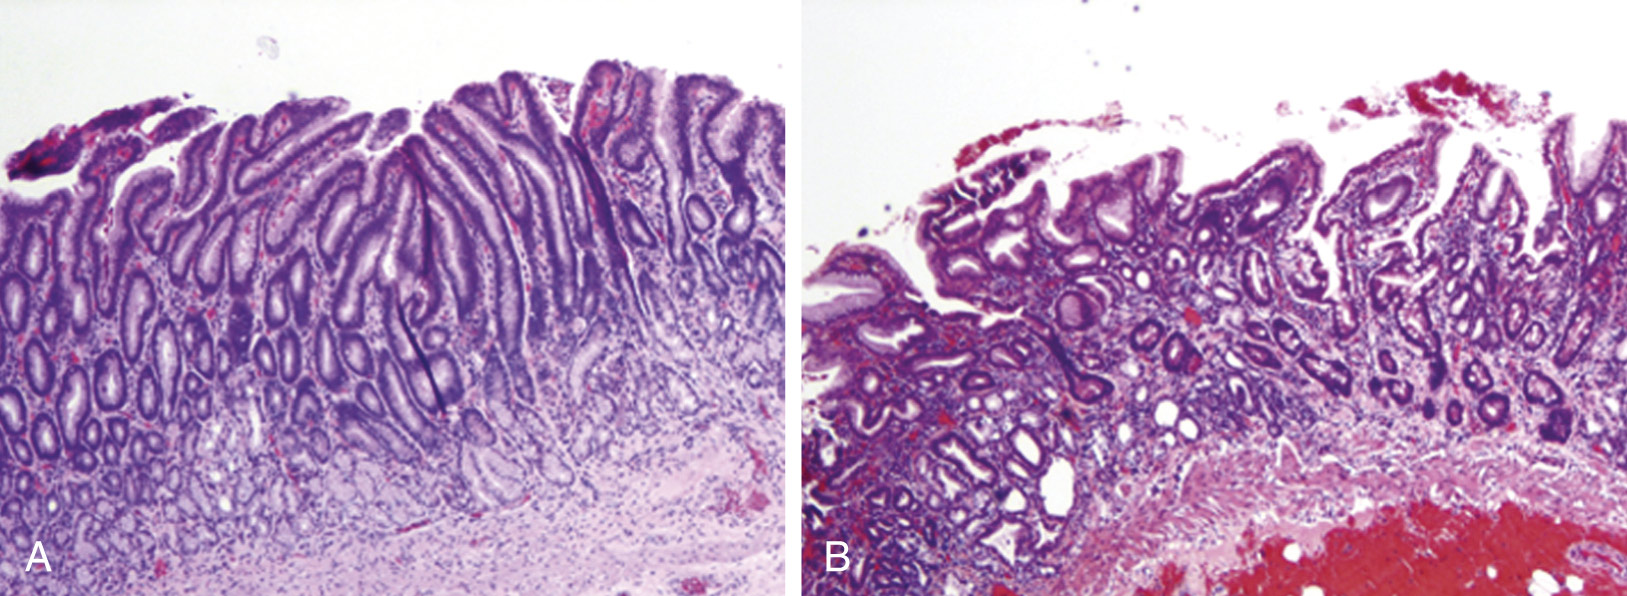
(From Hoffman R et al: Hematology, basic principles and practice, ed 8, Philadelphia, 2023, Elsevier.)