Drug: Imatinib Mesylate (Gleevec)
Indications: Imatinib mesylate is indicated for the treatment of patients with CML: 1. Initial treatment of newly diagnosed adult and pediatric patients with Ph+ chromosome CML in chronic phase
- Ph+ CML in blast crisis, in accelerated phase, or in chronic phase after failure of interferon-
 therapy
- Pediatric patients with Ph+ chronic phase CML whose disease has recurred after SCT or who are resistant to interferon- therapy
Imatinib is indicated for the treatment of:
- Adult patients with relapsed or refractory Ph+ acute lymphoblastic leukemia (ALL)
- Adult patients with myelodysplastic/myeloproliferative diseases (MDS/MPD) associated with PDGFR gene rearrangements
- Patients with Kit (CD117)-positive unresectable and/or metastatic malignant GISTs
- Adult patients following resection of Kit (CD117)-positive GIST (adjuvant)
- Adult patients with aggressive systemic mastocytosis (ASM) without the D816V c-Kit mutation or with unknown status
- Adult patients with hypereosinophilic syndrome (HES) and/or chronic eosinophilic leukemia with or without FIP1L1-PDGFR fusion kinase
- Adult patients with unresectable, recurrent, and/or metastatic dermatofibrosarcoma protuberans
Class: Protein tyrosine kinase inhibitor
Mechanism of Action: Inhibits abnormal tyrosine kinase encoded by the Philadelphia chromosome (BCR-Abl) in CML, thus preventing cell proliferation. Drug also inhibits receptor tyrosine kinases for PDGF. Inhibits c-Kit receptor called stem cell factor receptor tyrosine kinases as well, which has resulted in marked responses in GIST. Of patients with GISTs, 15–85% have Kit mutations that result in constitutively active kinases; imatinib mesylate selectively inhibits this mutated tyrosine kinase.
Pharmacokinetics: Well absorbed after oral administration, with 98% bioavailability and maximum concentration 2–4 hours after dosing. Elimination half-life of imatinib is 18 hours and 40 hours for primary active metabolite N-desmethyl derivative. Drug is 95% protein bound. It is metabolized via CYP3A4 hepatic cytochrome P450 enzyme system, with 81% of the dose eliminated in 7 days, primarily via fecal route (68%) and, to a lesser degree, urinary (13%). Of drug dose, 25% is excreted unchanged in feces and urine.
Dosage and Administration:
- 400 mg/day orally (single dose) for patients in chronic phase of CML
- 600 mg/day orally (single dose) for patients in accelerated phase or blast crisis
- Treatment continued as long as patient derives benefit from drug
- In case of disease progression at any time, failure to achieve a satisfactory hematologic response after 3 months of treatment, failure to achieve a cytogenetic response after 6–12 months of treatment, or loss of a hematologic or cytogenetic response: Increase dose to 600 mg/day (chronic CML); increase to 800 mg/day, given as 400 mg twice daily (accelerated or blast crisis) if no severe adverse drug reactions occur.
- Adults with Ph+ ALL: 600 mg/day
- GIST dosing: 400 mg/day orally. Metastatic or unresectable GIST: may dose escalate to 800 mg/day (400 mg PO twice daily) if disease progression occurs and drug is well tolerated. Adjuvant therapy following complete resection: some studies continued dosing for 1 year; optimal time is unknown.
- MDS, MPD: 400 mg/day PO Pediatric dosing (newly diagnosed): 340 mg/m2/day (not to exceed 600mg/day)
- Pediatric dosing (recurrence after SCT or if intolerant of interferon- therapy): 260 mg/m2/day
- Patients with mild to moderate hepatic impairment: 400 mg/day
- Patients with severe hepatic impairment: 25% dose reduction (e.g., 300 mg/day)
- Dose reduce for renal insufficiency: Moderate (creatinine clearance 20–39 mL/min) requires a 50% reduction in initial dose, which may be increased once it is established how the patient tolerates the drug, but doses > 400 mg/day are not recommended. Patients with creatinine clearance of 40–59 mL/min should not receive doses > 600 mg/day. Use drug cautiously (e.g., 100 mg/day if at all in patients with severe renal dysfunction). Dose reduce for severe neutropenia (ANC < 1.0 cells/mm3) and/or platelet
- count < 50,000/mm3 (see package insert).
Available as: 100-mg and 400-mg scored tablets in bottles of 120
Reconstitution and Preparation: None, as dose is oral. Administer dose orally, once daily (unless the total dose is 800 mg, which is given as 400 mg twice daily), with a meal and a large glass of water. Can dissolve tablet in water or apple juice if patient has dysphagia. If the dose is 800 mg and higher, 400-mg tablets should be used to reduce exposure to iron. Store at room temperature, 59–86°F (15–30°C), in a dry place, away from children and pets. Use gloves when handling the tablets, and return any unused drug in the bottle to the dispensing pharmacy for disposal.
Drug Interactions:
- CYP3A4 inhibitors (ketoconazole, itraconazole, erythromycin, clarithromycin, voriconazole, aprepitant) may increase imatinib plasma concentrations; do not coadminister, or monitor closely for imatinib adverse effects.
- CYP3A4 substrates (simvastatin): Imatinib decreases simvastatin metabolism with simvastatin serum levels increased 2–3.5 times. Use together cautiously, if at all, monitor BP, and dose reduce simvastatin if needed.
- CYP3A4 inducers (dexamethasone, phenytoin, carbamazepine, rifampicin, phenobarbital, St. John's wort) may increase metabolism of imatinib, so imatinib serum levels are reduced. Use together cautiously, if at all. When used with dexamethasone, phenytoin, carbamazepine, phenobarbital, rifabutin, or rifampin, increase imatinib dose by 50%. Do not take St. John's wort if taking imatinib.
- Other CYP3A4 substrates (cyclosporine, pimozide) increase plasma concentrations if coadministered with imatinib. Do not administer together because drug has a narrow therapeutic window.
- Other CYP3A4 substrates (triazolobenzadiazepines, dihydropyridine calcium channel blockers, HMG-CoA reductase inhibitors) may have increased serum levels when given together with imatinib. Use together cautiously, and monitor patient closely.
- Other CYP3A4 substrates: Eletriptan (Relpax) should not be administered within 72 hours of imatinib. Monitor vital signs closely.
- Warfarin: Do not give together with imatinib because imatinib inhibits warfarin metabolism by CYP2C9 enzymes. Use low molecular heparin or standard heparin instead.
- Acetaminophen: Systemic exposure of acetaminophen will be increased when coadministered with imatinib mesylate.
Contraindications: None
Warnings:
- Edema and severe fluid retention: Weigh patient regularly and manage unexpected, rapid weight gain with diuretics and dose interruption.
- Cytopenias with risk for infection, bleeding, and fatigue: Anemia, neutropenia, and thrombocytopenia have occurred. Manage with dose reduction or interruption, and rarely drug discontinuance. Monitor CBC weekly for first month, every other week for the second month, and periodically thereafter. Teach patient to self-assess and report temperature > 100.5°F, symptoms of infection or bleeding, or excessive fatigue. Teach patient to avoid contact with people who have colds and to wash hands frequently.
- Severe CHF and left ventricular dysfunction have been reported, especially in those with comorbidities, existing cardiac disease, or risk factors. Monitor patients closely and treat appropriately.
- Severe hepatotoxicity may occur. Assess LFTs baseline before starting the drug and monthly thereafter, or more frequently if clinically indicated. Monitor more closely when drug is combined with chemotherapy known to cause liver dysfunction. Dose modify depending upon laboratory findings, with a 25% dose reduction for patients with severe hepatic dysfunction.
- Grade 3 or 4 hemorrhage has been reported, especially in patients with newly diagnosed CML or GIST (GI lesions may be source).
- GI perforations have been reported.
- Cardiogenic shock or left ventricular dysfunction has been reported during drug initiation in patients with high eosinophil levels (HES, MDS/MPD, ASM). Monitor these patients very closely.
- Bullous dermatologic reactions such as erythema multiforme and Stevens-Johnson syndrome have been reported.
- Hypothyroidism in patients who have had a thyroidectomy and who are on levothyroxine replacement may occur. Monitor TSH levels closely in these patients.
- Drug is fetotoxic, so teach patients to use effective birth control measures and avoid pregnancy.
note:Adverse Reactions (bold indicates most common, occurring in > 25% of patients):
Cardiovascular:Edema with increased weight, periorbital edema, rare CHF, tachycardia, palpitations, angina
Pulmonary: Rare pleural effusions, ILD
CNS/neurologic:Headache, nasopharyngitis, dizziness, depression, blurred vision, nosebleeds, conjunctivitis, dry eye
Dermatologic:Rash, dry skin, alopecia, photosensitivity, rare hypersensitivity (e.g., bullous, erythema multiforme, Stevens-Johnson syndrome)
GI:Nausea, vomiting, diarrhea, abdominal pain, elevated LFTs, constipation, dyspepsia, anorexia, hypokalemia, stomatitis, rare increased serum amylase
Hematologic:Hemorrhage, neutropenia, thrombocytopenia, anemia
Musculoskeletal:Muscle cramps, arthralgias, myalgias, bone pain
General:Fatigue, pyrexia, night sweats
Nursing Discussion:
- Assess patient's laboratory parameters: CBC, platelets, LFTs (transaminases, bilirubin, alkaline phosphatase) baseline and then weekly × 4 CBC/differential, then every other week × 2, then monthly, along with monthly LFTs.
- Patients may develop resistance to the drug over time and require rescue with a second-generation agent.
- Review medication profile for interacting drugs, including OTC drugs such as aspirin and NSAIDs.
- Teach patient to use gloves when handling the tablet and to wash hands before and after wearing gloves. If pills remain in the bottle, return them to dispensing clinic or pharmacy for disposal.
Drug: Dasatinib (Sprycel)
Indications: Dasatinib is indicated for the treatment of adults with:
- Chronic, accelerated, or myeloid or lymphoid blast phase CML with resistance or intolerance to prior therapy including imatinib
- Ph+ ALL with resistance or intolerance to prior therapy
Class: Multitargeted kinase inhibitor
Mechanism of Action: Drug inhibits the following kinases: BCR-Abl, SRCfamily (SRC, LCK, YES, FYN), c-KIT, EPHA2, and PDGFR- . Drug forms a tighter bond with BCR-Abl kinase (300–1000 times more potently) than imatinib mesylate (Gleevec) and binds to both active and inactive forms (multiple forms of the ABL kinase).
Pharmacokinetics: Drug is rapidly absorbed after oral ingestion with peak serum levels in 0.5–6 hours and an overall mean half-life of 3–5 hours. If ingested with a high-fat meal, there is a 14% increase in the mean AUC exposure, but this is not considered clinically relevant. Drug and its active metabolite bind to plasma proteins 96% and 93%, respectively. Drug is extensively metabolized by the P450 microenzyme CYP3A4. Drug is excreted in the feces (85%) and to a lesser degree the urine (4%).
Dosage and Administration:
- Chronic-phase CML: 100 mg PO once daily
- Accelerated-phase CML, myeloid- or lymphoid blast-phase CML, or Ph+ ALL: 140 mg PO once daily
- Dose may be increased or decreased in 20-mg increments based on individual patient response or coadministration with drugs that either increase or decrease dasatinib serum levels (see drug interactions).
- Dose modifications for neutropenia: Monitor CBC weekly for the initial 2 months and then periodically. Chronic phase CML (starting dose 100 mg once daily): ANC < 0.5 × 10⁹/L or platelets < 50 × 109/L: (1) Stop drug until ANC is
 1 × 10⁹/L or platelets 50 × 109/L; (2) resume treatment at initial starting dose if recovery occurs on or within 7 days; (3) if platelets < 25 × 109/L or recurrence of ANC < 0.5 × 10⁹/L for > 7 days, stop drug as above, and resume drug at a reduced dose of 80 mg once daily (second episode) or discontinue drug (third episode).
- Accelerated phase CML, Blast phase CML, and Ph+ALL (starting dose 140 mg once daily): ANC < 0.5 × 10⁹/L or platelets < 10 × 109/L: (1) Check to see if cytopenia is related to leukemia by assessing bone marrow aspirate or biopsy; (2) if cytopenia unrelated to leukemia, stop drug until ANC is 1.0 × 10⁹/L or platelets 20 × 109/L and resume treatment at initial starting dose; (3) if recurrence of cytopenia, repeat step 1 and resume drug at reduced dose of 100 mg once daily (second episode) or 80 mg once daily (third episode); (4) if cytopenia is related to leukemia, consider dose escalation to 180 mg once daily.
- In clinical studies, adult patients with CML or Ph+ ALL who did not achieve a hematologic or cytogenic response at the recommended dosage were allowed to dose escalate to 140 mg once daily, or 180 mg once daily, respectively.
Available as: 20-mg, 50-mg, 70-mg, and 100-mg tablets, each in 60-tablet bottles, except the 100-mg tablets, which come in a 30-tablet bottle
Reconstitution, Preparation, Administration: Drug Administration: Oral, once in the morning and once in the evening, with or without food; do not crush or cut. Store at room temperature, 59–86°F (15–30°C), in a dry place, away from children and pets. Use gloves when handling the tablets, and return any unused drug in the bottle to the dispensing pharmacy for disposal.
Drug Interactions:
- CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, erythromycin, clarithromycin, atazanavir, indinavir, nefazodone, nelfinavir, ritonavir, saquinavir, telithromycin): May decrease metabolism of dasatinib, thus increasing serum concentrations of dasatinib; avoid coadministration, and if they must be given together, decrease dose of dasatinib. Decrease dose by 20 mg in patients taking 100 mg daily, and decrease 40 mg in patients taking 140 mg daily. If reduced drug dosage is not tolerated, either the strong CYP3A4 inhibitor must be discontinued or dasatinib. After the strong inhibitor is discontinued, allow a washout period of approximately 1 week before dasatinib dose is increased.
- CYP3A4 inducers: Rifampin—decreases dasatinib serum concentrations by 81%; others (dexamethasone, phenytoin, carbamazepine, phenobarbital, St. John's wort)—avoid coadministration, and if they must be given together, increase dose of dasatinib. Patients receiving dasatinib should NOT take St. John's wort.
- Antacids (aluminum hydroxide/magnesium hydroxide): Decreases dasatinib AUC by 55%, as drug requires acid pH; avoid concurrent administration or administer 2 hours prior to or 2 hours after dasatinib dose.
- H2 blockers/proton pump inhibitors (PPIs): Famotidine decreases dasatinib AUC 61%; avoid concurrent administration. Consider use of antacids rather than H2 blockers or PPIs.
- Simvastatin, CYP3A4 substrates: Dasatinib is a time-dependent inhibitor of CYP3A4 and may decrease the metabolism of drugs primarily metabolized by CYP3A4, such as alfentanil, astemizole, terfenadine, cisapride, cyclosporine, fentanyl, pimozide, quinidine, sirolimus, tacrolimus, or ergot alkaloids; decreases simvastatin AUC 37%; avoid concurrent administration or administer cautiously.
Contraindications: None
Warnings:
- Myelosuppression: Severe thrombocytopenia, neutropenia, and anemia may occur, requiring dose interruption or dose reduction. Cytopenias are more common in patients with advanced-phase CML or Ph+ ALL than in chronic-phase CML. Monitor CBC, differential baseline, then weekly for the first 2 months, and monthly thereafter. Teach patients to self-assess for signs/symptoms of infection, bleeding, and excessive fatigue. Teach patients to report temperature > 100.5°F, bleeding, or excessive fatigue.
- Bleeding-related events: Most are associated with severe thrombocytopenia. Rarely severe bleeding, such as CNS hemorrhage (1%), GI bleeding/hemorrhage (4%), have occurred and have required treatment interruption and transfusions. Use drug cautiously in patients who are also receiving medications that inhibit platelet function or anticoagulants.
- Fluid retention: Fluid retention occurs commonly and may occasionally be severe; fluid retention (10%, e.g., edema, ascites) and pleural (7%) and pericardial (1%) effusions may occur. Severe pulmonary edema occurrs in 1% of patients. Assess patients closely and manage with appropriate medical care (e.g., assess patients for dyspnea and dry cough; signs/symptoms suggestive of pleural effusion should prompt a chest x-ray). Supportive care is usually effective and includes diuretics, short course of steroids, and rarely thoracentesis and oxygen therapy.
- QT prolongaation: Use drug cautiously in patients who have or are at risk for developing QT prolongation, such as those taking certain antiarrythmic drugs or those who have an electrolyte imbalance (e.g., hypokalemia, hypomagnesemia), congenital QT prolongation, or high cumulative antracycline doses. Assess baseline ECG with QTc measurement, and repeat periodically during treatment.
- Drug is fetotoxic: Teach patients to use effective contraception.
- Although no drug modification is recommended, use cautiously in patients with hepatic impairment.
note:Adverse Reactions (bold indicates most common, occurring in > 25% of patients):
Cardiovascular:Fluid retention, hypertension, arrhythmia
Pulmonary:Dyspnea, pleural effusion, pericardial effusion, CHF, cardiac dysfunction, pulmonary edema
CNS/neurologic:Headache, insomnia, depression, visual disturbance
Dermatologic:Skin rash, urticaria
Metabolic: Hypophosphatemia, hypokalemia, hypocalcemia, elevated LFTs
GI:Diarrhea, nausea, abdominal pain, vomiting, mucosal inflammation, anorexia
Hematologic:Myelosuppression, hemorrhage, febrile neutropenia
Musculoskeletal: Myalgias, arthralgias
General:Fatigue, fever
Nursing Discussion:
- Assess patient's laboratory parameters: CBC, platelets, LFTs (transaminases, bilirubin, alkaline phosphatase) baseline and then CBC/differential weekly × 8, then monthly. Assess baseline ECG for QTc interval and document in the chart. Assess if patient has risk factors (e.g., electrolyte imbalance), correct, if possible, and discuss with physician or midlevel practitioner.
- Patients may develop resistance to the drug over time and require rescue with a second-generation agent.
- Review medication profile for interacting drugs, including OTC drugs such as aspirin and NSAIDs.
- Teach patient to use gloves when handling the tablet and to wash hands before and after wearing gloves. If pills remain in the bottle, return them to dispensing clinic or pharmacy for disposal.
Drug: Nilotinib (Tasigna)
Indications: Nilotinib is FDA indicated for the treatment of chronic-phase and accelerated-phase Ph+ CML in adult patients resistant to or intolerant to prior therapy that included imatinib.
Class: Protein kinase inhibitor (specific for)
Mechanism of Action: Ph+ CML and ALL are caused by a reciprocal mutation involving two chromosomes in the bone marrow stem cells that causes genetic material to be exchanged between chromosomes 9 and 22, creating the Philadelphia chromosome. The result is a fusion gene formed when the breakpoint cluster region (BCR) from chromosome 22 is placed next to the Abl gene on chromosome 9, forming the BCR-Abl gene. The normal ABL gene is a protooncogene and makes a protein kinase messenger that is normally tightly controlled. In the fusion gene, which looks like a short and fat bowling ball, the protein kinase behaves like an oncogene and continues to send the message to the cell nucleus to divide, resulting in the formation of primitive leukemic cells. In fact, the BCR-Abl fusion gene causes cell proliferation, decreased adhesion/increased migration, inhibition of apoptosis, degradation of regulatory proteins, and prevention of DNA repair. When the protein kinase is activated, it continues to send the message to the cell nucleus telling the cell to divide. However, the binding site is sometimes blocked (inactive) and sometimes active and able to bind to ATP, which turns it on. In addition, it can mutate, and a drug that was once able to block the ATP binding site may no longer fit into the ATP pocket. When a patient progresses on imatinib, it is because BCR-Abl is reactivated through a number of processes, such as amplification of BCR-Abl gene expression, or more than 30 point mutations in the BCR-Abl kinase domain that disable the drug from binding to the ATP binding site on the protein kinase. Nilotinib is a designer drug that is highly specific for and binds very tightly to the ATP binding site of ABL (more selective and 30 times more potent an inhibitor than imatinib mesylate). The drug is active against 32 of the 33 most common BCR-Abl mutations causing imatinib resistance. The drug also inhibits the KIT and PDGFR-A proteins found in patients with GIST.
Pharmacokinetics: The drug is metabolized via the cytochrome P450 microenzyme system in the liver (CYP3A4). A high-fat diet greatly increases drug bioavailability (82%), and thus, the drug must be given on an empty stomach.
Peak concentrations are reached 3 hours after drug administration. Serum protein binding is 98%. Elimination half-life with daily dosing is 17 hours, and steady state is reached by day 8. Metabolism occurs by oxidation and hydroxylation. Metabolites are not pharmacologically active. More than 90% of administered dose is eliminated within 7 days, primarily via the feces. Age, weight, gender, and ethnicity do not significantly affect pharmacokinetics.
Dosage and Administration: Oral.
- Nilotinib 400 mg orally twice daily, approximately 12 hours apart on an empty stomach (no food 2 hours before or 1 hour after the dose). Drink only water in the hour after the dose.
- Dose reduce for corrected QT (QTc) interval prolongation > 480 milliseconds. Stop the drug, assess serum potassium and magnesium, and replete if needed. Resume dose within 2 weeks if the QTc returns to < 450 milliseconds and to within 20 seconds of baseline. If the QTc is 450–480 milliseconds after 2 weeks, reduce the dose to 400 mg once daily. If following the dose reduction, the QTc returns to > 480 milliseconds, discontinue nilotinib. An ECG should be repeated approximately 7 days after any dose adjustment. Dose reduce for hematologic (ANC < 1.0 × 10⁹/L and/or platelet count < 50 × 109/L). Stop nilotinib, and monitor blood counts. Resume within 2 weeks at prior dose if ANC > 1.0 × 10⁹/L and platelets are > 50 × 109/L. If blood counts remain low for > 2 weeks, reduce dose to 400 mg once daily.
- Grade 3 or higher nonhematologic toxicities (serum lipase or amylase, elevated bilirubin, elevated hepatic transaminases): Hold nilotinib and monitor serum values; resume nilotinib at 400 mg once daily if serum levels return to
 grade 1.
- If patient requires a dose reduction, if appropriate, may gradually escalate base to 400 mg twice daily once condition has stabilized.
- Nilotinib can be given with hematopoietic growth factors such as erythropoietin or G-CSF if indicated.
- Nilotinib can be given with hydroxyurea or anagrelide if clinically indicated.
Available as: 200-mg hard gelatin capsules
Reconstitution and Preparation: Oral. Store at room temperature, 59–86°F (15–30°C), in a dry place, away from children and pets. Use gloves when handling the tablets, and return any unused drug in the bottle to the dispensing pharmacy for disposal.
Drug Interactions:
- CYP3A4 (strong) inhibitors (ketoconazole, itraconazole, clarithromycin, atazanavir, indinavir, nefazodone, nelfinavir, ritonavir, saquinavir, telithromycin, voriconazole, grapefruit juice) may increase imatinib plasma concentrations; do not coadminister. IF their administration is necessary, interrupt nilotinib therapy; if continued coadministration is necessary, adjust nilotinib dose to 400 mg daily (decrease by 50%), and monitor QTc interval closely for any prolongation. If the strong inhibitor is discontinued, a washout period should be allowed before increasing the dose of nilotinib back to 400 mg every 12 hours. Teach patient to avoid grapefruit and grapefruit juice.
- CYP3A4 substrates (simvastatin): Nilotinib decreases simvastatin metabolism with simvastatin serum levels increased 2–3.5 times. Use together cautiously, if at all, and monitor BP and dose reduce simvastatin if needed.
- CYP3A4 (strong) inducers (dexamethasone, phenytoin, carbamazepine, rifampicin, phenobarbital, St. John's wort) may increase metabolism of nilotinib so that nilotinib serum levels are reduced. Use together cautiously, if at all. When used with dexamethasone, phenytoin, carbamazepine, phenobarbital, rifabutin, or rifampin, increase nilotinib dose by 50%. If later the strong inducer is discontinued, the nilotinib dose should be decreased to the original dose. Teach patient to not take St. John's wort if taking nilotinib.
- Other CYP3A4 substrates (cyclosporine, pimozide) increase plasma concentrations if coadministered with nilotinib. Do not administer together because drug has a narrow therapeutic window.
- Other CYP3A4 substrates (triazolobenzodiazepines, dihydropyridine calcium channel blockers, HMG-CoA reductase inhibitors) may have increased serum levels when given together with nilotinib. Use together cautiously, and monitor patient closely.
- Other CYP3A4 substrates: Eletriptan (Relpax) should not be administered within 72 hours of nilotinib. Monitor vital signs closely.
- Warfarin: Nilotinib is a competitive substrate; thus, INR must be monitored closely and warfarin dose adjusted frequently.
- Drugs prolonging QTc (e.g., serotonin antagonists, other tyrosine kinase inhibitors): Do not use together, as will increase risk of prolonged QTc and sudden death.
- Nilotinib is an inhibitor of CYP3A4, CYP2C8, CYP2C9, and CYP2D6. It may be an inducer for CYP2B6, CYP2C8, and CYP2C9, thus affecting the serum levels of other drugs. See Chapter 5.
Contraindications:
- Patients with hypokalemia, hypomagnesemia, or long QT syndrome
- Drug is fetotoxic. Women of childbearing potential should use effective contraception and avoid pregnancy.
- Nilotinib should not be used by women who are breastfeeding.
Warnings:
- Myelosuppression: Associated with neutropenia, thrombocytopenia, and anemia. CBC should be assessed every 2 weeks for the first 2 months, then monthly. Reversible by withholding dose, and dose reduction per manufacturer. Dose reduction may be required.
- QT prolongation: nilotinib prolongs the QT interval. Correct hypokalemia or hypomagnesemia prior to administration and monitor periodically. Avoid drugs known to prolong the QT interval and strong CYP3A4 inhibitors. Use caution in patients with hepatic impairment. Hypokalemia and hypomagnesemia can increase the QTc interval. When taking nilotinib, which also prolongs the QTc interval, the patient may develop torsades de pointes, a ventricular tachycardia that can result in sudden death. This can be prevented by ensuring that serum magnesium and potassium are WNL and by closely monitoring QTc by ECG.
- Obtain ECGs at baseline, 7 days after initiation, and periodically thereafter, as well as following any dose adjustments.
- Sudden deaths: There were sudden deaths reported in the safety population and the expanded access program. Ventricular repolarization abnormalities may have contributed to their occurrence.
- Nilotinib can cause elevated serum lipase: Use cautiously if at all in patients with a history of pancreatitis. Assess serum lipase and amylase regularly during treatment.
- Liver function abnormality may occur, with elevations in bilirubin, AST/ALT, and alkaline phosphatase. Monitor LFTs baseline and periodically during treatment.
- Nilotinib can cause electrolyte abnormalities, including hypophosphatemia, hypokalemia, hyperkalemia, hypocalcemia, and hyponatremia. Correct electrolyte abnormalities prior to initiating nilotinib and monitor periodically during therapy.
- Hepatic impairment: Nilotinib has not been studied in patients with hepatic dysfunction. Use nilotinib cautiously in this patient group, and monitor QTc interval on ECG closely.
- Drug interactions: Avoid concomitant use of strong inhibitors or inducers of CYP3A4. If patients must be coadministered a strong CYP3A4 inhibitor, dose reduction should be considered, and the QT interval should be monitored closely.
- Food effects: Food increases blood levels of nilotinib. Avoid food 2 hours before and 1 hour after a dose.
note:Adverse Reactions (bold indicates most common, occurring in > 25% of patients):
Cardiovascular:QTc interval prolongation on ECG, peripheral edema, palpitations, hypertension, flushing
Pulmonary: Pneumonia, cough dyspnea, nasopharyngitis
CNS/neurologic:Headache, intracranial hemorrhage, dizziness, paresthesia, vertigo
Dermatologic:Rash,pruritus, night sweats, eczema, urticaria, alopecia, erythema
Metabolic: Elevated lipase, amylase, hypokalemia, hyponatremia, hyperglycemia, hypophosphatemia, hyperkalemia, decreased albumin, hypocalcemia, hyperthyroidism
GI:Nausea, diarrhea, constipation, vomiting, decreased serum albumin, elevated LFTs (ALT, total bilirubin, AST, alkaline phosphatase), abdominal pain, dehydration, anorexia, dyspepsia, flatulence
Hematologic:Neutropenia, thrombocytopenia, anemia, febrile neutropenia, leucopenia
Musculoskeletal: Arthralgia, myalgias, pain in extremity, bone pain, muscle spasms, back pain
Genitourinary: Elevated serum creatinine
General:Fatigue, pyrexia, asthenia
Nursing Discussion:
QTc interval prolongation: Nilotinib can increase the QTc interval (the period of ventricular repolarization in the heart) on the ECG. Prolongation of the QTc can increase the risk of developing torsades de pointes (twisting about the points), an unusual variant of ventricular tachycardia that may result in sudden death, syncope, or seizures (Figure 2-9). Risk of developing this condition is also increased if the patient has hypomagnesemia and hypokalemia. Thus, the nurse should ensure that the patient's electrolytes are WNL and that any abnormalities are corrected before the patient begins nilotinib. In addition, a baseline ECG should be done and repeated 7 days after nilotinib initiation, and then periodically during therapy. Electrolytes should also be monitored closely and repleted as needed. Concomitant use of drugs that are strong inhibitors of the CYP3A4 will block metabolism of nilotinib, resulting in increased toxicity, including QTc prolongation. The nurse should carefully review the patient's medication profile along with the physician, midlevel practitioner, or pharmacist to ensure that there are no drug interactions.
Patient teaching takes on increased importance, as the patients must be able to take nilotinib safely—that is, 2 hours before or 1 hour after a meal. Only water should be taken in during the 1 hour after the dose. If patients take nilotinib with food, the bioavailability of the drug is greater, the serum drug levels higher, and the risk of toxicity higher.
Review medication profile for interacting drugs, including OTC drugs such as aspirin and NSAIDs. Teach patient to use gloves when handling the tablet and to wash hands before and after wearing the gloves. If pills remain in the bottle, return them to dispensing clinic or pharmacy for disposal.
Figure 2-9. Torsades de pointes
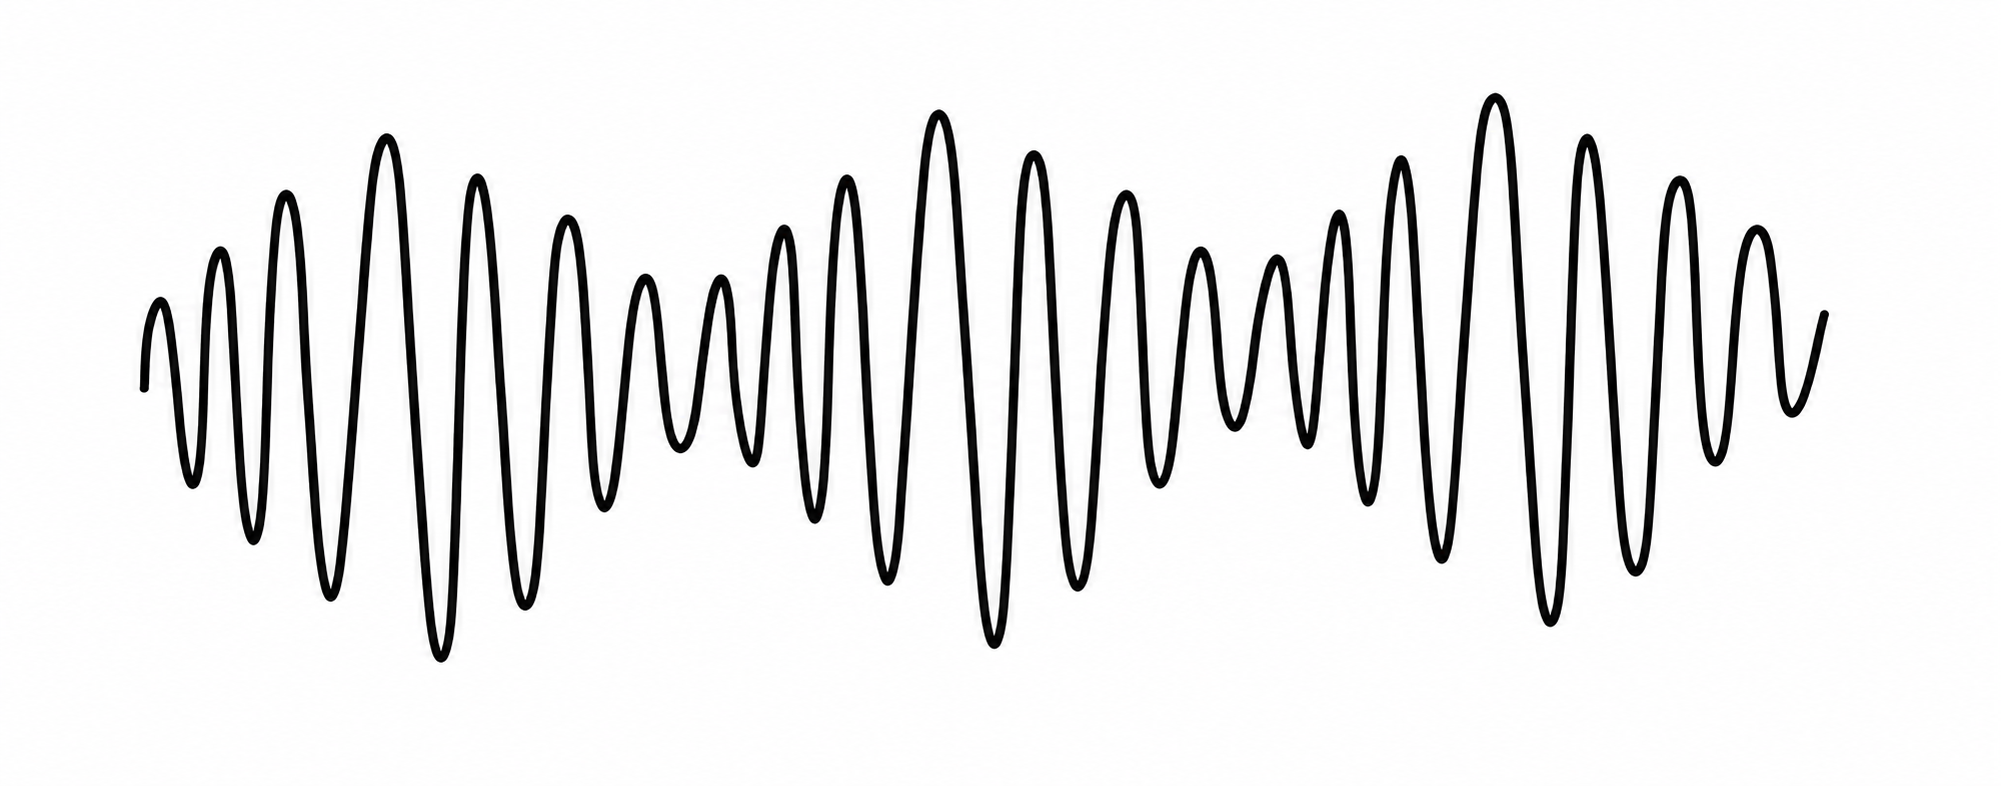
From 12-Lead ECG: The Art of Interpretation, courtesy of Tomas B. Garcia, MD.
Lab monitoring: CBC/differential baseline, then every 2 weeks for the first 2 months, and then monthly; ECG to monitor QTc baseline, 7 days after first dose, then periodically as well as after any dose adjustments; monitor QTc closely in patients with liver impairment or receiving strong CYP3A4 inhibitors; monitor electrolytes baseline and correct prior to starting drug, especially magnesium and potassium; monitor magnesium, potassium, calcium, phosphorus, sodium; monitor serum lipase and glucose baseline in patients with a history of pancreatitis; monitor LFTs baseline and periodically.
Risk for neutropenia and thrombocytopenia: Grade 3 or 4 neutropenia occurred in 28% of patients in chronic-phase and 37% of patients with acceleratedphase; thrombocytopenia in 28–37% of patients; anemia in 8–23% of patients. Febrile neutropenia occurred in < 10% of patients with accelerated-phase CML. Assess baseline CBC, WBCs, differential, and platelet count baseline before initiating therapy, then every 2 weeks for the first 8 weeks, and then monthly. Assess for signs/symptoms of infection or bleeding. Teach patient the signs/symptoms of infection or bleeding and to report them immediately, and teach patient self-care measures to minimize risk of infection and bleeding. Measures include avoidance of crowds, proximity to people with infections, and OTC aspirin-containing medications. Discuss need for blood product support or growth factors with physician or nurse practitioner.
Potential alteration in nutrition related to GI symptoms: Nausea affects 31% of patients (1% grade 3 or 4), and vomiting affects 21% (< 1% grade 3 or 4). Diarrhea affects 22% (3% grade 3 or 4), whereas constipation affects 20%. Hepatotoxicity is characterized by transient and reversible increase in LFTs. Grade 3 or 4 lipase increased in 15–17% of patients and glucose in 11%. The largest increase in bilirubin was found in patients with (TA) 7 genotype (UGT1A1*28).
** The enzyme UGT1A1*28 has a gene copy in some people (polymorphism) that has extra Thymidine-adenine (TA) repeats in the promoter region (7). This results in the liver's decreased ability to break down certain drugs, such as irinotecan, and causes an elevated level of unconjugated bilirubin in the blood. It is also found in people with Gilbert's syndrome and results in jaundice.
Teach patient to self-administer antiemetic 1 hour before each dose if needed and to call if nausea/vomiting develop. Discuss with physician more effective antiemetic regimen if nausea/vomiting develop despite antiemetics. Encourage small, frequent intake of cool, bland foods as tolerated if nausea develops. Refer to dietitian as needed for meal planning. Assess bowel elimination pattern baseline and at each visit. Teach patient to report diarrhea or constipation that does not respond to antidiarrheal or anticonstipation medications. Teach dietary modifications as appropriate. Monitor LFTs, serum, lipase, and glucose baseline and periodically during therapy. Discuss abnormalities with physician. Teach patient to report any abdominal pain with nausea or vomiting.