▶Aplasia cutis congenita (ACC) is a congenital defect of the skin that results in localized absence of the epidermis; dermis; and, occasionally, subcutaneous tissue.
▶The cause is unknown, and most cases are sporadic, although autosomal dominant inheritance has been suggested in some reports. A link with maternal antithyroid medication (especially methimazole) use during pregnancy has been suggested.
▶ACC is a feature of Adams-Oliver (with transverse limb defects and vascular and cardiac irregularities) and oculocerebrocutaneous (Delleman) syndromes and may occur in those who have trisomy 13 syndrome.
▶Usually presents as a solitary, round, oval, or stellate, 1- to 2-cm ulcer (Figure 99.1) or scar (Figure 99.2) located on the scalp near the origin of the hair whorl (although other body sites occasionally are affected). A minority of patients have multiple lesions (typically 2 or 3).
▶In some patients, the defect is covered by a thin membrane and surrounded by long dark hairs (the hair collar sign [Figure 99.3]). This membranous form of ACC is postulated to be a mild form of cranial neural tube closure defect.
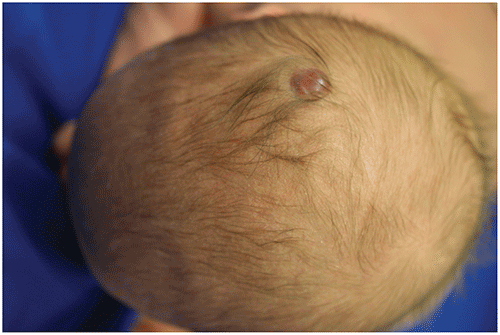
▶Occasionally may present as bullous ACC, with the appearance of a blister overlying the ACC, and often an associated hair collar sign (Figure 99.4); this form may be a forme fruste of a neural tube defect, and histologic evaluation may reveal changes of cephalocele or meningocele.
▶Large lesions (>4 cm) may be associated with underlying skull defects that may predispose to sagittal sinus hemorrhage or thrombosis, local infection, or meningitis.
Figure 99.1. Stellate Ulcer with Overlying Crust Characteristic of Aplasia Cutis Congenita.
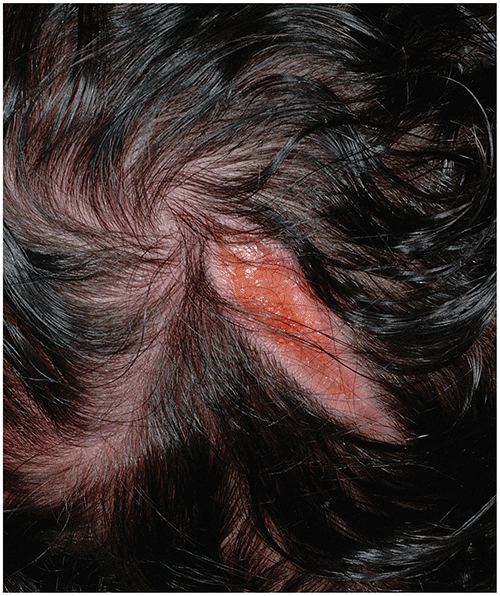
Figure 99.2. Aplasia Cutis Congenita Presenting as an Atrophic Scar.
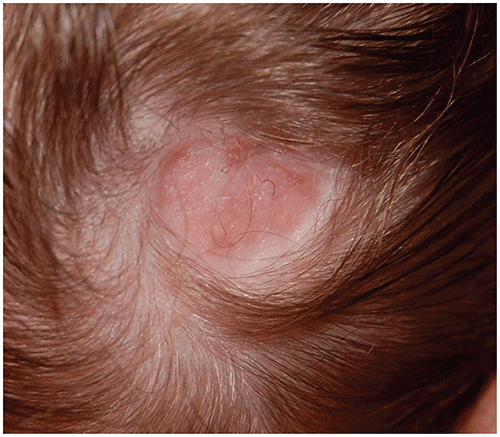
Figure 99.3. Aplasia Cutis Congenita in Which a Thin Membrane is Surrounded by Long Dark Hairs (Ie, the Hair Collar Sign).
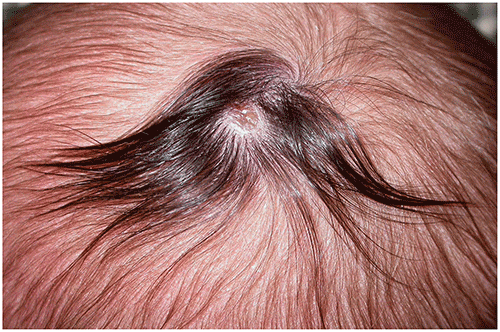
Figure 99.4. Bullous Aplasia Cutis Congenita with a Hair Collar Sign; Surgical Excision Was Performed (after Imaging Ruled Out Bony Defect or Tract to the Central Nervous System), and Histologically This Lesion Was a Cephalocele.
Look-alikes
| Disorder | Differentiating Features |
|---|
| When Presenting as an Ulcer |
|---|
| Herpes simplex virus infection | |
| Trauma from forceps | |
| Trauma from scalp electrode | |
| Epidermolysis bullosa | Typically more superficial than ACC, with denudation and eroded patches. Usually presents with multiple sites of involvement. Oral mucosal involvement occasionally present.
|
| When Presenting as a Scar |
|---|
| Nevus sebaceus | Usually presents as a verrucous (warty) plaque; however, some lesions are quite flat in neonates and may mimic a scar. Often yellowish orange to tan. If left untreated, becomes more elevated and verrucous in the peri-pubertal and postpubertal years.
|
▶For small ulcers, local wound care to prevent secondary bacterial infection is sufficient. Lesions presenting as scars require no treatment.
▶Large lesions require plastic surgery consultation and imaging.
▶Excellent for small lesions; atrophic scars will persist, and ulcers will heal with atrophic scars.
▶Large lesions may be associated with underlying skull defects that may predispose to sagittal sinus hemorrhage or thrombosis, local infection, or meningitis. For such patients, plastic surgical consultation is recommended.
▶Obtain plastic surgery consultation and consider imaging (for underlying central nervous system involvement) for patients with large lesions or deeper involvement. Also consider imaging for lesions accompanied by vascular stains or nodules or those with an associated hair collar sign (because of the risk of associated neural tube defect).