section name header

Basic Information ⬇

Author: Katerina L. Byanova, MD, MS and Laurence. Huang, MD, FCCP, ATSF

Definition

Pneumocystis jirovecii pneumonia (PJP) or Pneumocystis pneumonia (PCP) is a respiratory infection caused by the fungal pathogen P. jirovecii (formerly known as P. carinii).

Synonyms

  • Pneumocystis jirovecii pneumonia
  • PJP
  • Pneumocystis pneumonia
  • PCP
ICD-10CM CODE
B59Pneumocystosis
Epidemiology & Demographics
Incidence (In U.S.):

  • •In the early days of the HIV epidemic most PCP cases occurred in people with HIV (PWH) with CD4 counts <200/mm3. Given improvements in HIV treatment, >70% of cases are now found in persons without HIV.1 Pneumocystis disease is often more fulminant in people without HIV, leading to a higher mortality (33% to 71% compared with 13% to 18% among PWH).2
  • •Risk factors for infection in people with HIV include CD4 cell count <200/mm3 or CD4% <14%, elevated HIV RNA levels, and history of PCP.
  • •Among PWH, incidence of PCP remains high in those who are unaware of their HIV serostatus and/or are not on antiretroviral therapy (ART) or PCP prophylaxis.
  • •PCP also occurs in patients with severe cell-mediated immune deficiency (congenital T cell deficiency, acute leukemia, lymphoma, bone marrow or solid organ transplant), as well as in patients with inflammatory bowel disease, rheumatologic, and chronic lung diseases.1
  • •The major risk factor for infection in people without HIV is immunosuppression, and it is most commonly seen in patients on chronic high-dose glucocorticoid therapy (>15 mg prednisone equivalent for >2 to 4 wk).3 PCP also occurs in patients on treatment with other immunosuppressive therapies such as antilymphocyte monoclonal antibodies, tumor necrosis factor (TNF) alpha inhibitors, ibrutinib, or idelalisib.1 In addition to glucocorticoid use and immunosuppression, risk factors for mortality among people without HIV include increased age, lower Eastern Cooperative Oncology Group (ECOG) score, solid tumors, cytomegalovirus (CMV) coinfection, elevated lactate dehydrogenase (LDH), lower lymphocyte count, pneumothorax, concurrent pulmonary disease, and need for invasive ventilation.3,4 Patients at risk of developing Pneumocystis pneumonia unless prophylaxis is given are described in Table E1.
  • •Bacterial and viral coinfections including COVID-19 can occur with PCP.
  • •Pneumocystis is ubiquitous in the environment and is also frequently found as a colonizer in the airways of infants, children, and adults.

TABLE E1 Patients at Risk of Developing Pneumocystis Pneumonia, Unless Prophylaxis Is Given

HIV/AIDSSolid-Organ TransplantHematologic MalignancyConnective Tissue Disease
Risk factor for developing PCP
  • •CD4 count <200 cells/mm3
  • •CD4 <14% of total lymphocyte count
  • •Prior episode of PCP
  • •High plasma HIV load
  • •CD4 count <200 cells/mm3
  • •Use of:
    • •Corticosteroids
    • •Antilymphocyte therapy, (e.g., alemtuzumab, mycophenolate mofetil)
    • •Calcineurin inhibitors
  • •CMV disease
  • •Allograft rejection
  • •Prolonged neutropenia
  • •Exposure to patients with PCP
  • •CD4 count <200 cells/mm3
  • •Lymphopenia
  • •Use of:
    • •Monoclonal antibodies (e.g., rituximab)
    • •Immunosuppression to prevent rejection of allogenic hemopoietic SCT
    • •Purine analogues or high-dose corticosteroids for autologous SCT
    • •Chemotherapy (including R-CHOP14, FCR, ABVD, gemcitabine, high-dose methotrexate)
  • •ALL, or lymphoproliferative disorders (multiple myeloma, CML, NHL)
  • •GVHD
  • •CD4 count <200 cells/mm3
  • •Lymphopenia
  • •Use of:
    • •Anti-TNF inhibitors
    • •Azathioprine
    • •Corticosteroids (≥20 mg prednisolone OD (or equivalent) for ≥4 wk)
    • •Cyclophosphamide
    • •Methotrexate
    • •Rituximab
Prophylaxis given to patients
  • •CD4 count <200 cells/mm3
  • •CD4 <14% of lymphocyte count
  • •CD4 200-250 cells/mm3, if regular (e.g., 3 monthly) CD4 monitoring is not possible
  • •All solid-organ transplants
  • •Use of prednisolone ≥20 mg OD for ≥4 wk
  • •Recurrent or chronic CMV disease
  • •When immunosuppression is increased to prevent transplant rejection
  • •Prolonged neutropenia
  • •ALL
  • •Allogenic hemopoietic SCT
  • •20 mg prednisolone for ≥4 wk
  • •Use of:
    • •Alemtuzumab
    • •Fludarabine/cyclophosphamide/rituximab
  • •Optional:
    • •Radiotherapy and high-dose corticosteroids for primary brain tumor/metastases
    • •Lymphoma treated with R-CHOP14 or BEACOPP
  • •Use of:
    • •Nucleoside analogs (fludarabine, cladribine, mycophenolate mofetil)
  • •ANCA-positive vasculitis (especially granulomatosis with polyangiitis)
  • •Use of:
    • •Corticosteroids with other agents, e.g., azathioprine, cyclophosphamide, methotrexate, when used to treat SLE, or inflammatory myopathy (dermatomyositis, polymyositis)
Duration of prophylaxis
  • •When CD4 increases from <200 cells/mm3 to >200 cells/mm3 for >3 mo (reintroduce if CD4 falls to <200 cells/mm3 )
  • •When CD4 is 100-200 cells/mm3, if HIV plasma RNA level is below limits of quantification for 3-6 mo
  • •All solid-organ transplants: for 6-12 mo posttransplant
  • •Consider lifelong prophylaxis for:
    • •Lung/small bowel transplant
    • •History of prior PCP
    • •Chronic CMV disease
  • •ALL: From induction to end of maintenance
  • •Allogenic hemopoietic SCT: ≥6 mo after engraftment (and for as long as immunosuppression is ongoing)
  • •Alemtuzumab: >6 mo after completion of treatment
  • •Fludarabine/cyclophosphamide/rituximab: 6 mo after completion of treatment
Prophylaxis regimen
  • First choice:
  • TMP-SMX,
  • 1 double-strength (DS) tablet OD or 1 single-strength (SS) tablet OD
  • Alternatives:
  • Dapsone or dapsone plus pyrimethamine plus leucovorin, aerosolized pentamidine (via Respirgard II nebulizer) Atovaquone
  • First choice:
  • TMP-SMX, 1 SS tablet OD or 1 DS tablet OD (or 3 times per wk)
  • Alternatives:
  • Dapsone
  • Aerosolized pentamidine
  • Atovaquone
  • Clindamycin plusprimaquine
  • First choice:
  • TMP-SMX, 1 SS tablet OD or 1 DS tablet OD (or 3 times/wk)
  • Alternatives:
  • Dapsone
  • Aerosolized pentamidine
  • First choice:
  • TMP-SMX, 1 DS tablet OD or 1 SS tablet OD
  • Alternatives:
  • Dapsone, or dapsone plus pyrimethamine plus leucovorin
  • Aerosolized pentamidine
  • Atovaquone
Notes
  • •Prophylaxis indicated for all HIV-infected adults, including pregnant women and those on ART
  • •Prophylaxis not needed if receiving sulfadiazine-pyrimethamine for treatment or suppression of toxoplasmosis
  • •TMP-SMX DS tablet protects against toxoplasmosis and many respiratory infections
  • •Atovaquone is as effective as aerosolized pentamidine (but is more expensive)
  • •If seropositive for toxoplasmosis, and patient cannot tolerate TMP-SMX, dapsone plus pyrimethamine plus leucovorin, or atovaquone ± pyrimethamine plus leucovorin are alternatives
  • •Insufficient data to recommend:
    • •Aerosolized pentamidine given by devices other than Respirgard II
    • •Intermittently administered IV pentamidine
    • •Oral clindamycin plus primaquine (could consider these regimens if recommended agents cannot be administered or are not tolerated)

ABVD, Adriamycin (doxorubicin), bleomycin, vinblastine, dacarbazine; ALL, acute lymphoblastic leukemia; ANCA, antineutrophil cytoplasmic antibody; ART, antiretroviral therapy; BEACOPP, bleomycin, doxorubicin (adriamycin), etoposide, cyclophosphamide, vincristine (Oncovin), procarbazine, prednisolone; CML, chronic myeloid leukemia; CMV, cytomegalovirus; FCR, fludarabine, cyclophosphamide, rituximab; GVHD, graft-versus-host disease; HIV, human immunodeficiency virus; IV, intravenous; NHL, non-Hodgkin lymphoma; OD, every day; PCP, Pneumocystis jirovecii pneumonia; R-CHOP14, rituximab, cyclophosphamide, doxorubicin, vincristine (Oncovin), prednisolone (given every 14 days); SCT, stem cell transplant; SLE, systemic lupus erythematosus; TMP-SMX, trimethoprim-sulfamethoxazole; TNF, tumor necrosis factor.

From Bennett JE et al: Mandell, Douglas, and Bennett’s principles and practice of infectious diseases, ed 9, Philadelphia, 2020, Elsevier.

Predominant Sex:

Equal incidence when adjusted for HIV status.

Predominant Age:

During the AIDS epidemic, age at PCP diagnosis closely correlated with age at HIV infection. Currently the predominant age is 50 to 60 years due to changes in the populations at risk.1

Peak Incidence:

Widely variable based on the patient’s risk profile.

Genetics:

  • •Most frequent opportunistic infection among HIV-infected children, with serologic studies suggesting exposure typically occurs in childhood.
Physical Findings & Clinical Presentation

  • •PCP can present as an acute (3 to 5 days) or subacute (2 to 4 wk) pneumonia with fever, nonproductive cough, and progressive dyspnea. Patients progress to respiratory failure if not treated. Fulminant disease, longer hospital length of stay, and greater need for intensive care are observed more commonly in immunosuppressed patients without HIV than in PWH.5
  • •Purulent sputum argues against PCP.
  • •Hemoptysis is unusual.
  • •Extrapulmonary manifestations are rare but can involve nearly any organ.
  • •Vital signs: Notable for fever, tachypnea, low oxygen saturation. Oxygen desaturation with ambulation/exertion.
  • •Pulmonary exam is often normal. Dry rales can sometimes be auscultated.
  • •Spontaneous pneumothorax is possible; monitor for unilateral decreased or absent breath sounds.
Etiology

  • •P. jirovecii (formerly P. carinii) is a fungal organism (previously classified as a protozoan) (Fig. E1).
  • •Infection can occur either as a result of activation of latent infection or by new acquisition.
  • •Infection occurs via airborne transmission.
  • •No transmission from vertebrate animals (mammals) to humans.
  • •Increasing number of reports of nosocomial PCP transmission among immunocompromised patients (commonly solid organ transplant recipients).6
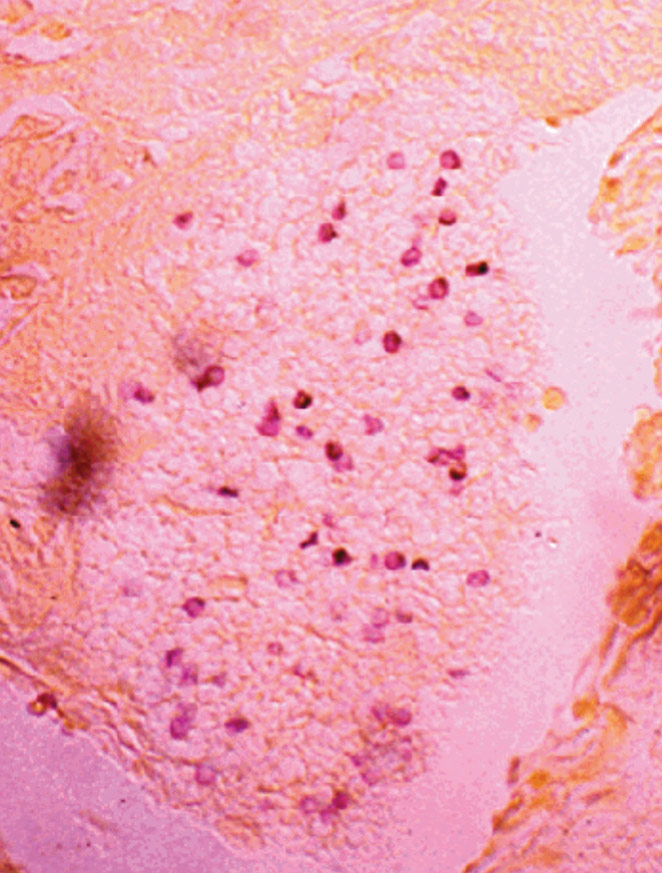
Figure E1 Wright-Giemsa stain of Pneumocystis jirovecii (carinii) pneumonia.

(From Gabbe SG: Obstetrics, ed 6, Philadelphia, 2012, Saunders.)

Diagnosis ⬆ ⬇

Differential Diagnosis

  • •Infectious etiologies:
    1. 1.Tuberculosis (especially in low- and middle-income countries)
    2. 2.Bacterial pneumonia
    3. 3.Viral pneumonia, including COVID-19 (SARS CoV-2)
    4. 4.Atypical pneumonia, such as Mycoplasma pneumonia
    5. 5.Cryptococcal pneumonia
    6. 6.Other fungal pneumonias, including endemic fungal infections such as Histoplasma and Coccidioides, as well as Aspergillus
    7. 7.CMV pneumonitis (in CD4 cell count <50 cells/mm3 or other severely immunocompromised state)
    8. 8.Mycobacterium avium complex (MAC) (in CD4 cell count <50 cells/mm3)
    9. 9.Toxoplasmosis
    10. 10.Legionella pneumonia
    11. 11.Strongyloidiasis
  • •Noninfectious etiologies:
    1. 1.Kaposi sarcoma
    2. 2.Non-Hodgkin lymphoma
    3. 3.Drug-induced pneumonitis
    4. 4.Pulmonary edema
    5. 5.Lymphocytic interstitial pneumonia
Workup

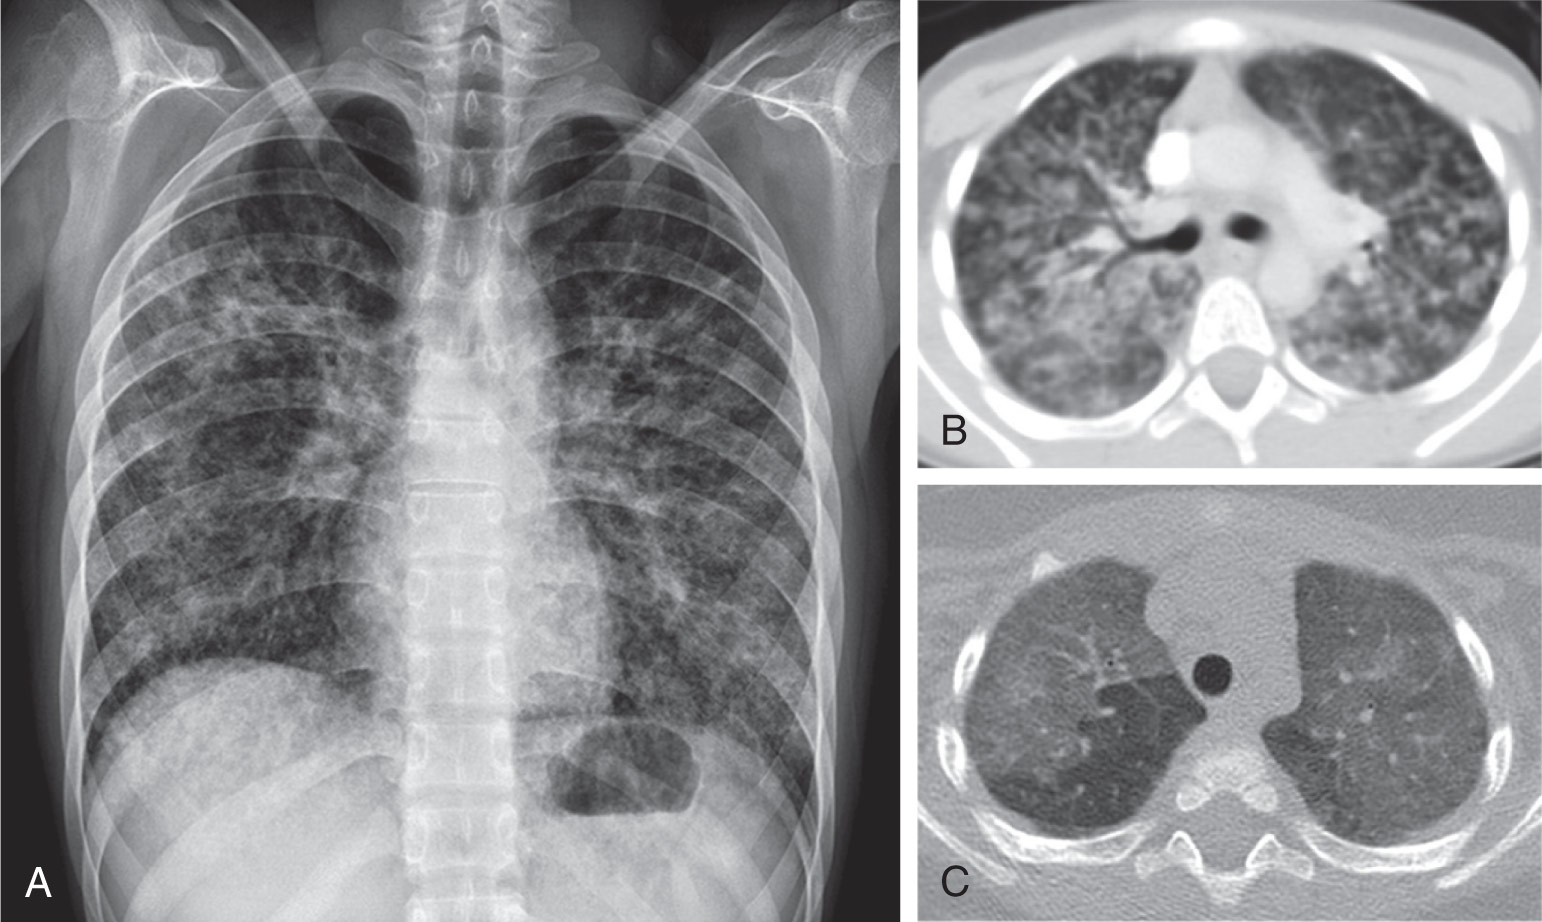
  • •Chest x-ray examination or chest computed tomography (CT) (Fig. E2).
  • •Arterial blood gas for evaluation of severity of hypoxemia and risk stratification.
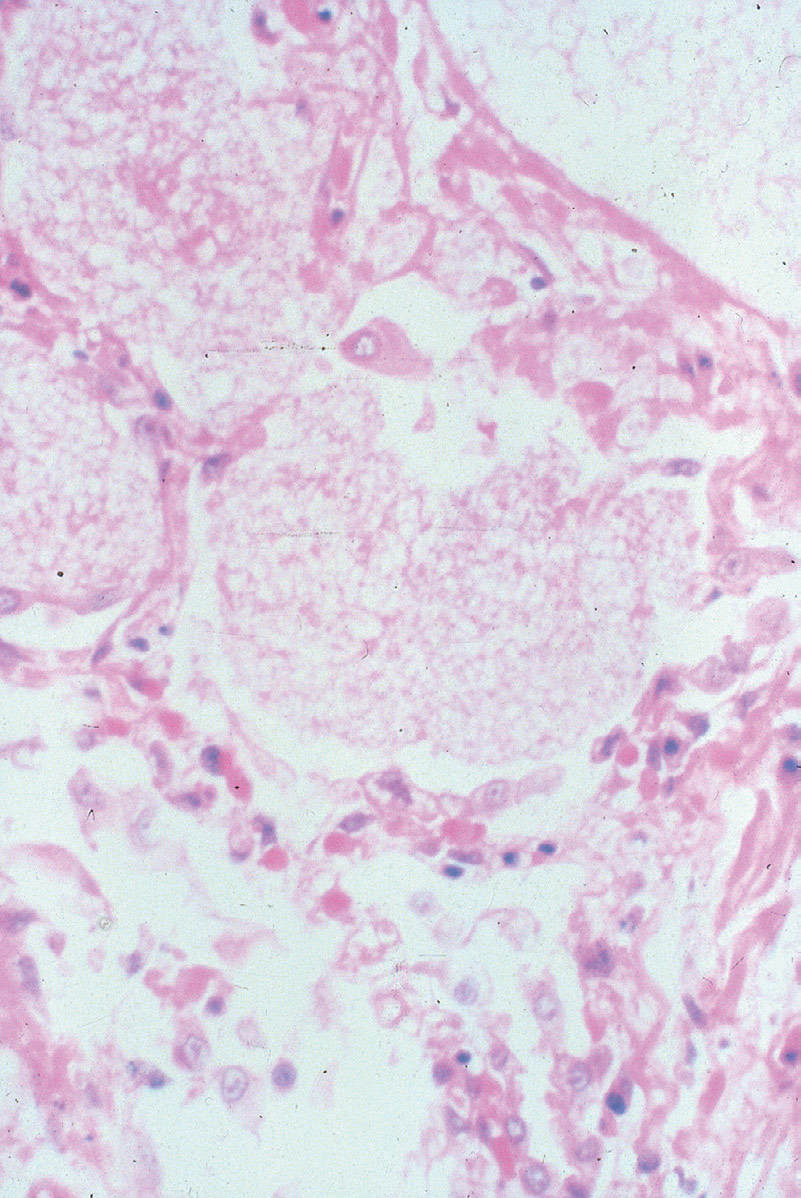
  • •Because Pneumocystis cannot be cultured, diagnosis is classically made through histopathologic or cytopathologic visualization of the organism from induced sputum, bronchoalveolar lavage (BAL) fluid, or tissue. Induced sputum is a common first diagnostic procedure. If negative, bronchoscopy with BAL is performed, and rarely a transbronchial biopsy can be done to augment BAL results and to exclude other pathogens. The principal histologic finding is a foamy, eosinophilic alveolar exudate (Fig. E3).
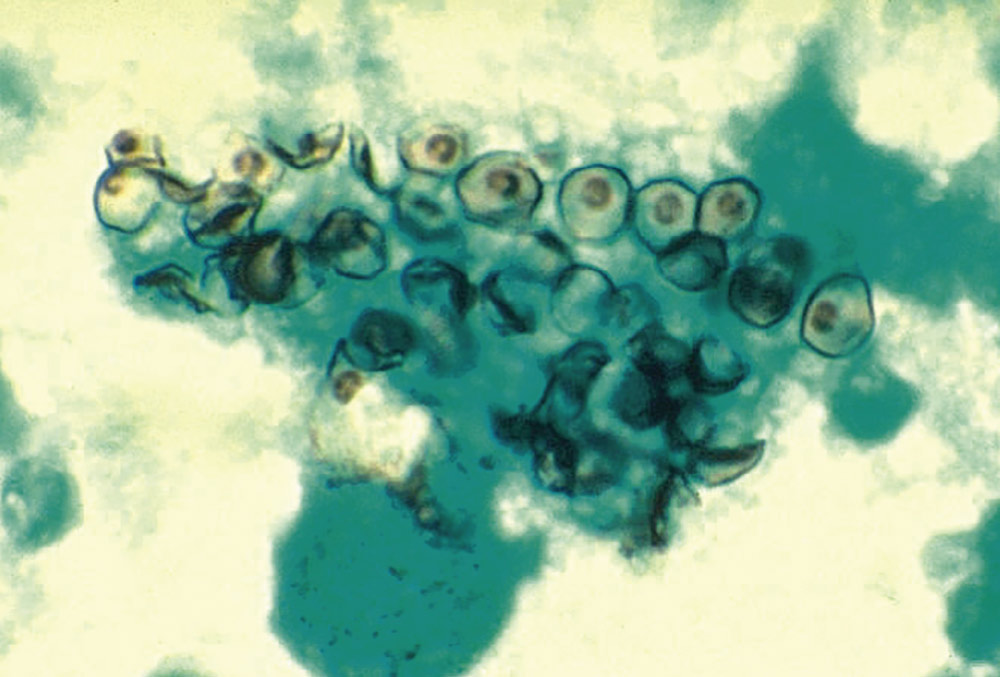
  • •Several stains can be performed (Fig. E4), such as Giemsa, Diff-Quik, and Wright (all stain both the cystic and the trophic forms of the organism but not the cyst wall); Grocott-Gomori methenamine silver, Gram-Weigert, toluidine blue, and cresyl violet stain (stain the cyst wall), as well as immunofluorescent stains, with results depending on the lab experience and the quality of the specimen.
  • •Polymerase chain reaction (PCR) of blood or BAL can be used. This cannot distinguish between colonization and active disease when positive, though it has excellent negative predictive value for PCP pneumonia when negative.7,8
  • •Serum 1,3-β-D glucan in blood or BAL has a good negative predictive value (very sensitive, less specific); test characteristics are slightly better in people with HIV.9
  • •LDH is nonspecific; it is often elevated, but a normal LDH does not rule out PCP. Persistently elevated LDH may be predictive of mortality or lack of response to treatment.4
  • •Metagenomic next-generation sequencing (mNGS) in blood or BAL fluid has demonstrated excellent performance for the diagnosis of PCP.10 Other new diagnostic modalities, such as measuring cell-free DNA in blood samples, have also shown promise as noninvasive diagnostic options.11
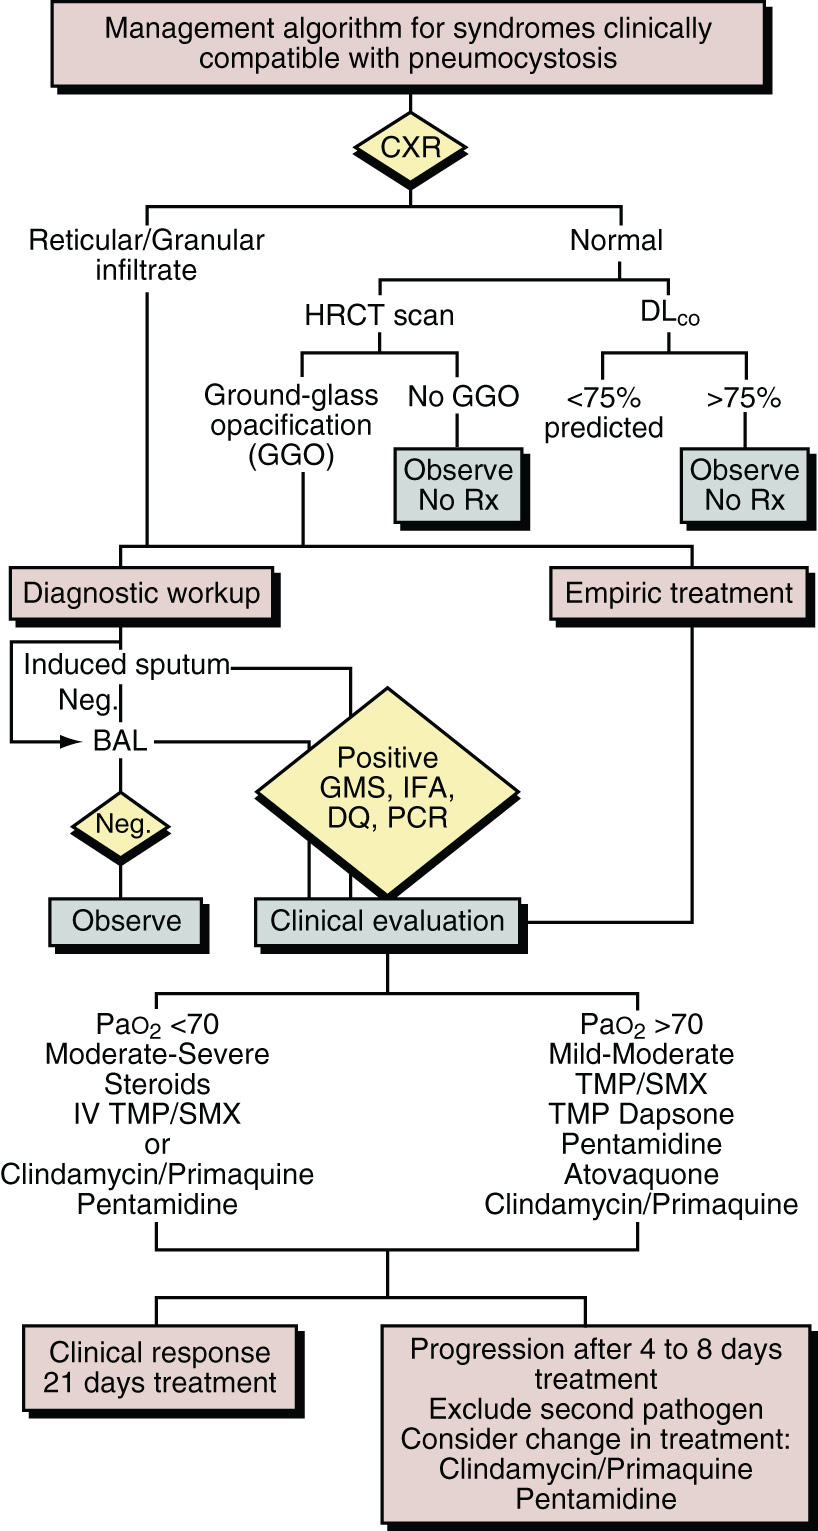
  • •Fig. E5 describes an algorithm for the diagnostic evaluation and management of patients with suspected Pneumocystis pneumonia.

Figure E2 Pneumocystis Jirovecii Infection in a 17-Yr-Old Male with Acute Lymphoblastic Leukemia and Immunodeficiency, Who Presented with Dyspnea, Fever, Nonproductive Cough, and Decreased White Blood Cell Counts

A, Radiograph shows diffuse bilateral interstitial opacity throughout the lungs. B, Contrast-enhanced computed tomography (CT) confirms the bilateral patchy and ground-glass opacities in both lungs. The diagnosis was confirmed by a positive polymerase chain reaction test from bronchial lavage fluid. C, CT in a different patient demonstrates a typical "crazy paving" pattern in both upper lobes.

(From Westra SJ et al: Pulmonary infection. In Coley BD [ed]: Caffey’s pediatric diagnostic imaging, ed 13, Philadelphia, 2019, Elsevier, Fig. 54.30.)

Figure E3 Histologic findings in pneumocystosis.

Pneumocystis pneumonia illustrating frothy eosinophilic honeycombed material filling the alveolar space (hematoxylin and eosin stain, ×400).

(From Bennett JE et al: Mandell, Douglas, and Bennett’s principles and practice of infectious diseases, ed 9, Philadelphia, 2020, Elsevier.)

Figure E4 Cysts of Pneumocystis jirovecii in smear from bronchoalveolar lavage.

Methenamine silver stain.

(Courtesy Dr. Russell K. Brynes/Centers for Disease Control and Prevention. In Ryan ET et al: Hunter’s tropical medicine and emerging infectious diseases, ed 10, Edinburgh, 2019, Elsevier.)

Figure E5 Algorithm for the Diagnostic Evaluation and Management of Patients with Suspected Pneumocystis Pneumonia

!!flowchart!!

BAL, Bronchoalveolar lavage; CXR, chest x-ray examination; DLCO, single-breath diffusing capacity for carbon monoxide; DQ, Diff-Quik (stain); GGO, ground-glass opacities; GMS, Gomori methenamine silver (stain); HRCT, high-resolution computed tomography; IFA, immunofluorescent antibody (stain); IV, intravenous; Neg., negative; PaO2, partial pressure of oxygen in arterial blood; PCR, polymerase chain reaction; Rx, treatment; TMP/SMX, trimethoprim-sulfamethoxazole.

(From Bennett JE et al: Mandell, Douglas, and Bennett’s principles and practice of infectious diseases, ed 9, Philadelphia, 2020, Elsevier.)

Laboratory Tests

  • •HIV antibody test and CD4 cell count (with CD4%) if cause of underlying immune deficiency state is unclear
  • •Arterial blood gas and calculation of the alveolar-arterial (A-a) oxygen gradient for determination of disease severity and need for adjunctive corticosteroids:
    1. 1.Mild disease: A-a gradient <35 mm Hg and/or PaO2>70 mm Hg
    2. 2.Moderate disease: A-a gradient 35 to 45 mm Hg and 60 mm Hg <PaO2<70 mm Hg
    3. 3.Severe disease: A-a gradient >45 mm Hg and PaO2<60 mm Hg
  • •Elevated 1,3-β-D-glucan (>80 pg/ml)
  • •Elevated lactate dehydrogenase
Imaging Studies

  • •Early in the disease course, the chest x-ray examination can be normal. In these cases, a high-resolution chest CT is recommended. This test is mostly useful in ruling out PCP because a chest CT without ground-glass opacities makes the diagnosis extremely unlikely.
  • •Classically, PCP presents as bilateral, symmetric interstitial, reticular, or granular infiltrates in the perihilar region ("butterfly pattern") on chest x-ray examination, and CT chest typically shows ground-glass opacities; however, variable radiographic presentations are possible (unilateral, asymmetric, nodular, miliary, etc.).8,10 Pneumatoceles, or cysts, which may cause pneumothorax, are more common in people with HIV.
Other Studies

If diagnostic uncertainty, PFTs can be used as adjunctive test. Low diffusing capacity for carbon monoxide (DLCO) is highly sensitive but not specific for PCP infection. A normal DLCO argues against PCP.

Treatment ⬆ ⬇

Nonpharmacologic Therapy

  • •Supplemental oxygen
  • •Noninvasive or invasive ventilatory support if needed
  • •Prompt chest tube placement if pneumothorax develops
Acute General Rx

For confirmed or suspected PCP (Table E2):

  • •Preferred therapy: Trimethoprim-sulfamethoxazole (TMP-SMX; 15 to 20 mg/kg trimethoprim and 75 to 100 mg/kg sulfamethoxazole) divided and given q6 to 8h. Recent systematic reviews and meta-analyses have suggested that lower doses of TMP-SMX may be as effective and may be considered in older adults or those with renal dysfunction; however, official guidelines continue to recommend the higher dose of TMP-SMX at this time.13
    1. 1.Mild PCP can be treated with PO formulation of TMP-SMX, usually two double-strength (DS) tablets PO tid.
    2. 2.Moderate and severe disease should be treated with intravenous (IV) formulation of TMP-SMX at first but can be switched to PO after clinical improvement.
  • •Alternative therapies: Use only if severe contraindication to TMP-SMX (e.g., Stevens-Johnson syndrome [SJS] or toxic epidermal necrolysis [TEN]) and after development of treatment-limiting adverse reaction.
    1. 1.Mild-moderate disease:
      1. a.TMP 15 mg/kg/day split into tid dosing plus dapsone 100 mg PO daily, OR
      2. b.Clindamycin 600 mg PO q8h plus primaquine 30 mg (base) PO daily, OR
      3. c.Atovaquone 750 mg PO bid (with food)
    2. 2.Moderate-severe disease:
      1. a.Clindamycin (600 mg q6h or 900 q8h) IV and primaquine 30 mg (base) PO daily, OR
      2. b.Pentamidine (4 mg/kg) IV daily. May reduce dose to 3 mg/kg IV daily if toxicity develops. Careful monitoring is required, as IV pentamidine can cause nephrotoxicity, numerous electrolyte disturbances, and cardiac arrhythmias.
  • •Adjunctive corticosteroids are indicated in moderate to severe PCP (PaO2 <70 mm Hg and A-a gradient >35 mm Hg) in PWH. Data are conflicting regarding the benefit of adjunctive corticosteroids in people without HIV, especially in those with mild or moderate disease4 (see also Hosseini-Moghaddam et al, Am J Transplant. 2024 & Kamel et al, Intensive Care Med. 2024):
    1. 1.Prednisone 40 mg bid × 5 days, followed by 40 mg/day × 5 days, followed by 20 mg/day × 11 days (for total of 21 days)
    2. 2.Alternative: IV methylprednisolone at 75% of prednisone dose
  • •Therapy continued for 21 days.
  • •Antiretroviral therapy in HIV positive individuals should be initiated as soon as possible, ideally within 2 wk of PCP diagnosis. Monitor for immune reconstitution inflammatory syndrome (IRIS).
  • •Table E3 summarizes causes of deterioration in an HIV-infected patient receiving treatment for PCP.

TABLE E3 Causes of Deterioration in an HIV-Infected Person Receiving Treatment for PCP

EtiologyExplanation
Severe Progressive PCP
Iatrogenic
  • Pulmonary edema due to IV fluid overload when giving TMP-SMX
  • IRIS following early initiation of ART
Side effects of therapyAnemia (e.g., caused by TMP-SMX), methemoglobinemia (e.g., caused by dapsone, primaquine)
Inadequate therapy
  • Incorrect dosage or route of administration
  • Adjuvant glucocorticoids not given for treatment of moderate or severe PCP
Postbronchoscopy
  • Sedation
  • Pneumothorax
Pneumothorax
  • Spontaneous
  • Associated with intubation and positive pressure ventilation
Copathology in lung
  • Bacterial infection
  • Pulmonary Kaposi sarcoma
  • Intercurrent pulmonary embolism
Wrong diagnosisEmpiric diagnosis of PCP, and correct diagnosis is another pathology (e.g., bacterial pneumonia)

ART, Antiretroviral therapy; HIV, human immunodeficiency virus; IRIS, immune reconstitution inflammatory syndrome; IV, intravenous; PCP, Pneumocystis jirovecii pneumonia; TMP-SMX, trimethoprim-sulfamethoxazole.

From Bennett JE et al: Mandell, Douglas, and Bennett’s principles and practice of infectious diseases, ed 9, Philadelphia, 2020, Elsevier.

TABLE E2 Treatment of Pneumocystis Pneumonia

DrugDoseComments
Preferred
TMP-SMXa15-20 mg/kg (TMP) and 75-100 mg/kg (SMX) IV or PO divided into doses given q6-8h (AI)b
  • Severe PCP: IV may be switched to PO with clinical improvement
  • Mild-to-moderate PCP: PO dose can be given as TMP-SMX DS 2 tablets PO tid
Alternatives
Clindamycin plus600-900 mg IV q6-8h
or
300-450 mg PO q6-8h
plus
Severe PCP: IV may be switched PO with clinical improvement
Mild-to-moderate PCP: PO dose can be used
Check for G6PD deficiency before use
Primaquine15 or 30 mg (of the base) PO qd (BI)
Pentamidine4 mg/kg IV q24h (BI)For moderate-to-severe PCP, some clinicians "dose reduce" to 3 mg/kg to reduce toxicity
TMP plus15 mg/kg PO (in divided doses, q8h) plusFor mild-to-moderate PCP, monitor for methemoglobinemia
Dapsone100 mg PO qd (BI)
Atovaquone750 mg suspension PO bid (BI)For mild-to-moderate PCP, take with food
Adjunctive
Prednisone
  • 40 mg PO bid days 1-5
  • 40 mg PO qd days 6-10
  • 20 mg PO qd days 11-21 (AI)
  • IV methylprednisolone can be administered as 75% of PO prednisone dose
  • For moderate-to-severe PCP, PaO2≤70 mm Hg, or alveolar-arterial O2 gradient >35 mm Hg
  • Begin as soon as possible and within 72 h of starting PCP therapy

bid, Twice per day; DS, double strength; G6PD, glucose-6-phosphate dehydrogenase; IV, intravenously; PaO2, partial pressure of arterial blood oxygen; PCP, Pneumocystis pneumonia; PO, orally; qd, every day; SMX, sulfamethoxazole; tid, three times per day; TMP, trimethoprim.

Duration of therapy is 21 days for patients with underlying HIV infection; shorter treatment course (typically 14-17 days) for those with other causes of immunodeficiency (e.g., renal transplantation).

a DS tablet = TMP 160 mg and SMX 800 mg.

b AI and BI grading scores are defined as follows: AI, Strong recommendation for the statement: One or more randomized trials with clinical outcomes or validated laboratory end points; BI, moderate recommendation for the statement: One or more randomized trials with clinical outcomes or validated laboratory end points.

Modified from Panel on Opportunistic Infections in HIV-Infected Adults and Adolescents: guidelines for the prevention and treatment of opportunistic infections in HIV-infected adults and adolescents: recommendations from the Centers for Disease Control and Prevention, the National Institutes of Health, and the HIV Medicine Association of the Infectious Diseases Society of America. Available at http://aidsinfo.nih.gov/contentfiles/lvguidelines/adult_oi.pdf.

Prophylaxis (Table E4

  • •Primary prophylaxis:
    1. 1.In people with HIV, primary prophylaxis is indicated when CD4 count <200 cells/mm3 or CD4% <14%. Acceptable regimens of TMP-SMX include one DS tablet PO daily, one single-strength (SS) tablet PO daily, or one DS tablet PO three times a wk. Can consider discontinuation of prophylaxis if CD4 cell count between 100 and 200/mm3 with undetectable HIV viral load for 3 to 6 mo following ART initiation.12
    2. 2.Commonly also applied to individuals on prolonged courses of steroids (e.g., >4 wk of >20 mg prednisone daily).
    3. 3.Indicated in certain immunosuppressed adults with malignancy, with rheumatologic, autoimmune, and dermatologic diseases on biologic therapy, and in patients with solid organ transplants, although official guidelines for PCP prophylaxis are still needed in many patient populations.3,14,15
  • •Secondary prophylaxis:
    1. 1.After completion of therapy, in PWH secondary prophylaxis should be maintained with TMP-SMX (one SS tablet PO daily OR one DS tablet PO daily OR [alternative] one DS tablet PO three times weekly) until the CD4 cell count is >200 cells/mm3 and viral load is undetectable for at least 3 mo after ART initiation.12
    2. 2.If PCP occurs at a CD4 cell count >200 cells/mm3 while on ART, continue PCP prophylaxis for life regardless of CD4 cell count.
  • •Patients intolerant of TMP-SMX should be treated with dapsone (100 mg PO daily) or atovaquone (1500 mg PO daily).
  • •Inhaled pentamidine (300 mg monthly by standardized nebulizer) is less effective and is reserved for patients intolerant to other forms of prophylaxis. Inhaled pentamidine or dapsone without pyrimethamine should not be used for PCP prophylaxis in patients with HIV who are also seropositive for Toxoplasma gondii.12

TABLE E4 Prevention of Pneumocystis Pneumonia

DrugDoseComments
Preferred
TMP-SMXa
  • 1 DS tab PO qd (AI)b
  • 1 SS tab PO qd (AI)
Both regimens are effective; SS tab may have fewer side effects
Alternative
TMP-SMX1 DS tab PO tiw (BI)Similar to other TMP-SMX regimens
Dapsone
  • 100 mg PO qd (BI)
  • or 50 mg PO bid
Methemoglobinemia may occur
Dapsone plus
  • 50 mg PO qd
  • plus
Methemoglobinemia may occur
Pyrimethamine plus
  • 50 mg PO qwk (BI)
  • plus
May also prevent toxoplasmosis
Leucovorin25 mg PO qwk
Pentamidine300 mg qmo aerosolized via Respirgard II nebulizer (BI)
Atovaquone750 mg suspension PO bid or 1500 mg qd (BI)
Atovaquone plus750 mg suspension PO bid or 1500 mg qd plus
Pyrimethamine plus25 mg PO qd (BII) plus
Leucovorin10 mg PO qd

bid, Twice per day; DS, double strength; PO, orally; qd, every day; qmo, every month; qwk, every week; SS, single strength; tiw, three times per wk; TMP-SMX, trimethoprim-sulfamethoxazole.

a SS tablet = TMP 80 mg and SMX 400 mg; DS tablet = TMP160 mg and SMX 800 mg.

b AI and BI grading scores are defined as follows: AI, Strong recommendation for the statement: One or more randomized trials with clinical outcomes/or validated laboratory end points; BI, moderate recommendation for the statement: One or more randomized trials with clinical outcomes/or validated laboratory end points; BII, moderate recommendation for the statement: One or more well-designed, nonrandomized trials, or observational cohort studies with long-term clinical outcomes.

Modified from Panel on Opportunistic Infections in HIV-Infected Adults and Adolescents: guidelines for the prevention and treatment of opportunistic infections in HIV-infected adults and adolescents: recommendations from the Centers for Disease Control and Prevention, the National Institutes of Health, and the HIV Medicine Association of the Infectious Diseases Society of America. Available at http://aidsinfo.nih.gov/contentfiles/lvguidelines/adult_0i.pdf.

Disposition

  • •After completion of therapy, long-term ambulatory follow-up is mandatory to provide secondary prophylaxis of PCP and management of the underlying immunodeficiency syndrome.
  • •Many patients have chronic respiratory complaints such as exertional dyspnea and may develop chronic obstructive pulmonary disease (COPD). These patients should be referred to a pulmonologist for evaluation and management.
Referral

  • •To a pulmonologist for bronchoscopy if diagnosis cannot be confirmed by sputum examination
  • •To an infectious disease specialist if case is severe or difficult to manage and to evaluate for underlying immune deficiency
  • •To a pulmonologist for evaluation if persistent respiratory complaints such as exertional dyspnea after PCP treatment

Pearls & Considerations ⬆ ⬇

Comments

  • •All patients, especially those with severe infection or intolerant of conventional therapy, should be followed by a physician experienced in the management of PCP and, if appropriate, in the long-term management of HIV infection or other underlying disease.
  • •Patients with suspected PCP should be started on empiric PCP therapy (and adjunctive corticosteroids if indicated) without waiting for diagnostic procedures. Pneumocystis can be seen on microscopic examination days to weeks into PCP therapy.
  • •Before administration of dapsone or primaquine, patients should be tested for G6PD deficiency.
  • •Clinical and chest x-ray examination findings in patients with PCP may worsen in the first 5 days after treatment initiation. Wait to declare treatment failure until after at least 7 to 10 days of therapy.8
  • •Mutations associated with resistance to sulfa drugs in other microorganisms have been documented in P. jirovecii, but their effect on clinical outcomes is uncertain.
  • •Monitor for IRIS in those with HIV after initiation of ART.
  • •TMP-SMX can have a range of side effects, including neutropenia (absolute neutrophil count <500 cells/mm3), fever, hyperkalemia, acute kidney injury, rash. May be able to slowly reintroduce medication after resolution of most mild side effects. Most severe and deadly TMP-SMX side effect is Stevens Johnson syndrome/toxic epidermal necrolysis (SJS/TEN); avoid all sulfa drugs thereafter.
  • •Severe and life-threatening hypoglycemia may occur 1 or 2 wk after starting IV pentamidine. Monitor closely and advise the patient of symptoms of hypoglycemia.
  • •Coinfection with other pathogens can be seen.8
  • •Consider indications for primary PCP prophylaxis in all immunosuppressed patients regardless of HIV status.
Related Content

Reference(s) ⬆

  1. Gold JAW : Possible diagnostic delays and missed prevention opportunities in Pneumocystis pneumonia patients without HIV: analysis of commercial insurance claims data-United States, 2011-2015doi:10.1093/ofid/ofaa255Open Forum Infect Dis. 7(7):ofaa255, 2020.
  2. McMullan B : Features and global impact of invasive fungal infections caused by Pneumocystis jirovecii: a systematic review to inform the World Health Organization fungal priority pathogens listdoi:10.1093/mmy/myae038Med Mycol. 62:myae038, 2024.
  3. Fragoulis GE : 2022 EULAR recommendations for screening and prophylaxis of chronic and opportunistic infections in adults with autoimmune inflammatory rheumatic diseasesdoi:10.1136/ard-2022-223335Ann Rheum Dis. 82:742-753, 2023.
  4. Wang Y : Risk factors of mortality from Pneumocystis pneumonia in non-HIV patients: a meta-analysisdoi:10.3389/fpubh.2021.680108Front Public Health. 9:680108, 2021.
  5. Benedict K : Epidemiology, clinical characteristics, and diagnostic testing practices for pneumocystis pneumonia-associated hospitalizations, United States, 2019-2022doi:10.1093/ofid/ofae054Open Forum Infect Dis. 11(2):ofae054, 2024.
  6. Yiannakis EP, Boswell TC : Systematic review of outbreaks of Pneumocystis jirovecii pneumonia: evidence that P. jirovecii is a transmissible organism and the implications for healthcare infection controldoi:10.1016/j.jhin.2016.01.018J Hosp Infect. 93(1):1-8, 2016.
  7. Brown L : Polymerase chain reaction on respiratory tract specimens of immunocompromised patients to diagnose Pneumocystis pneumonia: a systematic review and meta-analysisdoi:10.1093/cid/ciae239Clin Infect Dis. 79(1):161-168, 2024.
  8. White P : Therapy and management of Pneumocystis jirovecii infectiondoi:10.3390/jof4040127J Fungi. 4(4):127, 2018.
  9. Del Corpo O : Diagnostic accuracy of serum (1-3)-β-D-glucan for Pneumocystis jirovecii pneumonia: a systematic review and meta-analysisdoi:10.1016/j.cmi.2020.05.024Clin Microbiol Infect. 26(9):1137-1143, 2020.
  10. Li X : Diagnostic performance of metagenomic next-generation sequencing for Pneumocystis jirovecii pneumoniahttps://doi.org/10.1186/s12879-023-08440-4BMC Infect Dis. 23:455, 2023.
  11. Moreno A : Accuracy of Pneumocystis jirovecii plasma cell-free DNA PCR for noninvasive diagnosis of Pneumocystis pneumoniahttps://doi.org/10.1128/jcm.00101-22J Clin Microbiol. 60:1-7, 2022.
  12. NIH: Pneumocystis pneumonia. Available at https://clinicalinfo.hiv.gov/en/guidelines/hiv-clinical-guidelines-adult-and-adolescent-opportunistic-infections/pneumocystis-0. Accessed August 11, 2022.
  13. Haseeb A : Trimethoprim-sulfamethoxazole (Bactrim) dose optimization in Pneumocystis jirovecii pneumonia (PCP) management: a systematic reviewdoi:10.3390/ijerph19052833Int J Environ Res Public Health. 19(5):2833, 2022.
  14. Taplitz RA : Antimicrobial prophylaxis for adult patients with cancer-related immunosuppression: ASCO and IDSA clinical practice guideline updatedoi:10.1200/JCO.18.00374J Clin Oncol. 36(30):3043-3054, 2018.
  15. Fishman JA : Pneumocystis jiroveci in solid organ transplantation: guidelines from the American Society of Transplantation Infectious Diseases Community of Practicedoi:10.1111/ctr.13587Clin Transplant. 33(9):e13587, 2019.